 Back
Anatomy & Physiology (CH.8): Joints and Movements
 04:06

Terms in this set (48)
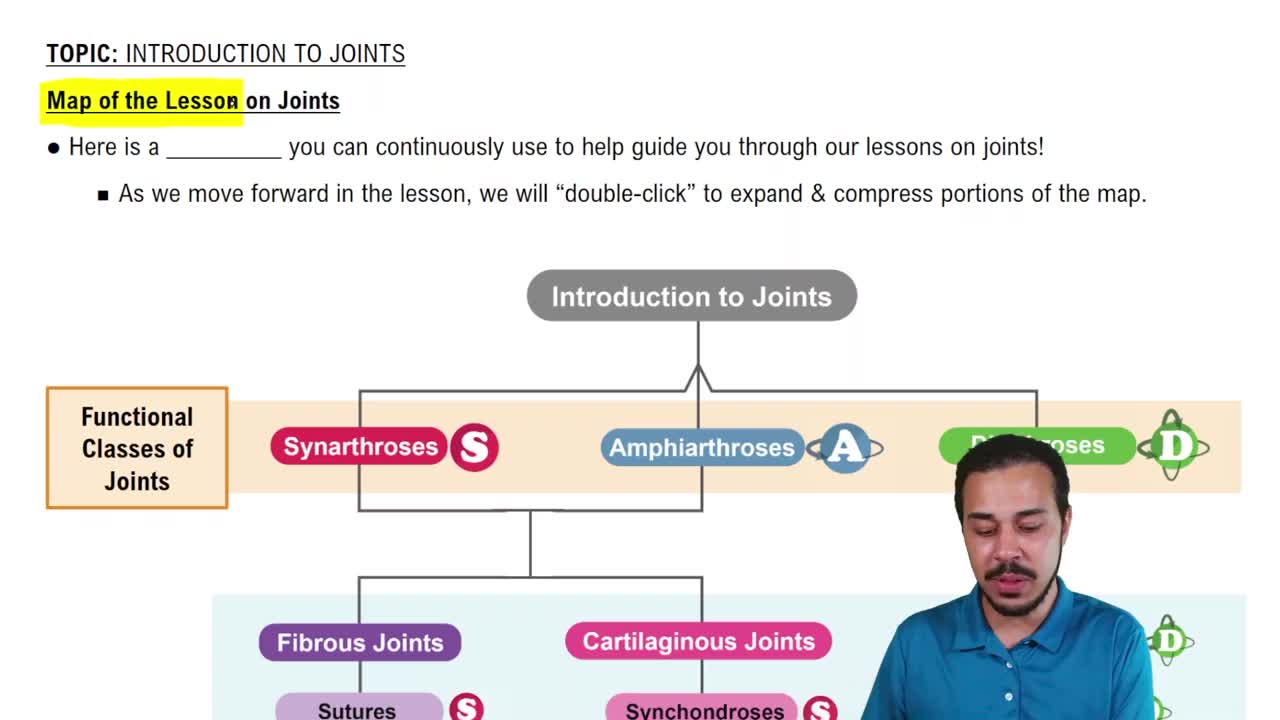
Structural-more clear cut (fibrous, cartilaginous, synovial) based on material and cavity presence, and Functional (synarthroses, amphiarthroses, diarthroses) based on movement allowed.
Bones joined by dense fibrous connective tissue with no joint cavity. Most = immovable-depends on length of connective tissue fibers. Types: sutures, syndesmoses, and gomphoses.
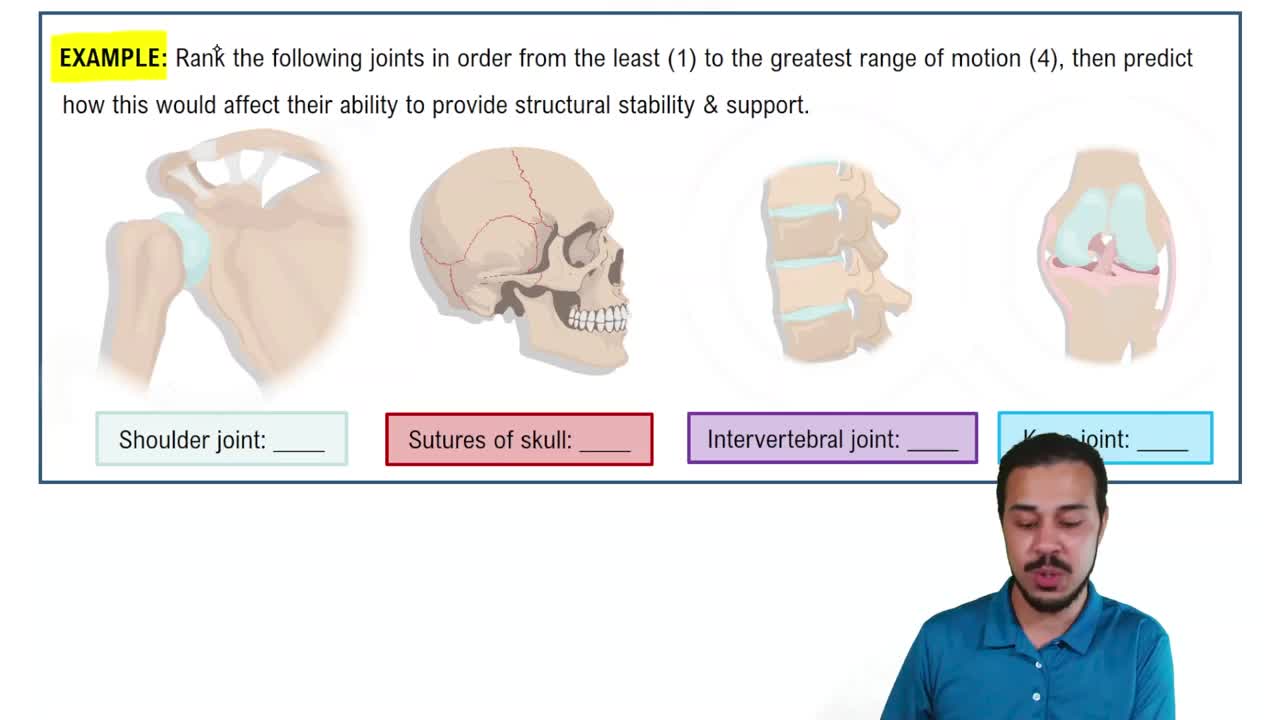
Rigid, interlocking joints of the skull with short connective tissue fibers allowing growth in youth; in middle age, they ossify and fuse. Immovable joints join skull into
one unit that protects brain
Bones connected by ligaments, bands of fibrous tissue. Fiber length varies, so does movement. Longer fibers offer a larget amount of movement.
A peg-in-socket joint. ONly example= teeth in alveolar sockets.
Bones united by cartilage, no joint cavity, not highly moveable. Types: synchondroses and symphyses.
Bar or plate of hyaline cartilage unites bones. Almost all are synarthrotic (immovable)
Ex: Temporary epiphyseal plate joints (become synostoses after plate closure). Cartilage of 1st rib with manubrium of sternum
Bones united by fibrocartilage. They are strong & slightly movable (amphiarthrotic). Examples: intervertebral discs (sandwiched b/t hyaline catilage) and pubic symphysis.
What are the first 3/6 general features of synovial joints?
1. Articular cartilage (consists of hyaline cartilage covering ends of bones-prevents crushing of bone ends), 2. Joint (synovial) cavity (small, fluid-filled potential
space that is unique to synovial joints)
3. Articular capsule (2 layers thick)-External fibrous layer: dense irregular connective tissue
• Inner synovial membrane: loose connective tissue that makes synovial fluid.
What are bursae and tendon sheaths?
-Bags of synovial fluid that act as lubricating “ball bearing”. (Not strictly part of synovial joints, but closely associated)
Bursae: reduce friction where ligaments, muscles, skin, tendons, or bones rub together.
Tendon sheaths: elongated bursae wrapped completely around tendons subjected to friction
What 3 factors influence synovial joint stability?
1. Shape of articular surface (minor role)-Shallow surfaces less stable than ball-and-socket. 2. Ligament number & location (limted role)-more ligaments, stronger the joint 3. Muscle tone (most important)-reinforces shoulder and knee joints & arches of the foot
What are the types of synovial joint movements by axis? (4)
Nonaxial (slipping), uniaxial (movement of one plane), biaxial (movement of two planes), multiaxial (movement in or around all three planes).
One flat bone surface glides or slips over another similar surface. Examples: intercarpal joints, intertarsal joints, & b/t articular processes of vertebrae (gliding movements of the wrist)
Increase or decrease angle between two bones (sagittla plane)
Ex: Flexion: decreased angle of the joint. Extension: Increases angle of the joint (Hyperextension: movement beyond the anantomical position),
Turning of a bone around its own long axis; toward midline or away from it. Medial rotation: rotation toward midline. Lateral: rotation away from midline. (Ex: Rotation between C1 and C2 vertebrae. Rotation of humerus and femur)
Supination & pronation: rotation of radius and ulna. Supination: palms face anteriorly (Radius and ulna= parallel). Pronation: palms face posteriorly (Radius rotates over ulna)
Dorsiflexion & plantar flexion of foot: Dorsiflexion: bending foot toward shin. Plantar flexion: pointing toes
Plane, hinge, pivot, condylar, saddle, and ball-and-socket joints.
(based on shape of articular surface, as well as movement joint is capable of)
What are the key features of the knee joint?
-Largest & most complex joint with three joints in one cavity;
includes femoropatellar joint-plane joint, allows gliding motion during knee flexion. Lateral. & Medial joints; Femoral condyles with lateral and medial menisci of tibia. Allow flexion, extension, and some rotation when knee partly flexed
Simultaneous injury to the anterior cruciate ligament, tibial collateral ligament, and medial meniscus. Ruptured ACL, ruptured tibial collateral ligament, and
torn meniscus.
Describe the temporomandibular joint (TMJ).
-Jaw joint is a modified hinge joint
-Mandibular condyle articulates with
temporal bone
Two types of movement: Hinge: depression and elevation of mandible. Gliding: side-to-side (lateral excursion) grinding of teeth
-Most easily dislocated joint in the
body
Cartilage tears, sprains (ligament tears), and dislocations (luxations).
B: Inflammation of bursa, usually caused by blow or friction. Treated with rest and ice and, if severe, anti- inflammatory drugs. T: Inflammation of tendon sheaths, typically caused by
overuse. Symptoms and treatment similar to those of bursitis
What is arthritis and its common types?
Chronic forms: osteoarthritis, rheumatoid arthritis, & gouty arthritis
>100 different types of inflammatory or degenerative diseases that damage joints. Most widespread crippling disease in the U.S. Symptoms: pain, stiffness, and swelling of joint. Acute forms: caused by bacteria, treated with antibiotics
Describe osteoarthritis.
-Most common type of arthritis
-By age 85, half of Americans develop OA, more
women than men
Irreversible, degenerative (“wear-and-tear”) arthritis. Cartilage is broken down faster than it is replaced. Bone spurs may form from thickened ends of bones. Joints may be stiff and make crunching noise referred to as crepitus, especially upon rising
What is rheumatoid arthritis?
-Chronic, inflammatory, autoimmune disease of unknown cause
Immune system attacks own cells. Usually arises between ages 40 and 50, but may occur at any age; affects three times as many women as men. Signs and symptoms include joint pain and swelling (usually bilateral), anemia, osteoporosis, muscle weakness, and cardiovascular problems
What causes gouty arthritis and its treatment?
-Deposition of uric acid crystals in joints and soft tissues, followed by inflammation. More common in men
Typically affects joint at base of great toe. In untreated gouty arthritis, bone ends fuse and
immobilize joint. Treatment: drugs, plenty of water, avoidance of alcohol and foods high in purines, such as liver, kidneys, and sardines
Advancing years take toll on joints. Ligaments and tendons shorten and weaken. Intervertebral discs more likely to herniate. Most people in 70s have some degree of OA. Full-range-of-motion exercise key to postponing joint problems
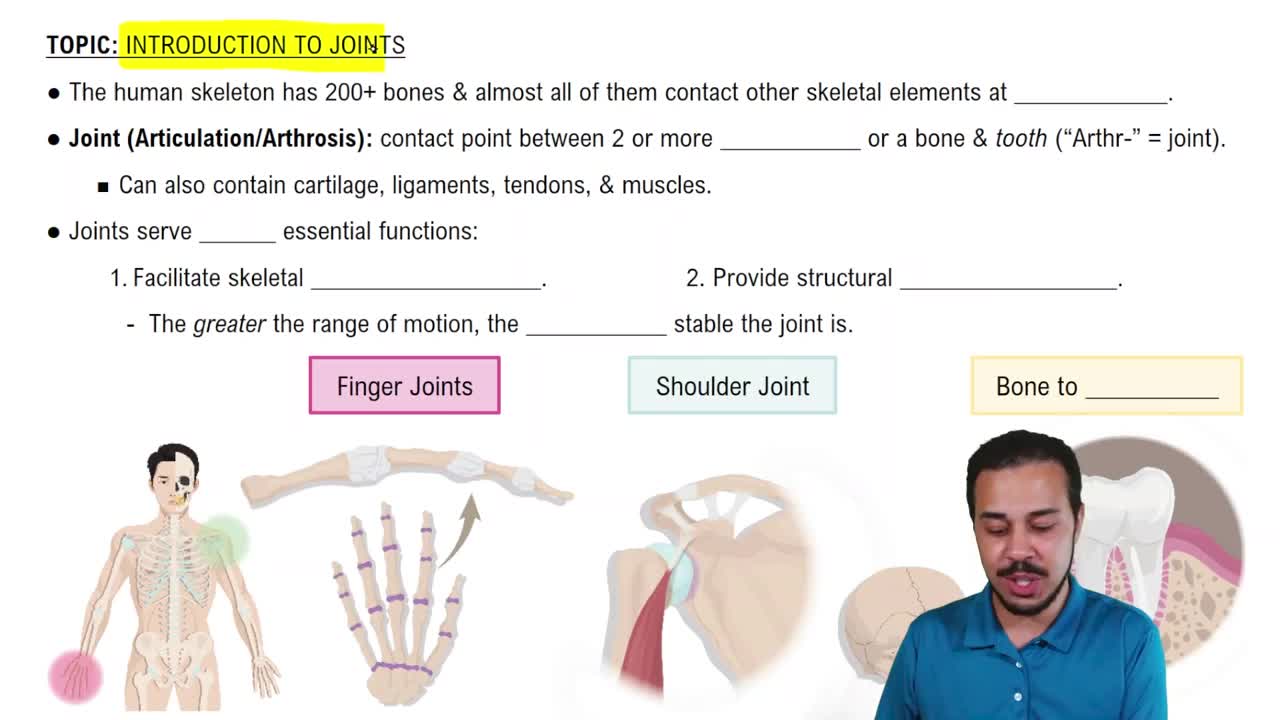
Function of joints
called articulations: where 2+ bones meet. give skeleton mobility and hold skeleton
together
Explain synovial joints. What are their 5 charcteristics?
-Bones separated by fluid-filled joint cavity. All are diarthrotic (freely movable). Include almost all limb joints.
A. Have six general features
B. Have bursae and tendon sheaths associated with
them
C. Stability is influenced by three factors
D. Allow several types of movements
E. Classified into six different types
What are the last 3/6 general features of the synovial joints?
-4. Synovial fluid (viscous, slippery filtrate of plasma and hyaluronic acid)-Lubricates and nourishes articular cartilage. Contains phagocytic cells to remove microbes and debris.
5. Reinforcing liga. (Capsular: thickened part of fibrous layer. Extracapsular: outside capsule. Intracapsular: deep to capsule; covered by synovial membrane 6. Nerves & blood vessels (Nerves detect pain; monitor joint position and stretch. Capillary beds supply filtrate for synovial fluid)
What are some other features of synovial joints ?
Fatty pads: For cushioning between fibrous layer of capsule and synovial
membrane or bone. Articular discs (menisci): Fibrocartilage separates articular surfaces to improve “fit” of bone ends, stabilize joint, and reduce wear and tear
Explain movements allowed by synovial joints
All muscles attach to bone or connective tissue at no fewer than 2 points
• Origin: attachment to immovable bone. Insertion: attachment to movable bone
-Muscle contraction causes insertion to move toward origin
(insertion=moving part when you flex)
What are the 3 types of general types of movements (synovial joints)
Gliding, angular movements, rotation
Explain Abduction, Adduction, & Circumduction (angular movements of synovial joints)
Abduction: movement along frontal plane, away from the midline. Adduction: movement along frontal plane, toward the midline. Circumduction: Involves flexion, abduction, extension, and adduction of limb. Limb describes cone in space
What are some more special movements of synovial joints?
Inversion and eversion of foot. Inversion: sole of foot faces medially. Eversion: sole of foot faces laterally. Protraction and retraction: movement in lateral plane
Protraction: mandible juts out. Retraction: mandible is pulled toward neck
What are some more special movements of synovial joints?
Elevation and depression of mandible. Elevation: lifting body part superiorly (Ex: shrugging shoulders). Depression: lowering body part (Ex: opening jaw).
Opposition: movement of thumb (Ex: touching thumb to tips of other fingers on same
hand or any grasping movement)
Explain Plane Synovial joints
Flat articular surfaces, nonaxial movement (gliding)
Ex: intercarpal joints, intertarsal joints, joints b/t vertebral articular surfaces
Explain HInge joint (synovial joint)
Humerus, Ulna: contains cylinder & trough. Uniaxial movement: Medial /lateral axis, flexion & extension
Ex: elbow joints, interphalangeal joints
Explain Pivot joints (synovial joint)
Ulan, Radius: contains sleeve, (bone & ligament), Axle (rounded bone). Uniaxial movement: vertical axis, rotation.
Ex: proximal radioulnar joints, atlantoaxial jpint
Explain Condylar joint (synovial joint)
Phalanges, metacarpals (oval articular processes) . Biaxial movement: medial/lateral axis (flexion and extension), anterior/posterior axis (adduction & abduction).
Ex: Metacarpophalangeal (knuchle) joints, wrist joints
Explain Saddle joint (synovial)
Metacarpal 1, trapezium (articular surfaces are both concave & convex). Biaxial movemnent: Adduction & Abduction (medial/lateral axis). Flexion & extension (anterior/posterior axis)
Ex: carpometacarpal joints of the thumbs
Explain Ball and Socket joints (synovial)
Scapula , Humerus: cup (socket), spherical head (ball). Multiaxial movement: Flexion & extension (medial/lateral axis). Adduction & abduction (anterior/posterior axis). Rotation (vertical axis)
Ex: shoulder and hip joints
What are the 3 Cs? (knee)
-common injuries involve these
Collateral ligaments, Cruciate ligaments, and Cartilages (menisci)
-Knee absorbs great amount of vertical force; however, it is vulnerable to horizontal blows,
especially laterally blows to extended knee
Explain the knee joint more
-Joint capsule is thin and absent anteriorly
Anteriorly, quadriceps tendon gives rise to three broad ligaments that run from patella to tibia. Medial & lateral patellar retinacula that flank the patellar ligament
• Doctors tap patellar ligament to test knee-jerk reflex
• At least 12 bursae associated with knee joint
Explain the knee joint more
-Intracapsular ligaments reside within capsule, but outside synovial cavity
-Help to prevent anterior-posterior displacement
Anterior cruciate ligament (ACL): Attaches to anterior tibia.Prevents forward sliding of tibia and stops hyperextension of knee. Posterior cruciate ligament (PCL): Attaches to posterior tibia. Prevents backward sliding of tibia and forward sliding of
femur
Explain Cartilage Tears
Cartilage rarely repairs itself. Repaired with arthroscopic surgery. Meniscal transplant possible in younger patients. Perhaps meniscus grown from own stem cells in future
Explain Sprains
-Reinforcing ligaments are stretched or torn
Common sites are ankle, knee, and lumbar region of back. Partial tears repair very slowly because of poor vascularization. Three options if torn completely 1. Ends of ligaments can be sewn together. 2. Replaced with grafts. 3. Just allow time and immobilization for healing
Explain Dislocations (luxations)
Bones forced out of alignment. Accompanied by sprains, inflammation, and difficulty
moving joint. Caused by serious falls or contact sports. Must be reduced to treat
-Subluxation: partial dislocation of a joint