Transport of O2, nutrients, wastes, hormones; Regulation of temperature, pH, fluid volume; Protection against blood loss and infection.
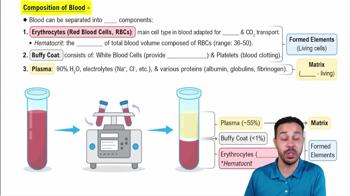
Composition of Blood
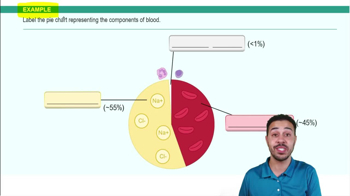
Blood is connective tissue with plasma (nonliving fluid matrix) and formed elements (RBCs, WBCs, platelets).
Hematocrit
Percentage of blood volume occupied by RBCs; normal ~45% (males 47% ± 5%, females 42% ± 5%).
Physical Characteristics of Blood
Sticky, opaque fluid with metallic taste; color varies with O2 content; pH 7.35–7.45; ~8% body weight; volume 5–6 L males, 4–5 L females.
Plasma Composition
About 90% water with dissolved solutes including nutrients, gases, hormones, wastes, and plasma proteins like albumin (60%).
Formed Elements
Include erythrocytes (RBCs), leukocytes (WBCs), and platelets; only WBCs are complete cells.
Erythrocyte Structure
Small (7.5 μm), biconcave, anucleate cells filled with hemoglobin; flexible due to spectrin protein.
Hemoglobin Structure
Protein with four polypeptide chains (2 alpha, 2 beta) each bound to a heme group containing iron that binds O2.
Erythrocyte Function
Transport respiratory gases; each Hb molecule carries 4 O2; RBC contains ~250 million Hb molecules.
Erythropoiesis
Process of RBC formation in red bone marrow; takes ~15 days; regulated by erythropoietin (EPO).
Erythropoietin (EPO)
Hormone from kidneys that stimulates RBC production in response to hypoxia (low O2).
Dietary Requirements for Erythropoiesis
Amino acids, iron (stored as ferritin/hemosiderin, transported by transferrin), vitamin B12, and folic acid.
RBC Life Span and Destruction
Live 100–120 days; old RBCs broken down by macrophages; heme degraded to bilirubin, iron recycled.
Anemia
Condition with low O2-carrying capacity; causes include blood loss, low RBC production, or high RBC destruction.
Polycythemia
Excess RBCs increasing blood viscosity; caused by bone marrow cancer or hypoxia-induced EPO increase.
Leukocytes (WBCs)
Complete cells with nuclei; defend against disease; classified as granulocytes (neutrophils, eosinophils, basophils) and agranulocytes (lymphocytes, monocytes).
Neutrophils
Most abundant WBCs (50–70%); multilobed nucleus; phagocytic bacteria slayers; kill microbes via respiratory burst.
Eosinophils
2–4% of WBCs; bilobed nucleus; red granules; attack parasitic worms; involved in allergies and asthma.
Basophils
Rarest WBCs (0.5–1%); bilobed nucleus; granules contain histamine which promotes inflammation and attracts WBCs.
Lymphocytes
25–45% of WBCs; large nucleus; key in immunity; T cells attack infected cells, B cells produce antibodies.
Monocytes
Largest WBCs (3–8%); kidney-shaped nucleus; differentiate into macrophages; phagocytic and activate lymphocytes.
Platelets
Cell fragments from megakaryocytes; contain clotting chemicals; form temporary platelet plugs in vessel injury.
Intrinsic (clotting factors in blood) and extrinsic (tissue factor outside blood) pathways converge to activate factor X and form prothrombin activator.
Thrombin Role
Converts prothrombin to thrombin, which converts fibrinogen to fibrin forming the clot mesh.
Clot Retraction and Fibrinolysis
Platelets contract to shrink clot; plasmin enzyme dissolves clot after repair.
Blood Transfusions and Typing
Blood groups based on A, B, and Rh antigens; mismatched transfusions cause agglutination and hemolysis.
 Indietro

 2:36