 Back
Blood: Structure, Function, and Clinical Aspects
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Blood: Structure, Function, and Clinical Aspects
Overview of Blood Functions
Blood is a specialized connective tissue that serves as the body's internal transport system. It performs essential functions in transport, regulation, and protection.
Transport: Delivers oxygen and nutrients to cells, removes metabolic wastes, and transports hormones.
Regulation: Maintains body temperature, pH balance, and fluid volume.
Protection: Prevents blood loss through clotting and combats infection via immune cells and proteins.
Composition of Blood
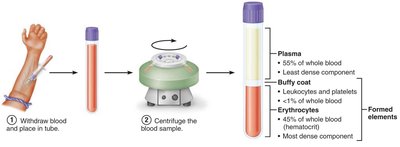
Blood consists of plasma (the liquid matrix) and formed elements (cells and cell fragments). When centrifuged, blood separates into three layers:
Plasma: ~55% of blood; contains water, proteins, nutrients, hormones, and waste products.
Buffy coat: <1% of blood; contains leukocytes (white blood cells) and platelets.
Erythrocytes: ~45% of blood; red blood cells responsible for oxygen transport (hematocrit).
Physical Characteristics and Volume
Blood is more viscous than water and has a metallic taste.
Color varies with oxygen content: bright red (oxygen-rich) to dark red (oxygen-poor).
pH: 7.35–7.45; volume: 5–6 L in males, 4–5 L in females (~8% of body weight).
Blood Plasma
Plasma is a straw-colored, sticky fluid making up about 90% water. It contains over 100 dissolved solutes, including:
Electrolytes: Sodium, potassium, calcium, chloride, bicarbonate, etc.
Plasma proteins: Albumin (60%, maintains osmotic pressure), globulins (36%, transport and immune functions), fibrinogen (4%, clotting).
Nutrients, gases, hormones, wastes, and nonprotein nitrogenous substances.
Formed Elements of Blood
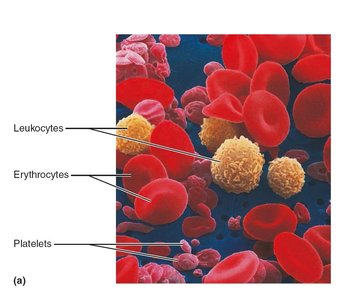
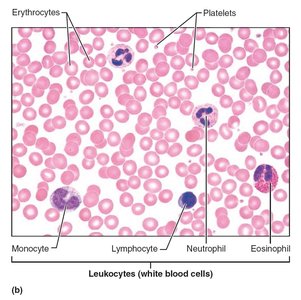
The formed elements include erythrocytes (RBCs), leukocytes (WBCs), and platelets. Most are short-lived and do not divide; they are replaced by stem cells in red bone marrow.
Erythrocytes (Red Blood Cells)
Structure and Function
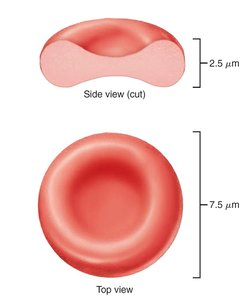
Erythrocytes are small, biconcave, anucleate cells specialized for gas transport. Their shape increases surface area for efficient gas exchange, and they lack mitochondria, so they do not consume the oxygen they carry.
Diameter: ~7.5 μm; thickness: ~2.5 μm.
Filled with hemoglobin (Hb), which binds oxygen and carbon dioxide.
Hemoglobin Structure and Function
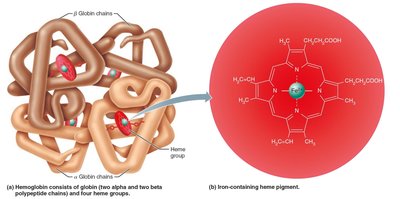
Hemoglobin is a protein composed of four polypeptide chains (two alpha, two beta) each bound to a heme group with a central iron ion. Each iron binds one oxygen molecule, so each Hb can carry four oxygens.
Normal values: Males 13–18 g/100 ml; Females 12–16 g/100 ml.
Oxygen loading in lungs forms oxyhemoglobin (bright red); unloading in tissues forms deoxyhemoglobin (dark red).
About 20% of CO2 binds to Hb, forming carbaminohemoglobin.
Erythropoiesis: Formation of Red Blood Cells
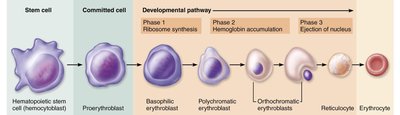
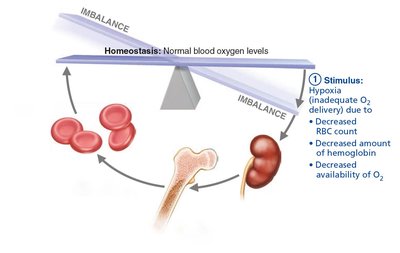
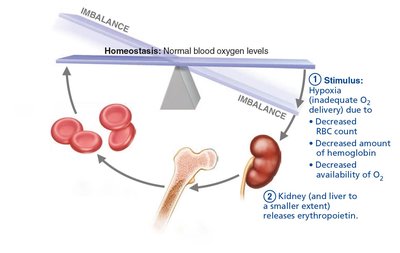
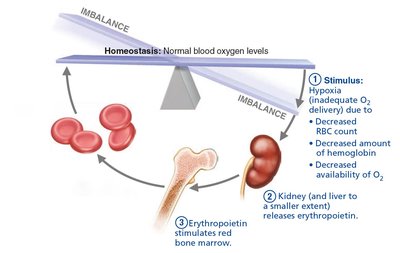
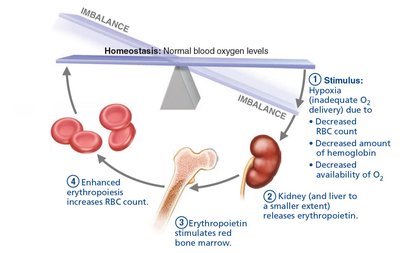
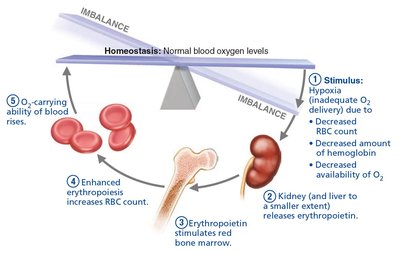
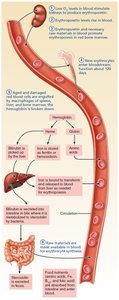
Erythropoiesis occurs in red bone marrow and is regulated by erythropoietin (EPO), a hormone produced by the kidneys in response to hypoxia (low oxygen).
Stages: Hematopoietic stem cell → Myeloid stem cell → Proerythroblast → Basophilic erythroblast → Polychromatic erythroblast → Orthochromatic erythroblast → Reticulocyte → Erythrocyte.
Reticulocyte count is a clinical indicator of RBC production rate.
Regulation of Erythropoiesis
The number of circulating RBCs is tightly regulated to balance oxygen delivery and blood viscosity. EPO release is stimulated by hypoxia due to decreased RBC count, decreased hemoglobin, or reduced oxygen availability.
Testosterone increases EPO production, contributing to higher hematocrit in males.
Dietary requirements: iron, vitamin B12, folic acid, amino acids, lipids, and carbohydrates.
Life Cycle and Fate of Erythrocytes
RBCs live about 100–120 days. Old RBCs are destroyed in the spleen; their components are recycled or excreted.
Iron is stored and reused; heme is degraded to bilirubin (excreted in bile); globin is broken down to amino acids.




Erythrocyte Disorders
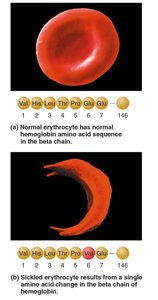
Anemia: Blood's oxygen-carrying capacity is too low. Causes include blood loss, decreased RBC production (iron-deficiency, pernicious, renal, aplastic anemia), or increased RBC destruction (hemolytic anemias, thalassemia, sickle-cell anemia).
Polycythemia: Excess RBCs increase blood viscosity. Can be primary (bone marrow cancer) or secondary (high altitude, EPO doping).
Leukocytes (White Blood Cells)
Structure and Function
Leukocytes are complete cells with nuclei and organelles. They defend the body against infection and foreign substances. They leave the bloodstream via diapedesis and move toward infection sites by chemotaxis.
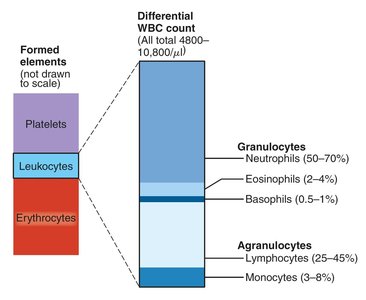
Normal count: 4,800–10,800/μL.
Leukocytosis (>11,000/μL) is a normal response to infection.
Types of Leukocytes
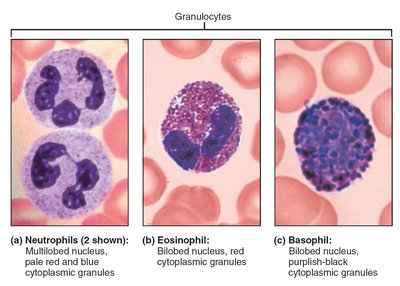
Granulocytes: Neutrophils (50–70%, phagocytic, bacteria slayers), eosinophils (2–4%, attack parasites, modulate allergies), basophils (0.5–1%, release histamine).
Agranulocytes: Lymphocytes (25–45%, immunity—T cells and B cells), monocytes (3–8%, become macrophages).
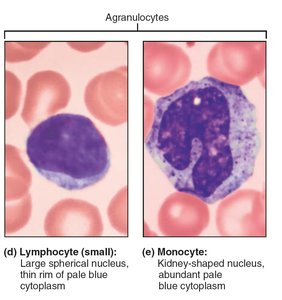
Leukopoiesis: Formation of White Blood Cells
Leukopoiesis is stimulated by interleukins and colony-stimulating factors. Hematopoietic stem cells differentiate into myeloid or lymphoid lines, giving rise to all WBCs.
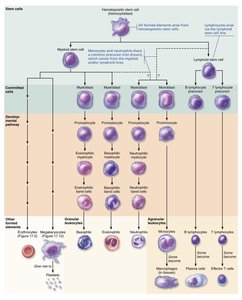
Leukocyte Disorders
Leukopenia: Abnormally low WBC count, often drug-induced.
Leukemias: Cancerous overproduction of abnormal WBCs; classified as acute or chronic, myeloid or lymphocytic.
Infectious mononucleosis: Viral disease (Epstein-Barr virus) causing excess atypical lymphocytes.
Platelets (Thrombocytes)
Structure and Function
Platelets are cell fragments derived from megakaryocytes. They are essential for blood clotting, forming temporary plugs to seal vessel breaks.
Normal count: 150,000–400,000/μL.
Formation (thrombopoiesis) is regulated by thrombopoietin.
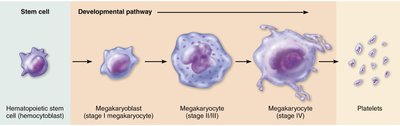
Hemostasis: Prevention of Blood Loss
Steps of Hemostasis
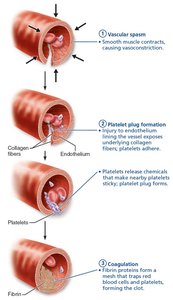
Hemostasis is a rapid, localized process to stop bleeding, involving three steps:
Vascular spasm: Vasoconstriction of damaged vessel.
Platelet plug formation: Platelets adhere to exposed collagen, become activated, and aggregate.
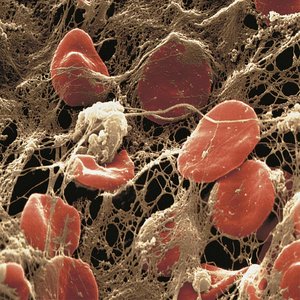
Coagulation: Fibrin forms a mesh that traps blood cells, forming a stable clot.

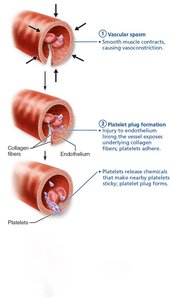
Coagulation Pathways
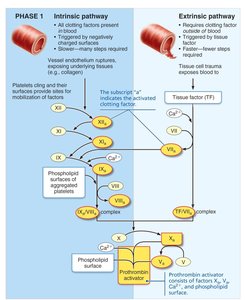
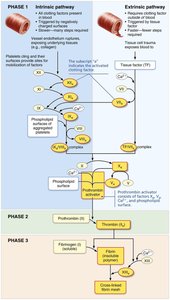
Coagulation involves a cascade of clotting factors, leading to the conversion of fibrinogen to fibrin. There are two pathways:
Intrinsic pathway: Triggered by factors within blood; slower.
Extrinsic pathway: Triggered by tissue factor from damaged tissue; faster.
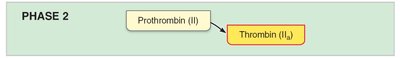
Both pathways converge to activate prothrombin to thrombin, which converts fibrinogen to fibrin.
Clot Retraction and Fibrinolysis
Clot retraction: Platelets contract, pulling wound edges together.
Fibrinolysis: Plasmin digests fibrin, dissolving the clot after repair.
Hemostasis Disorders
Thromboembolic disorders: Unwanted clot formation (thrombus, embolus).
Bleeding disorders: Thrombocytopenia (low platelets), impaired liver function, hemophilia (clotting factor deficiencies).
Disseminated intravascular coagulation (DIC): Both widespread clotting and bleeding.
Blood Transfusion and Blood Groups
ABO and Rh Blood Groups
Blood groups are determined by antigens (agglutinogens) on RBC membranes. The most clinically important are the ABO and Rh systems.
ABO: Type A (A antigen), B (B antigen), AB (both), O (neither). Plasma contains antibodies against absent antigens.
Rh: Rh+ (D antigen present), Rh− (absent). Anti-Rh antibodies form only after exposure.
Transfusion Reactions
Occur if mismatched blood is transfused; recipient antibodies attack donor RBCs, causing agglutination and hemolysis.
Universal donor: Type O; universal recipient: Type AB (with caveats).
Blood Tests and Clinical Assessment
Hematocrit: Percentage of RBCs in blood; low in anemia.
Differential WBC count: Proportions of each WBC type; helps diagnose infections and blood disorders.
Prothrombin time (PT), platelet count: Assess hemostasis.
Comprehensive metabolic panel (CMP), complete blood count (CBC): Assess overall health and organ function.
Developmental Aspects of Blood
Fetal blood cells form in yolk sac, liver, and spleen; red bone marrow becomes primary site by the seventh month.
Fetal hemoglobin (HbF) has higher oxygen affinity than adult hemoglobin (HbA).
Blood diseases increase with age, often due to cardiovascular or immune system disorders.
