 Back
Bones and Skeletal Tissues: Structure, Function, and Development
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Bones and Skeletal Tissues
Introduction
The skeletal system is fundamental to human anatomy and physiology, providing structure, protection, and facilitating movement. Understanding bone anatomy and physiology is essential for diagnosing and treating bone-related diseases such as osteoporosis.
Cartilages and Their Role in the Skeleton
Cartilage Structure and Types
Cartilage is a resilient tissue that forms the initial skeleton in embryos and remains in areas requiring flexibility. It is avascular and lacks nerves, with nutrients supplied by the perichondrium.
Hyaline cartilage: Provides support, flexibility, and resilience; most abundant; found in joints, ribs, respiratory passages, and nose.
Elastic cartilage: Contains elastic fibers; found in external ear and epiglottis.
Fibrocartilage: Contains thick collagen fibers; found in knee menisci, pubic symphysis, and intervertebral discs.
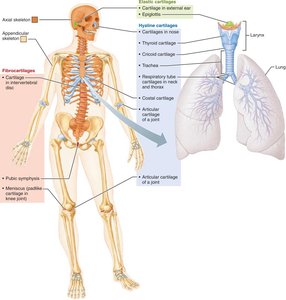
Cartilage Growth
Appositional growth: New matrix is added to the surface by cells in the perichondrium.
Interstitial growth: Chondrocytes within the cartilage divide and secrete new matrix, expanding cartilage from within.
Cartilage growth ends during adolescence.
Functions of Bones
Seven Major Functions
Support: Framework for the body and soft organs.
Protection: Shields brain, spinal cord, and vital organs.
Anchorage: Acts as levers for muscle action.
Mineral storage: Stores calcium and phosphorus.
Blood cell formation: Hematopoiesis occurs in red bone marrow.
Triglyceride storage: Fat stored in bone cavities.
Hormone production: Osteocalcin regulates insulin and energy expenditure.
Classification of Bones
By Location
Axial skeleton: Skull, vertebral column, rib cage.
Appendicular skeleton: Limbs and girdles.
By Shape
Long bones: Longer than wide; e.g., femur, humerus.
Short bones: Cube-shaped; e.g., wrist, ankle; includes sesamoid bones like the patella.
Flat bones: Thin, flat, slightly curved; e.g., sternum, ribs, cranial bones.
Irregular bones: Complex shapes; e.g., vertebrae, hip bones.
Bone Structure
Gross Anatomy: Compact and Spongy Bone
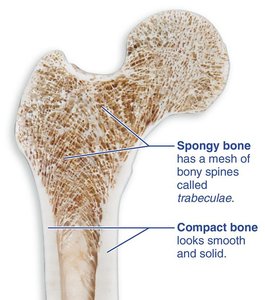
Bones are organs containing multiple tissue types. The two main types of bone tissue are:
Compact bone: Dense, smooth outer layer.
Spongy bone: Honeycomb structure of trabeculae, filled with bone marrow.
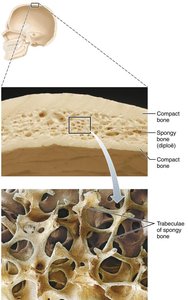
Structure of Short, Irregular, and Flat Bones
Thin plates of spongy bone (diploë) covered by compact bone.
Periosteum covers outside; endosteum covers inside.
Bone marrow is scattered throughout spongy bone.
Hyaline cartilage covers joint surfaces.
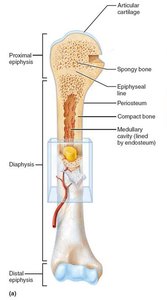
Structure of a Typical Long Bone
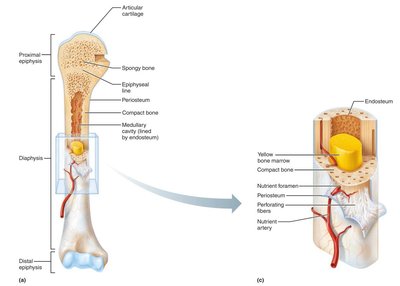
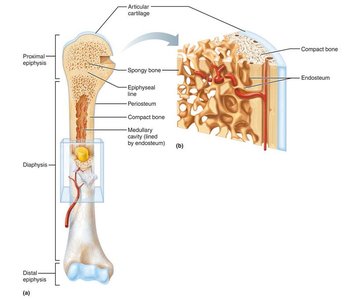
Diaphysis: Shaft; compact bone surrounds medullary cavity (yellow marrow in adults).
Epiphyses: Ends; compact bone externally, spongy bone internally; articular cartilage covers joint surfaces.
Epiphyseal line: Remnant of growth plate.
Membranes: Periosteum (outer), endosteum (inner).
Hematopoietic Tissue in Bones
Red bone marrow: Found in trabecular cavities of spongy bone and diploë of flat bones.
In adults, most active in flat bones and some irregular bones.
Yellow marrow can convert to red marrow if needed.
Bone Markings
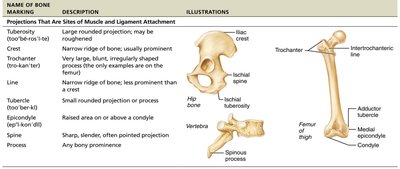
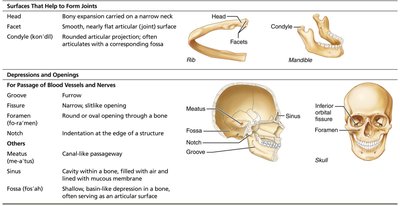
Bone markings are sites for muscle, ligament, and tendon attachment, joint formation, or passage for blood vessels and nerves.
Name of Bone Marking | Description | Illustrations |
|---|---|---|
Tuberosity | Large rounded projection | Hip bone |
Trochanter | Very large, blunt, irregularly shaped process | Femur |
Line | Narrow ridge of bone | Femur |
Spine | Sharp, slender, pointed projection | Vertebra |
Process | Any bony prominence | Spinous process |
Surfaces | Description | Illustrations |
|---|---|---|
Head | Bony expansion on a narrow neck | Rib |
Facet | Smooth, nearly flat articular surface | Condyle |
Depressions and Openings | Description | Illustrations |
Groove | Narrow, slitlike opening | Skull |
Foramen | Round or oval opening | Skull |
Sinus | Cavity within a bone | Skull |
Microscopic Anatomy of Bone
Types of Bone Cells
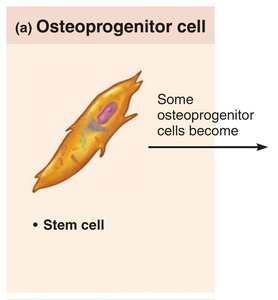
Osteoprogenitor cells: Stem cells in periosteum and endosteum; differentiate into osteoblasts or bone-lining cells.
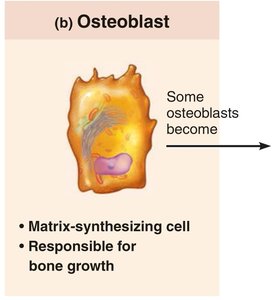
Osteoblasts: Bone-forming cells; secrete osteoid (collagen and calcium-binding proteins).
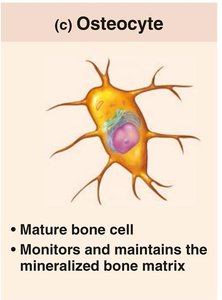
Osteocytes: Mature bone cells; maintain matrix and act as stress sensors.
Bone-lining cells: Flat cells on bone surfaces; maintain matrix.
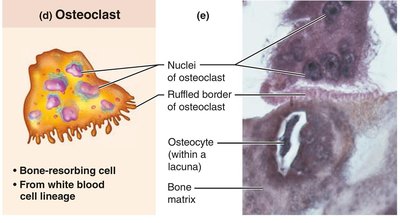
Osteoclasts: Bone-resorbing cells; break down bone matrix.
Microscopic Anatomy of Compact Bone
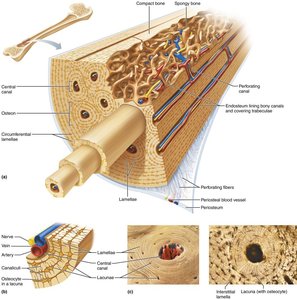
Osteon (Haversian system): Structural unit; cylindrical, parallel to bone axis; composed of concentric lamellae.
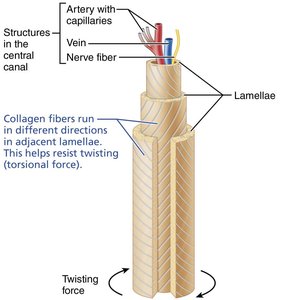
Canals and canaliculi: Central canal contains blood vessels and nerves; canaliculi connect lacunae and allow communication.
Lamellae: Collagen fibers run in different directions in adjacent rings, resisting twisting forces.
Interstitial and circumferential lamellae: Fill gaps and extend around diaphysis.
Microscopic Anatomy of Spongy Bone
Trabeculae align along lines of stress, conferring strength.
No osteons; trabeculae contain lamellae and osteocytes interconnected by canaliculi.
Capillaries in endosteum supply nutrients.
Chemical Composition of Bone
Organic Components
Includes bone cells and osteoid (collagen and ground substance).
Provides tensile strength and flexibility.
Sacrificial bonds in collagen dissipate energy and prevent fractures.
Inorganic Components
Hydroxyapatites (mineral salts) make up 65% of bone mass.
Calcium phosphate crystals provide hardness and resistance to compression.
Bones are strong and durable due to mineral composition.
Bone Development
Ossification (Osteogenesis)
Bone tissue formation begins in the second month of development and continues throughout life.
Endochondral ossification: Bone forms by replacing hyaline cartilage; most bones below the skull.
Intramembranous ossification: Bone develops from fibrous membrane; forms cranial bones and clavicles.
Endochondral Ossification
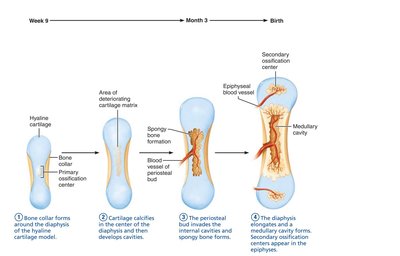
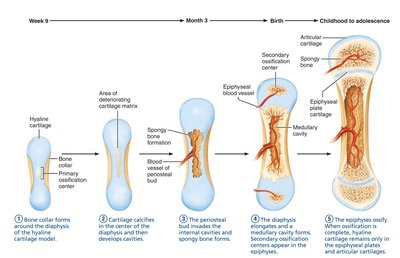
Five main steps: bone collar formation, cartilage calcification, periosteal bud invasion, diaphysis elongation, epiphyses ossification.
Hyaline cartilage remains in epiphyseal plates and articular cartilages.
Intramembranous Ossification
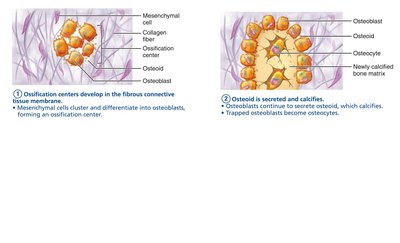
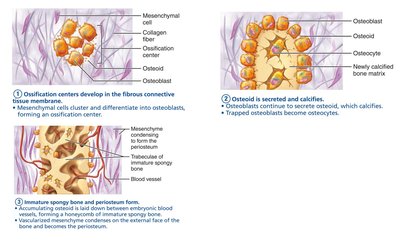
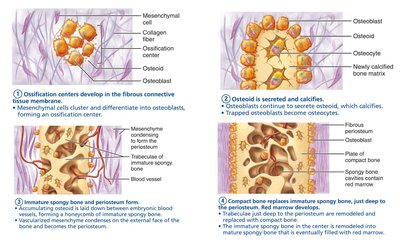
Four steps: formation of ossification centers, secretion and calcification of osteoid, formation of woven bone and periosteum, replacement by lamellar bone and appearance of red marrow.
Postnatal Bone Growth
Growth in Length of Long Bones
Occurs at the epiphyseal plate via interstitial growth.
Epiphyseal plate consists of five zones: resting, proliferation, hypertrophic, calcification, ossification.
Bone lengthening ceases when epiphysis and diaphysis fuse (epiphyseal plate closure).
Growth in Width (Thickness)
Appositional growth increases bone thickness.
Osteoblasts build bone externally; osteoclasts remove bone internally.
Bones thicken in response to stress.
Hormonal Regulation of Bone Growth
Growth hormone stimulates epiphyseal plate activity.
Thyroid hormone modulates growth hormone activity.
Sex hormones induce growth spurts and epiphyseal plate closure.
Bone Remodeling
Bone Remodeling Process
Bone deposit and resorption occur throughout life.
Remodeling units consist of osteoblasts and osteoclasts.
Bone Resorption
Osteoclasts break down bone matrix, releasing calcium into blood.
Regulated by parathyroid hormone (PTH) and immune proteins.
Bone Deposition
Osteoblasts deposit new bone matrix.
Calcification front marks transition between new and old bone.
Control of Remodeling
Hormonal control maintains blood calcium homeostasis.
Mechanical stress determines bone strength and structure (Wolff's law).
Bone Repair
Fracture Classification
Nondisplaced vs. displaced: Position of bone ends.
Complete vs. incomplete: Completeness of break.
Open vs. closed: Whether skin is penetrated.
Common Types of Fractures
Fracture Type | Description |
|---|---|
Comminuted | Bone fragments into three or more pieces; common in older adults. |
Compression | Bone is crushed; common in porous bones. |
Spiral | Ragged break from twisting forces; common in sports. |
Epiphyseal | Epiphysis separates from diaphysis; occurs where cartilage cells are dying. |
Depressed | Broken bone portion pressed inward; typical of skull fracture. |
Greenstick | Bone breaks incompletely; common in children. |
Fracture Treatment and Repair
Reduction (realignment) and immobilization are required.
Repair involves four stages: hematoma formation, fibrocartilaginous callus formation, bony callus formation, bone remodeling.
Bone Disorders
Osteomalacia and Rickets
Soft, weak bones due to poor mineralization.
Rickets in children causes bone deformities; often due to vitamin D deficiency.
Osteoporosis
Bone resorption exceeds deposit; bone mass declines.
Risk factors: age, gender, lack of exercise, poor diet, smoking, genetics, hormone-related conditions.
Treatments: calcium, vitamin D, exercise, hormone therapy, bisphosphonates, denosumab.
Prevention: adequate calcium, reduced alcohol, weight-bearing exercise.
Paget’s Disease
Excessive, haphazard bone deposit and resorption.
High ratio of spongy to compact bone; reduced mineralization.
Drug therapies: bisphosphonates, calcitonin.
Developmental and Age-Related Aspects of Bone
Embryonic and Fetal Development
Skeleton ossifies predictably; fetal age can be determined by X-rays.
Most long bones begin ossifying by 8 weeks; primary ossification centers by week 12.
Birth to Adulthood
Epiphyseal plates persist through childhood and adolescence.
Complete ossification and cessation of skeletal growth by age 25.
Age-Related Changes
Bone formation exceeds resorption in youth; balanced in young adults; resorption exceeds formation in older adults.
Bone density, mineralization, and healing decrease with age; genetics play a major role.
