 Back
Electrical and Mechanical Events of the Heart: ANP Study Guide
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Electrical Events of the Heart
Intrinsic Conduction System
The heart's rhythm is primarily set by its intrinsic conduction system, which consists of specialized autorhythmic cells that initiate and distribute electrical impulses. This system ensures coordinated depolarization and contraction of cardiac muscle, independent of nervous system input, though the rhythm can be modified by the autonomic nervous system.
Gap junctions allow rapid transmission of electrical signals between cardiac cells.
Autorhythmic cells (pacemaker cells) generate and propagate action potentials throughout the heart.
Pacemaker Cell Action Potentials
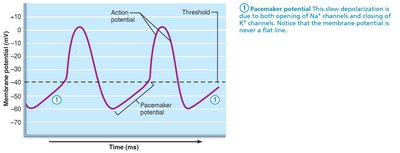
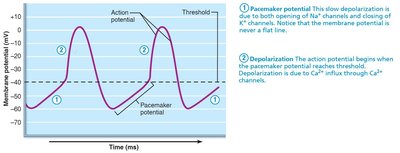
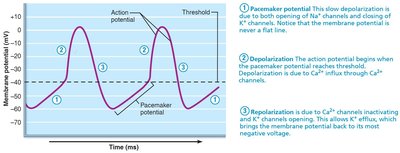
Pacemaker cells, primarily located in the sinoatrial (SA) node, exhibit unique action potentials characterized by three phases:
Pacemaker potential: Slow depolarization due to opening of Na+ channels and closing of K+ channels. The membrane potential never remains flat.
Depolarization: Ca2+ channels open at threshold (~-40 mV), causing a rapid influx of Ca2+ and the rising phase of the action potential.
Repolarization: Ca2+ channels inactivate and K+ channels open, allowing K+ efflux and returning the cell to its most negative voltage.
Sequence of Excitation in the Heart
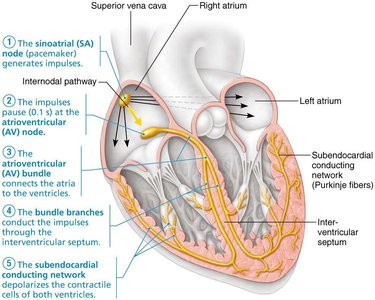
The electrical impulse travels through the heart in a specific sequence, ensuring proper contraction:
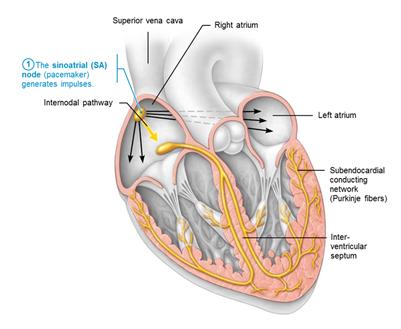
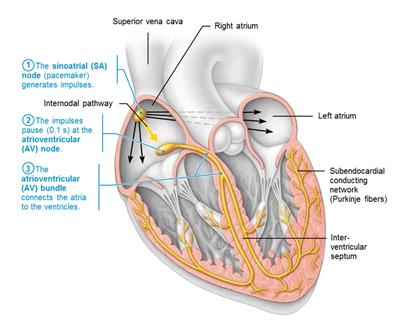
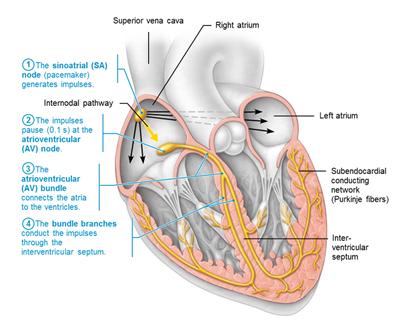
Sinoatrial (SA) node: Located in the right atrial wall; acts as the pacemaker, generating impulses about 75 times per minute.
Atrioventricular (AV) node: Located in the inferior interatrial septum; delays impulses by ~0.1 seconds, allowing atrial contraction before ventricular contraction.
Atrioventricular (AV) bundle (Bundle of His): Only electrical connection between atria and ventricles.
Right and left bundle branches: Carry impulses through the interventricular septum toward the apex.
Subendocardial conducting network (Purkinje fibers): Depolarizes the contractile cells of both ventricles.
Extrinsic Innervation of the Heart
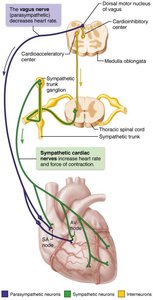
The autonomic nervous system (ANS) modifies the heart's basic rhythm via cardiac centers in the medulla oblongata:
Cardioacceleratory center: Sends sympathetic signals to increase heart rate and force of contraction.
Cardioinhibitory center: Sends parasympathetic signals via the vagus nerve to decrease heart rate.
Action Potentials of Contractile Cardiac Muscle Cells
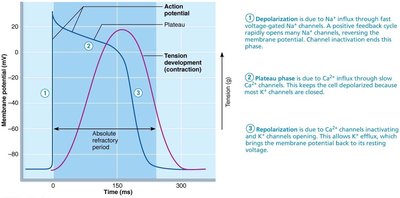
Contractile muscle fibers are responsible for the heart's pumping action. Their action potentials differ from those in skeletal muscle, featuring a plateau phase:
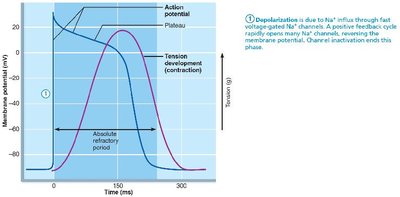
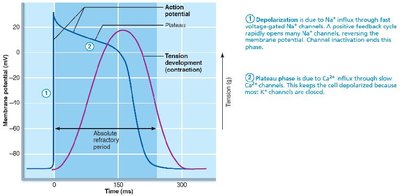
Depolarization: Fast voltage-gated Na+ channels open, causing rapid influx and rising phase of the action potential.
Plateau phase: Slow Ca2+ channels open, prolonging depolarization and resulting in a plateau.
Repolarization: Ca2+ channels close, K+ channels open, and the cell returns to resting membrane potential.
Electrocardiography (ECG/EKG)
Principles of ECG
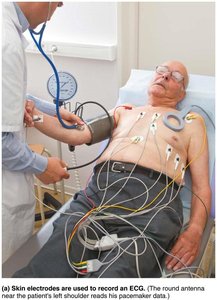
An electrocardiogram (ECG) is a graphic recording of the heart's electrical activity, representing the composite of all action potentials at a given time. Electrodes are placed at various points on the body to measure voltage differences.
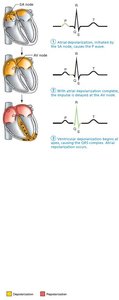
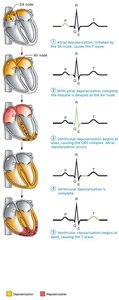
P wave: Depolarization of the SA node and atria.
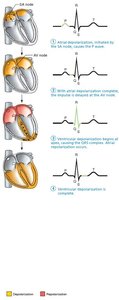
QRS complex: Ventricular depolarization and atrial repolarization.
T wave: Ventricular repolarization.
P-R interval: Beginning of atrial excitation to beginning of ventricular excitation.
S-T segment: Entire ventricular myocardium depolarized.
Q-T interval: Beginning of ventricular depolarization through ventricular repolarization.
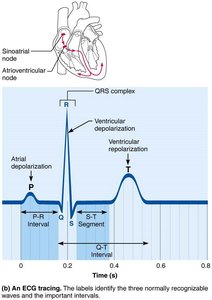
Sequence of Depolarization and Repolarization Related to ECG Waves
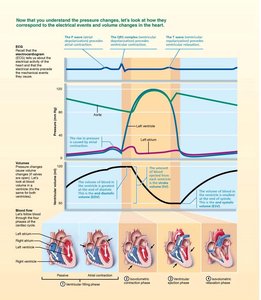
The ECG tracing reflects the sequence of electrical events in the heart, corresponding to the depolarization and repolarization of atria and ventricles.

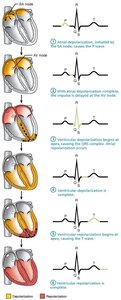
Normal and Abnormal ECG Tracings
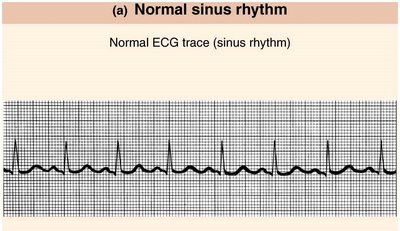
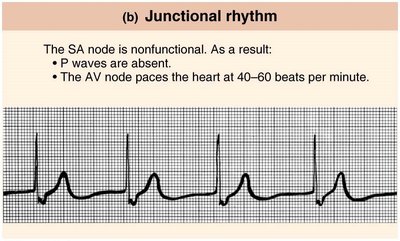
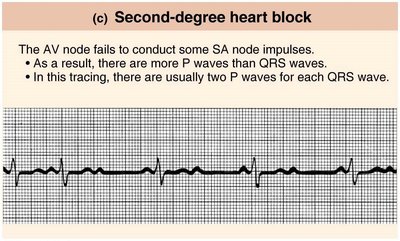
ECG tracings can reveal normal sinus rhythm as well as various arrhythmias:
Normal sinus rhythm: Regular, consistent ECG trace.
Junctional rhythm: SA node nonfunctional; AV node paces the heart, P waves absent.
Second-degree heart block: AV node fails to conduct some SA node impulses; more P waves than QRS waves.
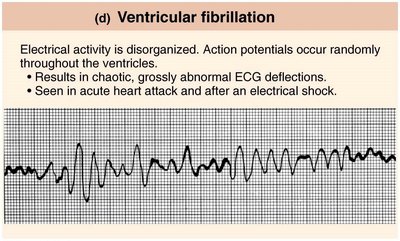
Ventricular fibrillation: Disorganized electrical activity; chaotic, abnormal ECG deflections.
Mechanical Events of the Heart
The Cardiac Cycle
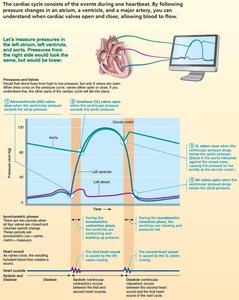
The cardiac cycle describes the sequence of mechanical events during one heartbeat, including systole (contraction) and diastole (relaxation). It consists of three main phases:
Ventricular filling: Blood flows passively from atria to ventricles; atrial contraction pushes remaining blood into ventricles.
Isovolumetric contraction: Ventricles contract with all valves closed; pressure rises until SL valves open.
Isovolumetric relaxation: Ventricles relax; SL valves close, AV valves open when atrial pressure exceeds ventricular pressure.
Heart Sounds
Heart sounds are produced by the closing of heart valves:
First sound (lub): Closing of AV valves at the beginning of ventricular systole.
Second sound (dup): Closing of SL valves at the beginning of ventricular diastole.
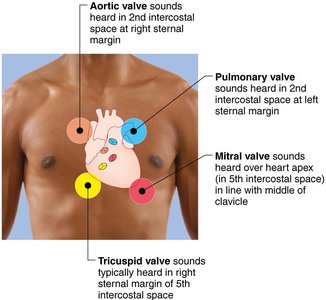
Valve sounds can be auscultated at specific thoracic locations.
Regulation of Cardiac Output
Cardiac Output and Its Regulation
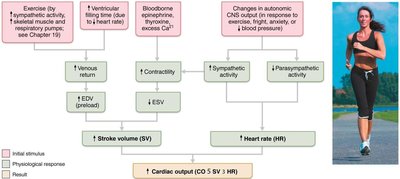
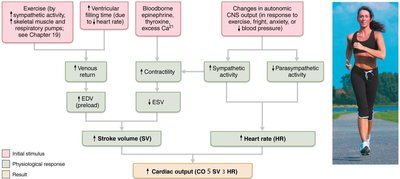
Cardiac output (CO) is the amount of blood pumped by each ventricle per minute. It is determined by heart rate (HR) and stroke volume (SV):
Formula:
Normal resting CO is about 5.25 L/min.
Cardiac reserve is the difference between resting and maximal CO.
Regulation of Stroke Volume
Stroke volume is regulated by three main factors:
Preload: Degree of stretch of cardiac muscle before contraction; increased by venous return.
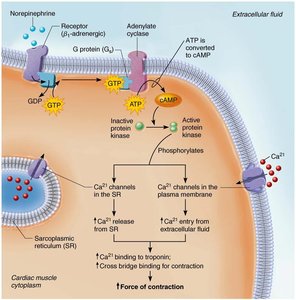
Contractility: Contractile strength at a given muscle length; increased by sympathetic stimulation and positive inotropic agents.
Afterload: Back pressure exerted by arterial blood; increased afterload reduces SV.
Mathematically:
Regulation of Heart Rate
Heart rate is regulated by:
Autonomic nervous system: Sympathetic stimulation increases HR; parasympathetic stimulation decreases HR.
Chemicals: Hormones (epinephrine, thyroxine) and ions (Ca2+, K+) affect HR.
Other factors: Age, gender, exercise, and body temperature.
Clinical and Developmental Aspects
Homeostatic Imbalances
Arrhythmias: Irregular heart rhythms due to defects in the conduction system.
Heart block: Impaired conduction through the AV node; may require artificial pacemaker.
Congestive heart failure (CHF): Inadequate cardiac output due to weakened myocardium.
Congenital heart defects: Most common birth defects; may involve mixing of blood or narrowed valves/vessels.
Developmental Aspects
The heart develops from mesoderm, forming a four-chambered structure by day 35 of embryonic development.
Fetal heart structures (foramen ovale, ductus arteriosus) bypass pulmonary circulation and close at birth.
Age-related changes include valve sclerosis, reduced cardiac reserve, fibrosis, and atherosclerosis.
Additional info: This guide covers the electrical and mechanical events of the heart, including conduction system, action potentials, ECG interpretation, cardiac cycle, regulation of cardiac output, and clinical/developmental aspects, as relevant to ANP college course chapters.
