 Back
Flow, Pressure, and Resistance in the Cardiovascular System: Regulation and Homeostasis
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Flow, Pressure, and Resistance in the Cardiovascular System
Definitions and Fundamental Concepts
The cardiovascular system relies on the coordinated interaction of blood flow, blood pressure, and resistance to ensure efficient circulation throughout the body. Understanding these terms is essential for grasping how blood is transported and regulated.
Blood Flow: The volume of blood moving through a vessel, organ, or the entire circulation in a given period (ml/min). For the entire vascular system, it is equivalent to cardiac output (CO). While overall flow is relatively constant at rest, it varies at the organ level based on metabolic needs.
Blood Pressure (BP): The force per unit area exerted on the wall of a blood vessel by the blood, measured in mm Hg. Systemic arterial BP is typically measured in large arteries near the heart. The pressure gradient drives blood from higher to lower pressure areas.
Resistance (Peripheral Resistance): The opposition to blood flow, primarily due to friction between blood and vessel walls. It is mainly determined by blood viscosity, total vessel length, and vessel diameter.
Determinants of Resistance
Blood Viscosity: The thickness or stickiness of blood, influenced by formed elements and plasma proteins. Increased viscosity raises resistance.
Total Blood Vessel Length: The longer the vessel, the greater the resistance encountered.
Blood Vessel Diameter: The most significant factor affecting resistance. Resistance varies inversely with the fourth power of the vessel radius (). Small changes in diameter cause large changes in resistance. For example, doubling the radius decreases resistance to 1/16 of its original value.
Laminar flow describes how fluid near the vessel wall moves more slowly than in the center. Abrupt changes in diameter or obstructions (e.g., atherosclerotic plaques) can cause turbulent flow, increasing resistance.
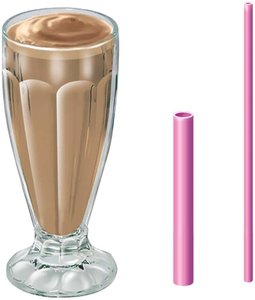
Example: Drinking a thick milkshake through a narrow straw is much harder than through a wide straw, illustrating how vessel diameter affects resistance.
Relationship Between Flow, Pressure, and Resistance
Blood flow (F) is directly proportional to the pressure gradient (ΔP) and inversely proportional to resistance (R):
If ΔP increases, blood flow increases.
If R increases, blood flow decreases.
The relationship is expressed as:
Because vessel diameter can change rapidly, resistance is the most important factor influencing local blood flow.
Systemic Blood Pressure
Pressure Changes Throughout the Circulation
The heart's pumping action generates blood flow, and pressure results when flow is opposed by resistance. Systemic pressure is highest in the aorta and declines throughout the vascular pathway, with the steepest drop in the arterioles.
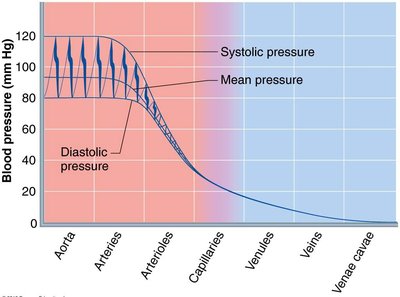
Figure: Blood pressure is highest in the aorta and decreases through arteries, arterioles, capillaries, veins, and is lowest in the venae cavae.
Arterial Blood Pressure
Arterial BP is determined by:
Elasticity (compliance) of arteries near the heart
Volume of blood forced into arteries at any time
Blood pressure near the heart is pulsatile, rising and falling with each heartbeat.
Systolic Pressure: Pressure during ventricular contraction (average 120 mm Hg in adults).
Diastolic Pressure: Lowest aortic pressure during heart relaxation (rest).
Pulse Pressure: Difference between systolic and diastolic pressure.
Mean Arterial Pressure (MAP): The pressure that propels blood to tissues. Calculated as:
Pulse pressure and MAP decline with increasing distance from the heart.
Clinical Monitoring of Circulatory Efficiency
Vital Signs: Pulse, blood pressure, respiratory rate, and body temperature.
Pulse Points: Sites where the pulse is easily palpated, such as the radial artery at the wrist.
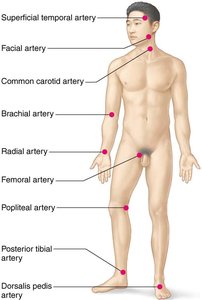
Figure: Common pulse points include the superficial temporal, facial, carotid, brachial, radial, femoral, popliteal, posterior tibial, and dorsalis pedis arteries.
Measuring Blood Pressure
Systemic arterial BP is measured indirectly using a sphygmomanometer and stethoscope (auscultatory method).
Systolic pressure: Pressure when sounds first occur as blood starts to spurt through the artery (normally <120 mm Hg).
Diastolic pressure: Pressure when sounds disappear as the artery is no longer constricted (normally <80 mm Hg).
Capillary and Venous Blood Pressure
Capillary Pressure: Ranges from 35 mm Hg at the start to ~17 mm Hg at the end of the capillary bed. Low pressure prevents capillary rupture and allows for filtration into tissues.
Venous Pressure: Low and steady (about 15 mm Hg), requiring adaptations for venous return.
Muscular Pump: Skeletal muscle contractions "milk" blood toward the heart, with valves preventing backflow.
Respiratory Pump: Pressure changes during breathing move blood toward the heart.
Sympathetic Venoconstriction: Smooth muscle constriction pushes blood toward the heart.
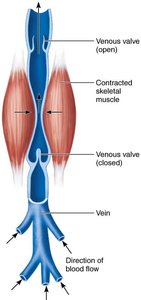
Figure: The muscular pump mechanism, showing how contracted skeletal muscles and venous valves facilitate blood flow toward the heart.
Regulation of Blood Pressure
Major Factors Affecting Blood Pressure
Blood pressure is regulated by the heart, blood vessels, and kidneys, under the supervision of the brain. The three main factors are:
Cardiac Output (CO)
Peripheral Resistance (PR)
Blood Volume
Blood pressure varies directly with CO, PR, and blood volume:
Since , then:
Any increase in stroke volume (SV), heart rate (HR), or resistance (R) will increase MAP.
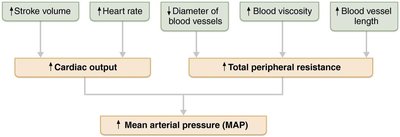
Figure: Factors such as increased stroke volume, heart rate, blood viscosity, and vessel length raise mean arterial pressure (MAP).
Short-Term Regulation: Neural Controls
Neural mechanisms regulate peripheral resistance and blood distribution via reflex arcs involving the cardiovascular center (medulla), baroreceptors, chemoreceptors, and higher brain centers.
Baroreceptor Reflexes: Located in carotid sinuses, aortic arch, and large arteries. Increased BP stimulates baroreceptors, leading to vasodilation and decreased cardiac output, lowering BP. Decreased BP triggers vasoconstriction and increased CO, raising BP.
Chemoreceptor Reflexes: Detect changes in CO2, pH, or O2 and adjust BP by influencing heart rate and vessel constriction.
Higher Brain Centers: The hypothalamus and cortex can modify BP during stress, exercise, or temperature changes.
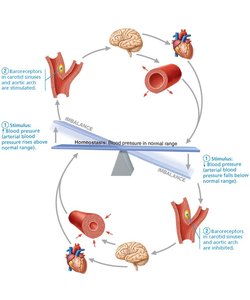
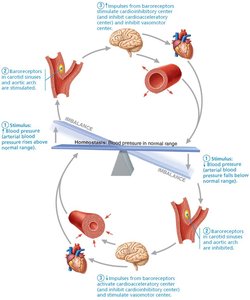
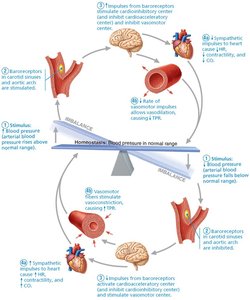
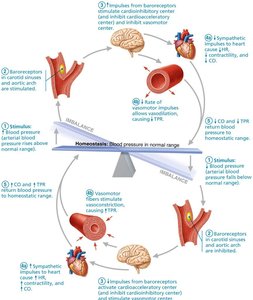
Figures: The sequence of baroreceptor reflexes that help maintain blood pressure homeostasis in response to changes in arterial pressure.
Short-Term Regulation: Hormonal Controls
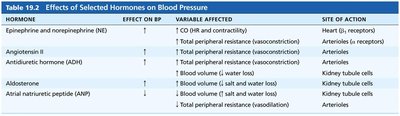
Hormones regulate BP by altering peripheral resistance or blood volume:
Epinephrine and Norepinephrine: Increase CO and vasoconstriction.
Angiotensin II: Potent vasoconstrictor.
Antidiuretic Hormone (ADH): High levels cause vasoconstriction and water retention.
Atrial Natriuretic Peptide (ANP): Decreases BP by promoting salt and water loss.
Hormone | Effect on BP | Variable Affected | Site of Action |
|---|---|---|---|
Epinephrine and norepinephrine (NE) | ↑ | CO (HR and contractility) | Heart (β1 receptors) |
Angiotensin II | ↑ | Total peripheral resistance (vasoconstriction) | Arterioles |
Antidiuretic hormone (ADH) | ↑ | Total peripheral resistance (vasoconstriction) | Arterioles |
Aldosterone | ↑ | Blood volume (salt and water loss) | Kidney tubule cells |
Atrial natriuretic peptide (ANP) | ↓ | Blood volume (salt and water loss) | Kidney tubule cells |
Long-Term Regulation: Renal Mechanisms
Long-term BP regulation is achieved by the kidneys, which control blood volume through two mechanisms:
Direct Renal Mechanism: Increased BP or blood volume leads to increased urine output, reducing BP. Decreased BP or volume causes water conservation, raising BP.
Indirect Renal Mechanism (Renin-Angiotensin-Aldosterone): Low BP triggers renin release, leading to angiotensin II formation, which increases BP by vasoconstriction, stimulating aldosterone and ADH release, and increasing thirst.
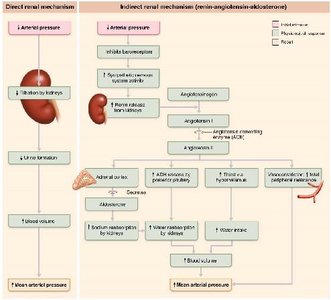
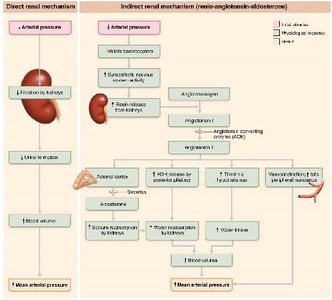
Figures: Flowcharts illustrating direct and indirect (hormonal) mechanisms for renal control of blood pressure.
Homeostatic Imbalances in Blood Pressure
Hypertension
Definition: Sustained arterial pressure of 140/90 mm Hg or higher.
Primary Hypertension: 90% of cases; no identifiable cause. Risk factors include heredity, diet, obesity, age, diabetes, stress, and smoking. Managed by lifestyle changes and antihypertensive drugs.
Secondary Hypertension: Less common; due to identifiable disorders (e.g., kidney disease, endocrine disorders). Treatment targets the underlying cause.
Consequences: Major cause of heart failure, vascular disease, renal failure, and stroke. Prolonged hypertension damages blood vessels and the heart.
Hypotension
Definition: Low blood pressure below 90/60 mm Hg. Usually not a concern unless it causes inadequate tissue perfusion.
Types:
Orthostatic Hypotension: Temporary drop in BP upon standing.
Chronic Hypotension: May indicate poor nutrition or endocrine disorders.
Acute Hypotension: Important sign of circulatory shock.
Circulatory Shock
Definition: Condition where blood vessels are inadequately filled, leading to insufficient blood flow to meet tissue needs.
Types:
Hypovolemic Shock: Due to large-scale blood loss.
Vascular Shock: Due to extreme vasodilation and decreased resistance.
Cardiogenic Shock: Due to heart failure.
Summary of Blood Pressure Regulation
The goal of blood pressure regulation is to maintain adequate tissue perfusion without causing damage to blood vessels. Both short-term (neural and hormonal) and long-term (renal) mechanisms work together to achieve this balance.
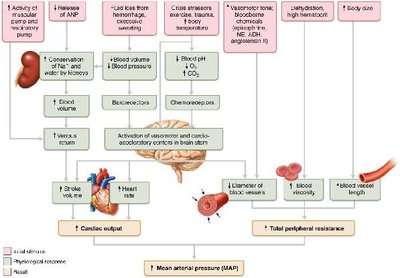
Figure: Summary diagram of factors that increase mean arterial pressure (MAP).
