Back
The Respiratory System: Structure, Function, and Regulation
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
The Respiratory System
Overview and Functional Anatomy
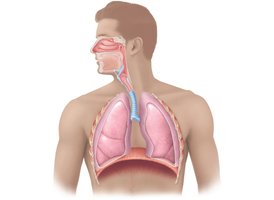
The respiratory system is responsible for the exchange of gases (oxygen and carbon dioxide) between the body and the environment. It consists of a series of organs and structures that facilitate breathing and gas exchange.
Major organs: Nose, nasal cavity, paranasal sinuses, pharynx, larynx, trachea, bronchi and their branches, lungs, and alveoli.
Primary functions: Air conduction, gas exchange, sound production, olfaction, and protection against pathogens and particulates.
Upper Respiratory System
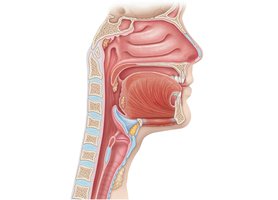
The upper respiratory tract includes the nose, nasal cavity, paranasal sinuses, and pharynx. These structures filter, warm, and moisten incoming air and serve as a passageway for airflow.
Nasal cavity: Lined with mucosa, contains nasal conchae to increase surface area and turbulence.
Pharynx: Divided into nasopharynx, oropharynx, and laryngopharynx; serves as a pathway for both air and food.
Larynx and Voice Production
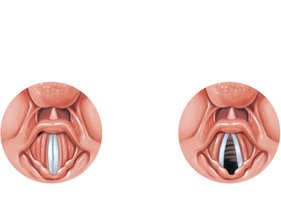
The larynx (voice box) is involved in sound production and protects the lower airways. The vocal folds (cords) vibrate to produce sound as air passes through the glottis.
Pitch: Determined by the length and tension of the vocal cords.
Loudness: Depends on the force of air passing through the cords.
Sound quality: Enhanced by the pharynx, oral, nasal, and sinus cavities.
Lower Respiratory System: Conducting and Respiratory Zones
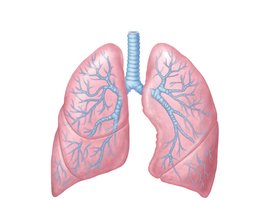
The lower respiratory tract includes the larynx, trachea, bronchi, bronchioles, and lungs. It is divided into the conducting zone (air passageways) and the respiratory zone (site of gas exchange).
Conducting zone: Trachea to terminal bronchioles; functions as air conduits.
Respiratory zone: Respiratory bronchioles, alveolar ducts, and alveoli; site of gas exchange.
Alveoli and Gas Exchange
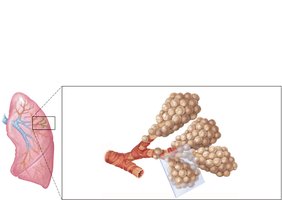
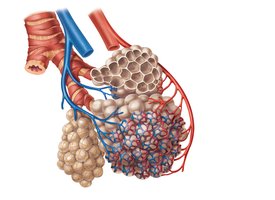
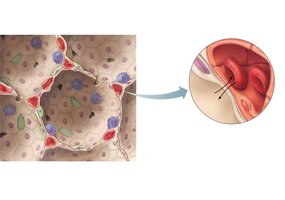
Alveoli are tiny air sacs in the lungs where gas exchange occurs. Approximately 300 million alveoli provide a large surface area for efficient diffusion of gases.
Alveolar structure: Clusters of alveoli are surrounded by capillaries for gas exchange.
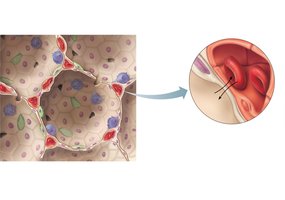
Respiratory membrane: Formed by alveolar and capillary walls; thin for rapid diffusion.
Pleurae and Thoracic Cavity
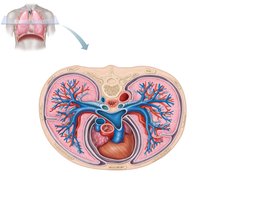
The lungs are enclosed by pleural membranes: the parietal pleura (lining the thoracic cavity) and the visceral pleura (covering the lungs). The pleural cavity contains fluid to reduce friction during breathing.
Mechanics of Breathing (Pulmonary Ventilation)
Phases of Breathing
Pulmonary ventilation consists of two phases: inspiration (air in) and expiration (air out). Breathing is driven by pressure changes in the thoracic cavity.
Inspiration: Active process; diaphragm and external intercostals contract, thoracic volume increases, intrapulmonary pressure drops, air flows in.
Expiration: Passive process during quiet breathing; muscles relax, thoracic volume decreases, intrapulmonary pressure rises, air flows out.
Forced expiration: Active process using abdominal and internal intercostal muscles.
Pressure Relationships
Atmospheric pressure (Patm): Pressure exerted by air around the body (760 mm Hg at sea level).
Intrapulmonary pressure (Ppul): Pressure in alveoli; fluctuates with breathing, equalizes with Patm.
Intrapleural pressure (Pip): Pressure in pleural cavity; always negative relative to Patm and Ppul.
Transpulmonary pressure: Difference between Ppul and Pip; keeps lungs inflated.
Key equation:
Physical Factors Influencing Pulmonary Ventilation
Airway resistance: Usually low due to large airway diameters and extensive branching.
Alveolar surface tension: Reduced by surfactant (produced by type II alveolar cells), preventing alveolar collapse.
Lung compliance: Measure of lung expandability; decreased by fibrosis, reduced surfactant, or thoracic cage rigidity.
Pulmonary Function Tests
Respiratory Volumes and Capacities
Pulmonary function is assessed using a spirometer, which measures respiratory volumes and capacities.
Tidal Volume (TV): Air inhaled/exhaled per breath (500 ml average adult).
Inspiratory Reserve Volume (IRV): Additional air inhaled after normal inspiration.
Expiratory Reserve Volume (ERV): Additional air exhaled after normal expiration.
Residual Volume (RV): Air remaining in lungs after forced expiration.
Vital Capacity (VC): Maximum air exhaled after maximum inhalation ().
Total Lung Capacity (TLC): Total air in lungs after maximum inspiration ().
Dead space: Volume of air not involved in gas exchange (anatomical and alveolar dead space).
Gas Exchange
Composition of Alveolar Gas
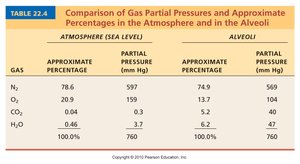
Alveolar air differs from atmospheric air due to gas exchange, humidification, and mixing. The table below compares the partial pressures and percentages of gases in the atmosphere and alveoli.
Gas | Atmosphere (%) | Atmosphere (mm Hg) | Alveoli (%) | Alveoli (mm Hg) |
|---|---|---|---|---|
N2 | 78.6 | 597 | 74.9 | 569 |
O2 | 20.9 | 159 | 13.7 | 104 |
CO2 | 0.04 | 0.3 | 5.2 | 40 |
H2O | 0.46 | 3.7 | 6.2 | 47 |
Total | 100.0 | 760 | 100.0 | 760 |
External and Internal Respiration
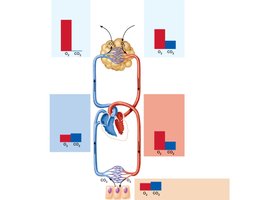
External respiration: Exchange of O2 and CO2 between alveoli and blood, driven by partial pressure gradients.
Internal respiration: Exchange of gases between blood and tissues; O2 diffuses into tissues, CO2 into blood.
Ventilation-perfusion coupling: Matching of air flow and blood flow for efficient gas exchange.
Control of Respiration
Neural Mechanisms
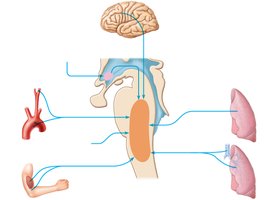
Breathing is regulated by respiratory centers in the medulla and pons. The ventral respiratory group (VRG) generates the basic rhythm, while the dorsal respiratory group (DRG) integrates sensory input and modifies the rhythm.
Rate: 12–15 breaths per minute in adults.
Depth and rate: Adjusted in response to chemical and emotional factors.
Chemical and Other Factors Affecting Breathing
CO2: Most potent stimulus; increased CO2 (hypercapnia) increases ventilation, decreased CO2 (hypocapnia) depresses it.
O2: Significant only when arterial PO2 drops below 60 mm Hg.
pH: Decreased pH stimulates increased ventilation.
Other factors: Emotions, pain, temperature, pulmonary irritants, and stretch receptors.
Respiratory Adjustments
Exercise
During exercise, ventilation increases (hyperpnea) to meet metabolic demands. Blood gas levels (CO2, O2, pH) remain relatively constant due to efficient regulation.
High Altitude
Rapid ascent to high altitude can cause acute mountain sickness (AMS), with symptoms such as headache, shortness of breath, and nausea. Severe cases may result in cerebral or pulmonary edema.
Diving
Underwater pressure increases with depth, compressing the lungs. Breathing compressed air is necessary, but rapid ascent can cause barotrauma or decompression sickness ("the bends") due to nitrogen bubble formation.

Homeostatic Imbalances of the Respiratory System
Chronic Obstructive Pulmonary Disease (COPD)
COPD includes chronic bronchitis and emphysema, characterized by irreversible airflow limitation, dyspnea, coughing, and frequent infections. Most patients have a history of smoking.
Asthma
Asthma is marked by airway inflammation, bronchospasms, and increased mucus production, leading to wheezing, coughing, and chest tightness. It is often triggered by allergens and involves immune responses.
Tuberculosis
Tuberculosis is an infectious disease caused by Mycobacterium tuberculosis. Symptoms include fever, night sweats, weight loss, and a persistent cough. Treatment requires long-term antibiotics.
Lung Cancer
Lung cancer is the leading cause of cancer death in North America. Most cases are linked to smoking. Major types include squamous cell carcinoma, adenocarcinoma, and small cell carcinoma.
Cystic Fibrosis
Cystic fibrosis is a genetic disorder caused by mutations in the CFTR gene, leading to thick, sticky mucus in the lungs, frequent infections, and progressive lung damage.