 Back
The Small and Large Intestine: Structure, Function, and Digestive Processes
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
The Small Intestine
Gross Anatomy of the Small Intestine
The small intestine is the principal organ for digestion and absorption of nutrients. It extends from the pyloric sphincter to the ileocecal valve, measuring approximately 2–4 meters in length and 2.5–4 cm in diameter. The small intestine is subdivided into three regions: the duodenum, jejunum, and ileum.
Duodenum: The first segment (~25 cm), mostly retroperitoneal, curves around the head of the pancreas.
Jejunum: The middle segment (~2.5 m), attached posteriorly by mesentery.
Ileum: The final segment (~3.6 m), also attached by mesentery, joins the large intestine at the ileocecal valve.
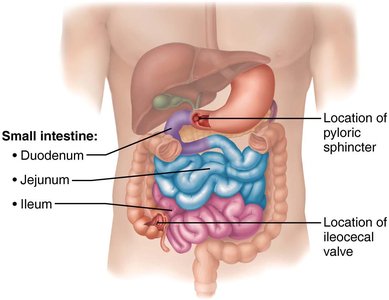
Blood supply is provided by the superior mesenteric artery, and venous drainage occurs via the hepatic portal system. The nerve supply includes parasympathetic fibers from the vagus nerve and sympathetic fibers from thoracic splanchnic nerves.
Relationship to Accessory Organs
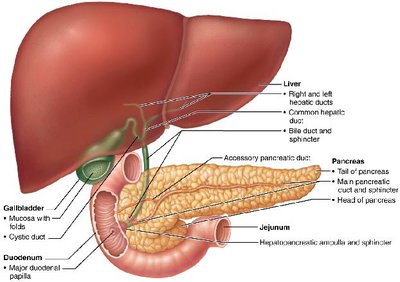
The duodenum receives secretions from the liver, gallbladder, and pancreas, which are essential for digestion. The liver produces bile, the gallbladder stores and releases bile, and the pancreas provides digestive enzymes and bicarbonate.
Microscopic Anatomy and Structural Modifications
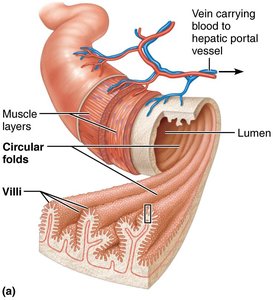
The small intestine is highly specialized for absorption, with several structural modifications that increase its surface area approximately 600-fold to about 200 m2:
Circular folds (plicae circulares): Permanent folds (~1 cm deep) that force chyme to spiral through the lumen, slowing its movement and increasing absorption time.
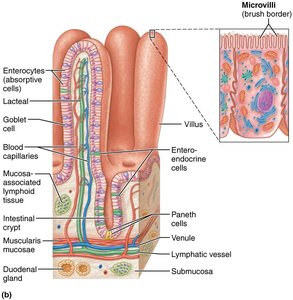
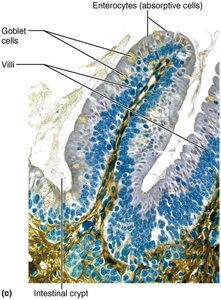
Villi: Fingerlike projections (~1 mm high) of the mucosa containing a dense capillary bed and a lymphatic capillary (lacteal) for nutrient absorption.
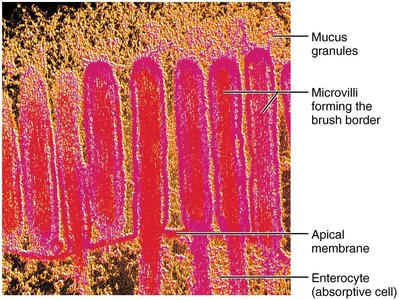
Microvilli: Cytoplasmic extensions of enterocytes forming the brush border, which contains membrane-bound enzymes for final digestion of carbohydrates and proteins.
Cell Types in the Small Intestine
Enterocytes: Absorptive cells with microvilli; absorb nutrients and electrolytes (in villi) and secrete intestinal juice (in crypts).
Goblet cells: Secrete mucus for lubrication and protection.
Enteroendocrine cells: Release hormones (e.g., CCK, secretin) that regulate digestion.
Paneth cells: Secrete antimicrobial agents (defensins, lysozyme) to protect against bacteria.
Stem cells: Continuously divide to replenish the epithelium (renewed every 2–4 days).
Intestinal Juice
About 1–2 liters of intestinal juice are secreted daily, mainly in response to acidic or hypertonic chyme. The juice is slightly alkaline, isotonic with blood plasma, and consists largely of water and mucus.
Digestive Processes in the Small Intestine
Chyme Entry Regulation: Chyme enters the duodenum slowly to prevent osmotic water loss and is mixed with bile and pancreatic juice. The enterogastric reflex and enterogastrones regulate this process.
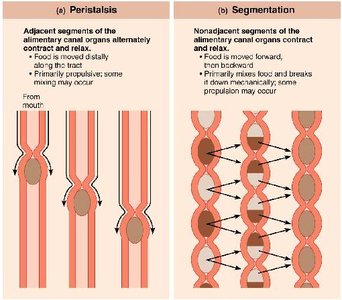
Motility: After a meal, segmentation mixes and moves chyme; between meals, peristalsis (migrating motor complex) propels remnants toward the large intestine.
Control of Small Intestinal Motility
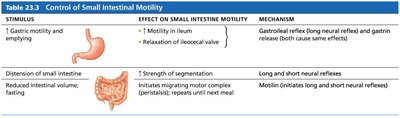
Stimulus | Effect on Small Intestine Motility | Mechanism |
|---|---|---|
Gastric motility and emptying | ↑ Motility in ileum, relaxation of ileocecal valve | Gastroileal reflex (neural), gastrin release |
Distension of small intestine | ↑ Strength of segmentation | Long and short neural reflexes |
Reduced intestinal volume, fasting | Initiates migrating motor complex (peristalsis) | Motilin (hormonal) |
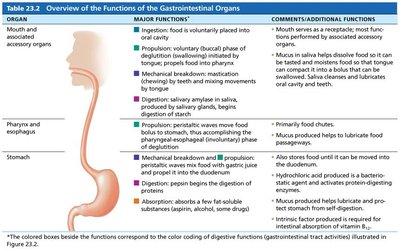
Overview of Gastrointestinal Organ Functions
Organ | Major Functions | Comments/Additional Functions |
|---|---|---|
Mouth and associated accessory organs | Ingestion, propulsion, mechanical breakdown, digestion | Mucus lubricates food; salivary amylase begins starch digestion |
Stomach | Mechanical breakdown, propulsion, digestion, absorption | Hydrochloric acid and pepsin begin protein digestion |
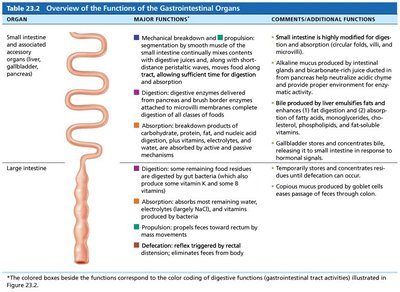
Organ | Major Functions | Comments/Additional Functions |
|---|---|---|
Small intestine | Mechanical breakdown, propulsion, digestion, absorption | Highly modified for absorption; brush border enzymes complete digestion |
Large intestine | Digestion (bacterial), absorption, propulsion, defecation | Absorbs water, electrolytes, vitamins; forms and stores feces |
The Large Intestine
Gross Anatomy of the Large Intestine
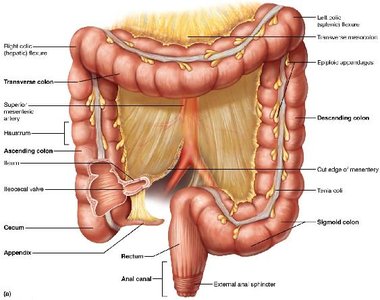
The large intestine absorbs water and electrolytes, forms feces, and eliminates waste. It has unique features such as teniae coli (three bands of longitudinal muscle), haustra (pouch-like sacs), and epiploic appendages (fat-filled pouches).
Cecum: First part, receives chyme from ileum.
Appendix: Contains lymphoid tissue, acts as a bacterial storehouse.
Colon: Ascending, transverse, descending, and sigmoid regions.
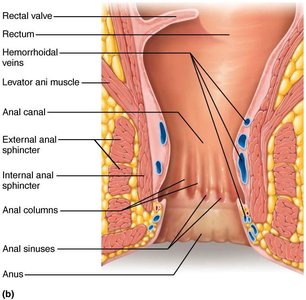
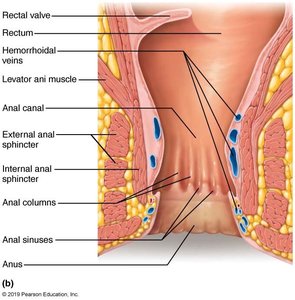
Rectum: Contains rectal valves to separate feces from gas.
Anal canal: Opens to the exterior, contains internal (smooth muscle) and external (skeletal muscle) sphincters.
Relationship to the Peritoneum
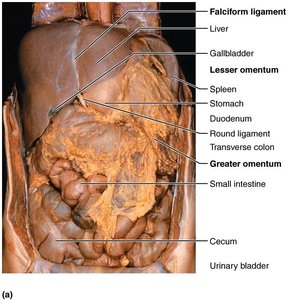
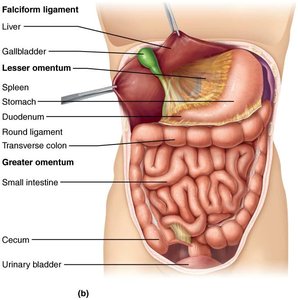
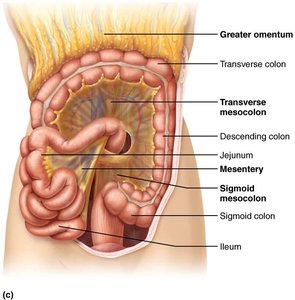
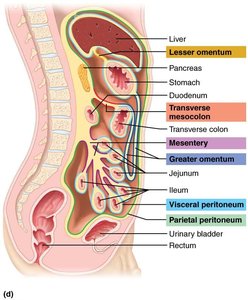
The cecum, appendix, and rectum are retroperitoneal, while the transverse and sigmoid colon are intraperitoneal and anchored by mesocolons.
Microscopic Anatomy of the Large Intestine
Thicker mucosa with simple columnar epithelium (except in the anal canal, which is stratified squamous for abrasion resistance).
No circular folds, villi, or digestive secretions; abundant deep crypts with many goblet cells.
Anal columns and anal recesses aid in emptying and mucus secretion.
Pectinate line divides regions of visceral (insensitive) and somatic (sensitive) innervation.
Bacterial Flora
Over 1000 species of bacteria ferment indigestible carbohydrates, synthesize B vitamins and vitamin K, and help suppress pathogenic bacteria.
Gut bacteria influence body weight, disease susceptibility, and even mood.
Digestive Processes in the Large Intestine
Residue remains for 12–24 hours; vitamins, water, and electrolytes are reclaimed.
Haustral contractions and mass movements (gastrocolic reflex) propel feces toward the rectum.
Defecation is initiated by rectal distension, involving both involuntary (internal sphincter) and voluntary (external sphincter) control.
Clinical Considerations
Appendicitis: Inflammation of the appendix, often requiring surgical removal.
Antibiotic-associated diarrhea: Overgrowth of Clostridium difficile can cause severe colitis.
Diverticulosis/Diverticulitis: Outpouchings of the colon wall, which can become inflamed or rupture.
Irritable Bowel Syndrome (IBS): Functional disorder with abdominal pain, bloating, and altered bowel habits.
Diarrhea and Constipation: Result from altered water absorption in the colon.
Summary Table: Control of Small Intestinal Motility
Stimulus | Effect | Mechanism |
|---|---|---|
Gastric motility/emptying | ↑ Motility in ileum, relaxes ileocecal valve | Gastroileal reflex, gastrin |
Distension of small intestine | ↑ Segmentation strength | Neural reflexes |
Fasting | Initiates migrating motor complex | Motilin |
Additional info: The small and large intestines are essential for digestion, absorption, and waste elimination. Their structure and function are closely integrated with accessory organs and regulated by neural and hormonal mechanisms. Disruptions in these processes can lead to significant clinical conditions.
