 Indietro
Bone Development, Growth, Remodeling, and Disorders: Study Notes for Anatomy & Physiology
Guida di studio - Note intelligenti
 Appunti personalizzati basati sui tuoi materiali, ampliati con definizioni chiave, esempi e contesto.
Bones and Skeletal Tissues
Bone Development (Ossification)
Bone development, also known as ossification or osteogenesis, is the process by which bone tissue forms. This process begins in the second month of embryonic development and continues throughout life as bones grow, remodel, and repair.
Formation of the bony skeleton: Up to week 8, the fetal skeleton consists of fibrous membranes and hyaline cartilage, which are gradually replaced by bone tissue.
Endochondral ossification: Bone forms by replacing hyaline cartilage. Most bones below the skull (except clavicles) are formed this way.
Intramembranous ossification: Bone develops directly from fibrous membranes, forming the flat bones of the skull and clavicle.
Endochondral Ossification
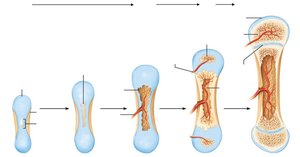
Endochondral ossification is the process by which most bones are formed, especially those inferior to the base of the skull. It involves several steps:
Bone collar forms around the diaphysis of the cartilage model.
Central cartilage in diaphysis calcifies and develops cavities.
Periosteal bud invades cavities, forming spongy bone.
Diaphysis elongates, medullary cavity forms, and secondary ossification centers appear in epiphyses.
Epiphyses ossify; hyaline cartilage remains only in epiphyseal plates and articular cartilages.
Intramembranous Ossification
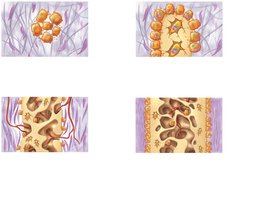
Intramembranous ossification forms flat bones such as the frontal, parietal, occipital, temporal, and clavicle bones. The process involves:
Ossification centers form when mesenchymal cells cluster and become osteoblasts.
Osteoid is secreted and calcified.
Woven bone forms around blood vessels, resulting in trabeculae.
Outer layer of woven bone forms periosteum; lamellar bone replaces woven bone, and red marrow appears.
Postnatal Bone Growth
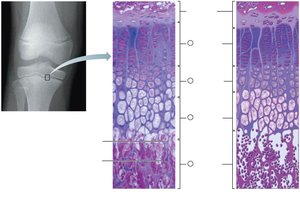
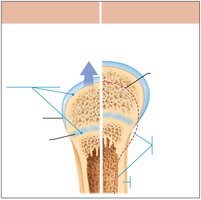
After birth, bones continue to grow in length and width. Long bones grow lengthwise by interstitial growth at the epiphyseal plate, while appositional growth increases bone thickness.
Epiphyseal plate: Responsible for longitudinal growth; consists of several zones (resting, proliferation, hypertrophic, calcification, ossification).
Bones stop growing during adolescence, with epiphyseal plate closure occurring around age 18 in females and 21 in males.
Appositional growth allows bones to thicken throughout life, responding to stress and weight.
Hormonal Regulation of Bone Growth
Bone growth is regulated by several hormones:
Growth hormone: Stimulates epiphyseal plate activity in childhood.
Thyroid hormone: Modulates growth hormone activity for proper proportions.
Sex hormones (testosterone and estrogens): Promote adolescent growth spurts and induce epiphyseal plate closure.
Imbalances in these hormones can cause abnormal skeletal growth.
Bone Remodeling
Bone Remodeling Process
Bone remodeling is a lifelong process involving bone deposit and resorption, coordinated by osteoblasts and osteoclasts. About 5–7% of bone mass is recycled weekly.
Bone deposit: Osteoblasts deposit new bone matrix (osteoid seam), which is then mineralized.
Bone resorption: Osteoclasts break down bone matrix, releasing calcium and other minerals into the blood.
Remodeling occurs at both periosteum and endosteum surfaces.
Control of Remodeling
Bone remodeling is regulated by hormonal and mechanical factors:
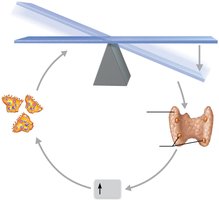
Parathyroid hormone (PTH): Released in response to low blood calcium levels, stimulates osteoclasts to resorb bone and release calcium.
Calcitonin: Released by the thyroid gland, inhibits bone resorption and lowers blood calcium levels.
Mechanical stress and gravity also influence bone remodeling.
Bone Repair
Fracture Classification
Fractures are classified based on the position of bone ends, completeness of the break, and whether the skin is penetrated. Common types include:
Nondisplaced vs. displaced: Bone ends retain or lose normal position.
Complete vs. incomplete: Bone is broken all the way through or not.
Open (compound) vs. closed (simple): Skin is penetrated or not.
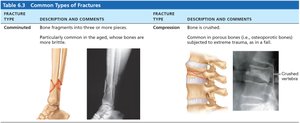
Common Types of Fractures
Fracture Type | Description and Comments |
|---|---|
Comminuted | Bone fragments into three or more pieces; common in aged bones. |
Compression | Bone is crushed; common in porous bones subjected to extreme trauma. |
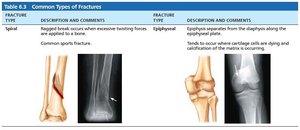
Fracture Type | Description and Comments |
|---|---|
Spiral | Ragged break due to excessive twisting forces; common sports fracture. |
Epiphyseal | Epiphysis separates from diaphysis along epiphyseal plate; occurs where cartilage cells are dying. |
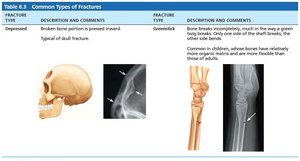
Fracture Type | Description and Comments |
|---|---|
Depressed | Broken bone portion is pressed inward; typical of skull fracture. |
Greenstick | Bone breaks incompletely; common in children. |
Fracture Treatment and Repair
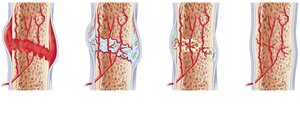
Fracture repair involves four major stages:
Hematoma formation: Blood vessels break, forming a hematoma.
Fibrocartilaginous callus formation: Soft callus forms as new blood vessels and cells invade.
Bony callus formation: Spongy bone replaces the soft callus.
Bone remodeling: Bone is remodeled to restore its original shape and structure.
Bone Disorders
Osteomalacia and Rickets
Osteomalacia refers to poorly mineralized bones in adults, resulting in soft, weak bones and pain. Rickets is the childhood form, causing bowed legs and bone deformities due to vitamin D deficiency or insufficient calcium.
Osteoporosis
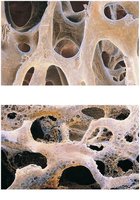
Osteoporosis is a group of diseases where bone resorption exceeds deposit, leading to decreased bone mass and increased fracture risk, especially in the spine and femur.
Risk factors: Age, postmenopausal women, low estrogen, insufficient exercise, poor diet, smoking, genetics, hormone-related conditions, alcohol, and certain medications.
Treatment: Calcium, vitamin D, weight-bearing exercise, hormone replacement therapy (controversial).
Paget’s Disease
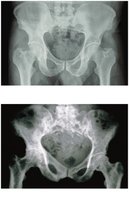
Paget’s disease involves excessive and disorganized bone remodeling, resulting in weak, deformed bones with a high ratio of spongy to compact bone. It usually affects the spine, pelvis, femur, and skull, and is treated with calcitonin and bisphosphonates.
Summary Table: Bone Disorders
Disorder | Key Features | Causes | Treatment |
|---|---|---|---|
Osteomalacia/Rickets | Soft, weak bones; deformities | Vitamin D deficiency, low calcium | Vitamin D, calcium supplements |
Osteoporosis | Low bone mass, fractures | Age, hormonal changes, lifestyle | Calcium, vitamin D, exercise, hormone therapy |
Paget’s Disease | Disorganized bone, deformities | Unknown, possibly viral | Calcitonin, bisphosphonates |
