 Indietro
Diabetes Mellitus: Anatomy, Physiology, and Pathophysiology of the Pancreas
Guida di studio - Note intelligenti
 Appunti personalizzati basati sui tuoi materiali, ampliati con definizioni chiave, esempi e contesto.
The Pancreas: Anatomy and Physiology
Location and Structure
The pancreas is a long, flat organ situated within the abdomen, posterior to the stomach. It measures approximately 12–20 cm in length and possesses both endocrine and exocrine functions.
Exocrine function: Secretes digestive enzymes into the duodenum, aiding in the breakdown of carbohydrates, lipids, and proteins.
Endocrine function: Produces hormones, primarily insulin and glucagon, which regulate blood glucose levels.
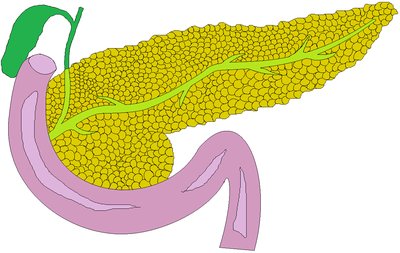
Islets of Langerhans: Cell Types and Hormones
The endocrine portion of the pancreas consists of clusters of cells called the islets of Langerhans, which contain five key cell types:
Alpha cells: Produce glucagon, a peptide hormone that raises blood glucose by triggering glycogen breakdown in the liver.
Beta cells: Produce insulin, a peptide hormone that lowers blood glucose by promoting glycogen formation and glucose uptake by muscle and fat cells.
Delta cells: Produce somatostatin, which inhibits insulin and glucagon secretion, regulating the system.
Gamma (PP) cells: Produce pancreatic polypeptide, which regulates pancreatic function and reduces appetite.
Epsilon cells: Produce ghrelin, which induces hunger and inhibits insulin secretion, allowing blood sugar to rise after a meal.
Blood Glucose Regulation
Hormonal Control and Homeostasis
nsulin: activates transportation of glucose from blood into the
liver, fat and muscle cells (lowering blood glucose)
• Glucagon: activates breakdown of glycogen (mainly in liver) to
release glucose into the circulation (raising blood glucose)
• The antagonistic hormone pair in insulin and glucagon therefore
allows for blood glucose homeostasis
• Homeostatic regulation maintains blood glucose levels within a
normal, adult fasting range of 3.5–5.5 mmol/L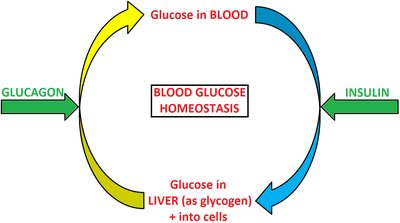
Mechanism of Insulin Action
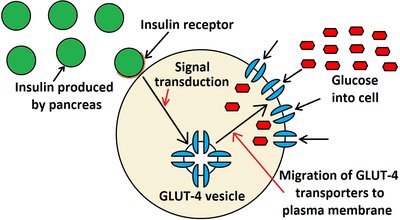
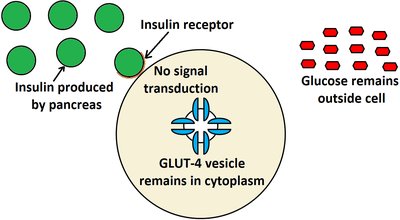
Insulin binds to receptors on cell surfaces, causing glucose transporter proteins (GLUT-4) to relocate to the plasma membrane, allowing glucose to enter cells via facilitated diffusion.
Facilitated diffusion: Movement of glucose into cells is enabled by transporter proteins, not by simple diffusion.
Diabetes Mellitus: Types and Pathophysiology
Type I Diabetes Mellitus
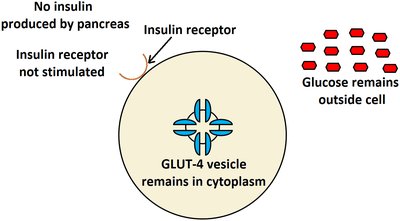
Type I diabetes is an autoimmune disease characterized by destruction of beta cells, resulting in little or no insulin production. It is referred to as insulin-dependent diabetes.
Pathophysiology: Immune system (B and T lymphocytes, macrophages) attacks beta cells; triggers are genetic and environmental.
Symptoms: Sudden onset, severe hyperglycaemia, increased fat breakdown, ketoacidosis.
Ketoacidosis: High levels of ketones due to fat metabolism; can lead to coma and death if untreated.
Rare causes: Pancreatitis or idiopathic (unknown cause).
Type II Diabetes Mellitus
Type II diabetes is characterized by insulin resistance, where cells become less responsive to insulin. It is referred to as non-insulin dependent or insulin resistant diabetes.
Pathophysiology: Insulin is produced, but cells are resistant; beta cell function may decline over time.
Triggers: Environmental factors (obesity, inactivity), genetic predisposition, increasing age, hypertension, ethnicity.
Progression: Gradual development; increased insulin production leads to beta cell exhaustion and death.
Reversibility: Type II can be reversed by addressing causes (weight loss, increased activity); Type I cannot.
Metabolic syndrome: Pre-diabetic state with increased risk for diabetes, heart disease, and stroke.
Metabolic Syndrome and Obesity
Metabolic syndrome is diagnosed if three or more specific traits are present, including increased waist circumference, elevated plasma triglycerides, reduced HDL:cholesterol ratio, elevated blood pressure, and elevated fasting plasma glucose.
Obesity: Contributes to type II diabetes via adipokines (inflammatory hormones), elevated blood fats, increased inflammatory cytokines, and prolonged hyperinsulinemia.
Trait | Measurement |
|---|---|
Increased waist circumference | male > 40 inches, female > 35 inches |
Increased plasma triglycerides | ≥ 1.71 mmol/L |
Reduced plasma HDL:cholesterol ratio | male < 1.04 mmol/L, female < 1.3 mmol/L |
Elevated blood pressure | ≥ 130/85 mmHg |
Elevated fasting plasma glucose | 5.6–6.9 mmol/L |
Symptoms and Diagnosis of Diabetes Mellitus
Key Symptoms
Both types of diabetes share several key symptoms, though their onset and severity may differ.
Polyuria: Excessive urine production due to glucose acting as a diuretic.
Polydipsia: Excessive thirst caused by dehydration.
Polyphagia: Excessive hunger due to reduced glucose metabolism.
Weight loss: Fat stores metabolized when glucose is unavailable.
Fatigue: Low energy from inability to metabolize glucose.
Visual disturbance: Fluctuating osmotic pressure and retinal damage.
Paraesthesia: Nerve dysfunction from hyperglycaemia.
Pruritus: Itchy skin (type II).
Recurrent infections: Poor wound healing (type II).
Nocturia: Night-time urination (type II).
Diagnostic Tests
Diagnosis of diabetes mellitus is based on several laboratory tests:
Test | Normal | Diabetes Mellitus |
|---|---|---|
Glycosylated haemoglobin (HbA1c) | 18–46 mmol/mol | > 48 mmol/mol |
Fasting Plasma Glucose (FPG) | < 7.8 mmol/L | ≥ 7.8 mmol/L |
Oral Glucose Tolerance Test (OGTT) | < 7.8 mmol/L | ≥ 11.1 mmol/L |
Random Plasma Glucose | 4.2–6.4 mmol/L | ≥ 11.1 mmol/L |
Complications of Diabetes Mellitus
Acute Complications
Diabetic ketoacidosis: Most common in type I; results from insulin deficiency, leading to fat metabolism and acidic ketone production. Blood pH drops below 7.3.
Severe hypoglycaemia (insulin shock): Plasma glucose < 3.33 mmol/L due to excess insulin or medication; symptoms include pallor, tremor, anxiety, seizures, coma.
Chronic Complications
Cardiovascular: Atherosclerosis, hypertension, hypercoagulability, heart failure, poor wound healing.
Neuropathy: Peripheral nerve dysfunction and degeneration.
Nephropathy: Glomerular damage, renal failure; diabetes is the most common reason for dialysis.
Retinopathy: Cataracts, macular degeneration.
Infections: Impaired immunity due to abnormal blood sugar and fat levels.
Additional info: The notes expand on the original content by providing definitions, mechanisms, and clinical context for each topic, ensuring completeness and academic quality for exam preparation.
