 Indietro
Muscles and Muscle Tissue: Structure, Function, and Physiology
Guida di studio - Note intelligenti
 Appunti personalizzati basati sui tuoi materiali, ampliati con definizioni chiave, esempi e contesto.
Muscle Tissue Overview
Introduction to Muscle Tissue
Muscle tissue is essential for movement, posture, and various bodily functions. It transforms chemical energy (ATP) into mechanical energy, enabling force generation and movement. Nearly half of the body's mass is muscle tissue.
Key prefixes: myo-, mys-, and sarco- refer to muscle (e.g., sarcoplasm is muscle cell cytoplasm).
Three types of muscle tissue: Skeletal, Cardiac, and Smooth.
Only skeletal and smooth muscle cells are elongated and called muscle fibers.
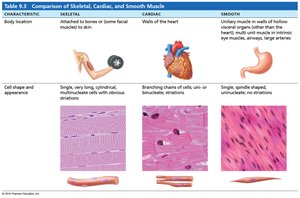
Types of Muscle Tissue
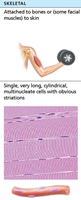
Skeletal Muscle: Attached to bones or skin, voluntary, striated, contracts rapidly, tires easily, and is powerful.
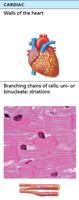
Cardiac Muscle: Found only in the heart, involuntary, striated, contracts at a steady rate due to the heart's pacemaker.
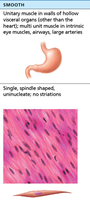
Smooth Muscle: Found in walls of hollow organs (e.g., stomach, bladder), involuntary, non-striated, contracts slowly.
Characteristics of Muscle Tissue
Excitability (Responsiveness): Ability to receive and respond to stimuli.
Contractility: Ability to shorten forcibly when stimulated.
Extensibility: Ability to be stretched.
Elasticity: Ability to recoil to resting length.
Functions of Muscle Tissue
Produce movement (locomotion, manipulation, pumping blood, digestion).
Maintain posture and body position.
Stabilize joints.
Generate heat as they contract.
Skeletal Muscle Anatomy
Structure and Organization
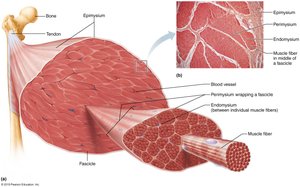
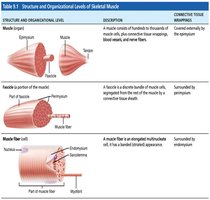
Skeletal muscle is an organ composed of muscle fibers, connective tissue, blood vessels, and nerves. It has three main features: nerve and blood supply, connective tissue sheaths, and attachments.
Nerve and Blood Supply: Each muscle receives a nerve, artery, and veins. Nerves control muscle activity, and blood vessels supply nutrients and remove wastes.
Connective Tissue Sheaths:
Epimysium: Surrounds the entire muscle.
Perimysium: Surrounds fascicles (groups of muscle fibers).
Endomysium: Surrounds each individual muscle fiber.
Muscle Attachments
Origin: Attachment to immovable or less movable bone.
Insertion: Attachment to movable bone.
Direct Attachment: Epimysium fused to periosteum of bone.
Indirect Attachment: Connective tissue extends as a tendon or aponeurosis.
Muscle Fiber Microanatomy and the Sliding Filament Model
Muscle Fiber Structure
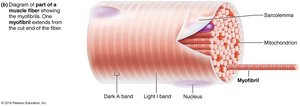
Skeletal muscle fibers are long, cylindrical, multinucleated cells. The sarcolemma is the plasma membrane, and the sarcoplasm is the cytoplasm, containing glycosomes (glycogen storage) and myoglobin (O2 storage).
Myofibrils: Densely packed, rodlike elements that make up 80% of cell volume.
Myofibril Features
Striations: Alternating dark (A bands) and light (I bands) regions.
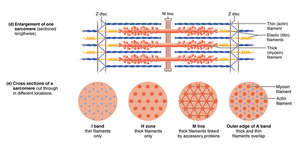
Sarcomeres: Smallest contractile units, aligned end to end along myofibril.
Myofilaments: Actin (thin) and myosin (thick) filaments arranged in a hexagonal pattern.

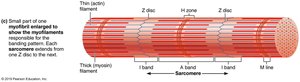
Molecular Composition of Myofilaments
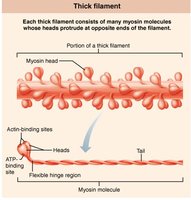
Thick Filaments: Composed of myosin molecules with heads that form cross bridges during contraction.
Thin Filaments: Composed of actin, tropomyosin, and troponin. Actin subunits have binding sites for myosin heads.
Elastic Filament: Composed of titin, helps maintain sarcomere structure.
Dystrophin: Links thin filaments to sarcolemma proteins.

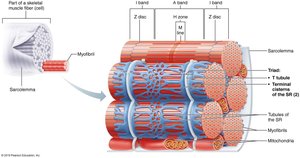
Sarcoplasmic Reticulum and T Tubules
Sarcoplasmic Reticulum (SR): Stores and releases Ca2+ for muscle contraction.
T Tubules: Invaginations of the sarcolemma that transmit action potentials deep into the muscle fiber.
Triad: Consists of a T tubule and two terminal cisterns of the SR.
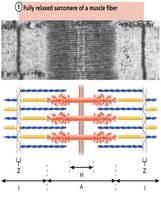
Sliding Filament Model of Contraction
Mechanism of Contraction
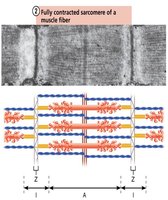
Muscle contraction occurs when myosin heads bind to actin, forming cross bridges and pulling thin filaments toward the center of the sarcomere. This process shortens the muscle fiber without changing the length of the filaments themselves.
During contraction, Z discs are pulled toward the M line, I bands shorten, H zones disappear, and A bands move closer together.
Muscle Fiber Contraction: The Neuromuscular Junction and Action Potential
Neuromuscular Junction (NMJ)
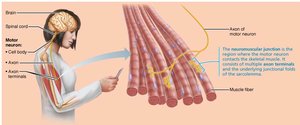
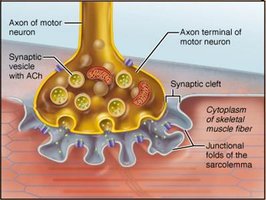
The NMJ is the site where a motor neuron communicates with a muscle fiber. The axon terminal releases acetylcholine (ACh), which binds to receptors on the sarcolemma, initiating an action potential in the muscle fiber.
Synaptic cleft: Space between axon terminal and muscle fiber.
Junctional folds: Increase surface area for ACh receptors.
Generation of an Action Potential
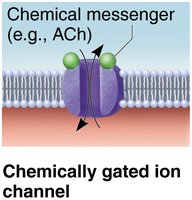
End Plate Potential: ACh binding opens chemically gated ion channels, allowing Na+ influx and local depolarization.
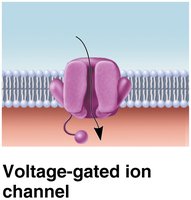
Depolarization: If threshold is reached, voltage-gated Na+ channels open, generating an action potential that spreads across the sarcolemma.
Repolarization: Na+ channels close, K+ channels open, restoring resting membrane potential.
Excitation-Contraction (E-C) Coupling and Cross Bridge Cycling
Excitation-Contraction Coupling
E-C coupling links the action potential in the sarcolemma to the sliding of myofilaments. The action potential travels down T tubules, triggering Ca2+ release from the SR, which initiates contraction.
Cross Bridge Cycle
Cross Bridge Formation: Myosin head attaches to actin.
Power Stroke: Myosin head pivots, pulling actin filament toward M line.
Cross Bridge Detachment: ATP binds to myosin, causing detachment from actin.
Cocking of Myosin Head: ATP hydrolysis re-energizes the myosin head.
Whole Muscle Contraction
Motor Units and Muscle Twitch
Motor Unit: A motor neuron and all the muscle fibers it innervates.
Muscle Twitch: Response of a muscle to a single stimulus, consisting of latent, contraction, and relaxation phases.
Graded Muscle Responses
Muscle contractions are graded by changing the frequency and strength of stimulation.
Wave summation: Increased frequency leads to greater force.
Recruitment: Increased stimulus strength activates more motor units.
Isotonic and Isometric Contractions
Isotonic: Muscle changes length (concentric or eccentric).
Isometric: Muscle tension increases, but length does not change.
Energy for Contraction
ATP and Muscle Metabolism
ATP is the direct source of energy for muscle contraction. It is regenerated by:
Direct phosphorylation: Creatine phosphate donates a phosphate to ADP to form ATP.
Anaerobic pathway: Glycolysis and lactic acid formation (no oxygen required).
Aerobic respiration: Uses oxygen to produce ATP from glucose, fatty acids, and other fuels.
Muscle Fatigue and Recovery
Muscle Fatigue: Inability to contract despite stimulation, caused by ionic imbalances, decreased ATP, or other metabolic factors.
Excess Postexercise Oxygen Consumption (EPOC): Oxygen required to restore muscle to pre-exercise state.
Clinical Connections
Duchenne Muscular Dystrophy (DMD): Genetic disorder causing muscle degeneration due to defective dystrophin.
Myasthenia Gravis: Autoimmune disease reducing ACh receptors, leading to muscle weakness.
Rigor Mortis: Postmortem muscle stiffening due to lack of ATP for cross bridge detachment.
Muscle Type | Location | Cell Shape & Appearance | Control | Striations |
|---|---|---|---|---|
Skeletal | Attached to bones/skin | Long, cylindrical, multinucleate | Voluntary | Yes |
Cardiac | Heart walls | Branching, uni- or binucleate | Involuntary | Yes |
Smooth | Walls of hollow organs | Spindle-shaped, uninucleate | Involuntary | No |
