 뒤로
Bone Development, Growth, Remodeling, and Disorders: Study Notes for Anatomy & Physiology
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
Bones and Skeletal Tissues
Bone Development (Ossification)
Ossification, also known as osteogenesis, is the process by which bone tissue forms. This process begins in the second month of embryonic development and continues throughout life, with bone remodeling and repair persisting into adulthood.
Ossification: Formation of bone tissue from precursor structures.
Formation of Bony Skeleton: Up to week 8, the fetal skeleton consists of fibrous membranes and hyaline cartilage, which are gradually replaced by bone.
Types of Ossification:
Endochondral Ossification: Bone forms by replacing hyaline cartilage. Most bones below the skull (except clavicles) are formed this way.
Intramembranous Ossification: Bone develops directly from fibrous membranes, forming flat bones such as the skull and clavicle.
Endochondral Ossification
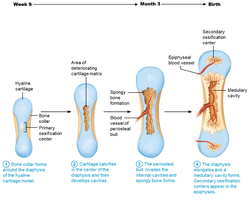
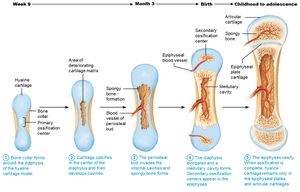
Endochondral ossification is the process by which most bones are formed, especially those inferior to the base of the skull. It begins late in the second month of development and uses hyaline cartilage models as templates.
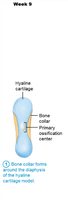
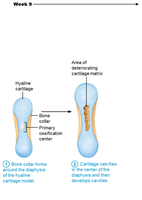
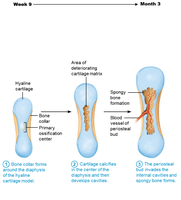
Bone collar forms around the diaphysis of the cartilage model.
Central cartilage in diaphysis calcifies and develops cavities.
Periosteal bud invades cavities, forming spongy bone.
Diaphysis elongates, medullary cavity forms, and secondary ossification centers appear in epiphyses.
Epiphyses ossify; hyaline cartilage remains only in epiphyseal plates and articular cartilages.
Intramembranous Ossification
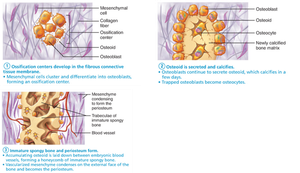
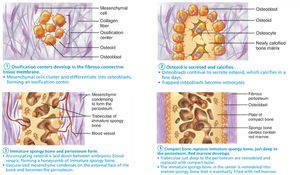
Intramembranous ossification forms flat bones such as the frontal, parietal, occipital, temporal, and clavicle bones. It begins within fibrous connective tissue membranes formed by mesenchymal cells.
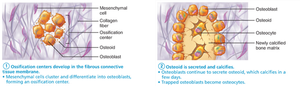
Ossification centers form when mesenchymal cells cluster and become osteoblasts.
Osteoid is secreted and then calcified.
Woven bone forms as osteoid is laid down around blood vessels, resulting in trabeculae.
Outer layer of woven bone forms periosteum; lamellar bone replaces woven bone, and red marrow appears.
Postnatal Bone Growth
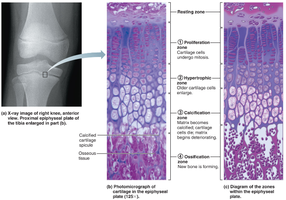
After birth, bones grow in length and width. Long bones grow lengthwise by interstitial growth of the epiphyseal plate, while appositional growth increases bone thickness.
Interstitial Growth: Requires epiphyseal cartilage; plate maintains constant thickness as cartilage growth and bone replacement are balanced.
Zones of Epiphyseal Plate:
Resting (quiescent) zone
Proliferation (growth) zone
Hypertrophic zone
Calcification zone
Ossification (osteogenic) zone
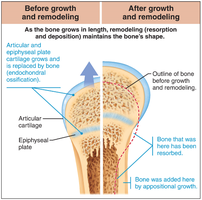
Growth in Width (Appositional Growth): Osteoblasts beneath periosteum secrete bone matrix; osteoclasts remove bone on endosteal surface. Bones thicken in response to stress.
Hormonal Regulation: Growth hormone stimulates epiphyseal plate activity; thyroid hormone modulates growth hormone; sex hormones induce growth spurts and epiphyseal plate closure.
Bone Remodeling
Bone remodeling is a lifelong process involving bone deposit and resorption. About 5–10% of bone mass is recycled each year. Osteoblasts and osteoclasts respond to hormonal signals and mechanical stress.
Bone Resorption: Osteoclasts break down bone matrix, releasing minerals into the blood.
Bone Deposit: Osteoblasts deposit new bone matrix; calcification occurs as calcium and phosphate ions form hydroxyapatite crystals.
Control of Remodeling
Hormonal Controls:
Parathyroid hormone (PTH) increases blood calcium by stimulating osteoclasts.
Calcitonin lowers blood calcium at high doses.
Mechanical Stress: Bones remodel in response to mechanical forces (Wolf’s law).
Bone Repair
Fractures are breaks in bone, classified by position, completeness, and whether skin is penetrated. Repair involves four stages:
Hematoma formation
Fibrocartilaginous callus formation
Bony callus formation
Bone remodeling
Bone Disorders
Imbalances between bone deposit and resorption cause bone diseases:
Osteomalacia and Rickets: Caused by vitamin D deficiency or insufficient calcium; bones are soft and weak.
Osteoporosis: Bone resorption exceeds deposit; bone mass declines, increasing fracture risk.
Paget’s Disease: Excessive, disorganized bone remodeling; high ratio of spongy to compact bone.
Summary Table: Common Types of Fractures
Type | Description |
|---|---|
Nondisplaced | Ends retain normal position |
Displaced | Ends are out of normal alignment |
Complete | Broken all the way through |
Incomplete | Not broken all the way through |
Open (compound) | Skin is penetrated |
Closed (simple) | Skin is not penetrated |
Additional info: See textbook for specific fracture types (e.g., comminuted, spiral, etc.) |
Key Equations
Calcium homeostasis is regulated by hormones:
Bone mass changes:
Example: Osteoporosis occurs when bone resorption exceeds bone deposit, leading to decreased bone mass and increased fracture risk.
Additional info: Bone remodeling is influenced by both hormonal and mechanical factors, ensuring bones adapt to physiological needs and environmental stresses.
