뒤로
Bones and Skeletal Tissues: Structure, Function, Development, and Disorders
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
Bones and Skeletal Tissues
Skeletal Cartilages
The human skeleton initially consists of cartilage, which is gradually replaced by bone except in areas requiring flexibility. Skeletal cartilage is made of highly resilient, molded tissue that consists primarily of water and contains no blood vessels or nerves. The perichondrium is a dense connective tissue layer surrounding cartilage, providing resistance to outward expansion and containing blood vessels for nutrient delivery. Cartilage is composed of chondrocytes, cells encased in lacunae within a jelly-like extracellular matrix.
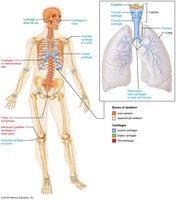
Types of Cartilage
Hyaline cartilage: Provides support, flexibility, and resilience; most abundant; contains only collagen fibers. Found in articular (joints), costal (ribs), respiratory (larynx), and nasal cartilage.
Elastic cartilage: Similar to hyaline but contains elastic fibers. Found in external ear and epiglottis.
Fibrocartilage: Contains thick collagen fibers for great tensile strength. Found in menisci of knee and vertebral discs.
Growth of Cartilage
Appositional growth: Cartilage-forming cells in perichondrium secrete matrix on the surface of existing cartilage.
Interstitial growth: Chondrocytes within lacunae divide and secrete new matrix, expanding cartilage from within.
Calcification: Occurs during normal bone growth in youth and old age; hardened cartilage is not bone.
Functions of Bones
Bones perform seven essential functions:
Support: Framework for the body and soft organs.
Protection: Shields brain, spinal cord, and vital organs.
Movement: Acts as levers for muscle action.
Mineral and growth factor storage: Reservoir for calcium, phosphorus, and growth factors.
Blood cell formation: Hematopoiesis occurs in red marrow cavities.
Triglyceride storage: Fat stored in bone cavities for energy.
Hormone production: Osteocalcin regulates insulin secretion, glucose levels, and metabolism.
Classification of Bones
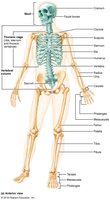
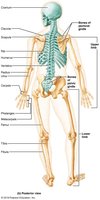
The human skeleton has 206 named bones, divided into two groups:
Axial skeleton: Long axis of body; includes skull, vertebral column, and rib cage.
Appendicular skeleton: Bones of limbs and girdles attaching limbs to axial skeleton.
Bone Shapes
Long bones: Longer than wide; limb bones.
Short bones: Cube-shaped; wrist and ankle bones; sesamoid bones form within tendons (e.g., patella).
Flat bones: Thin, flat, slightly curved; sternum, scapulae, ribs, skull bones.
Irregular bones: Complicated shapes; vertebrae and hip bones.
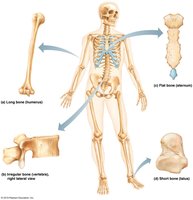
Bone Structure
Bones are organs containing various tissues: bone (osseous), nervous, cartilage, fibrous connective, muscle, and epithelial cells in blood vessels. Structure is studied at three levels: gross, microscopic, and chemical.
Gross Anatomy
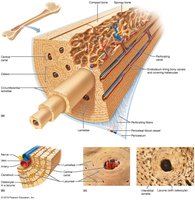
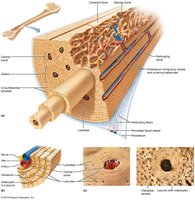
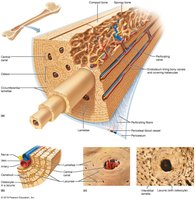
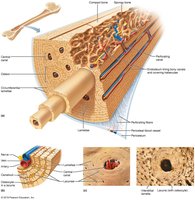
Compact bone: Dense outer layer, smooth and solid.
Spongy bone: Honeycomb of trabeculae; spaces filled with red or yellow marrow.
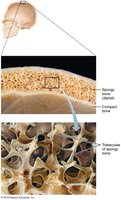
Structure of Long Bones
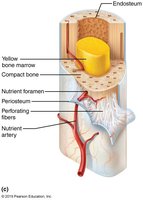
Diaphysis: Tubular shaft; compact bone surrounds medullary cavity (yellow marrow in adults).
Epiphyses: Ends of long bones; compact bone externally, spongy bone internally; articular cartilage covers joint surfaces.
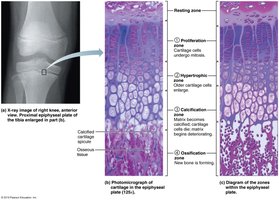
Epiphyseal line: Remnant of childhood epiphyseal plate where bone growth occurs.
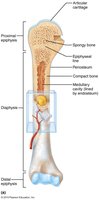
Bone Membranes
Periosteum: Double-layered membrane covering external surfaces except joints; fibrous layer (dense irregular connective tissue), osteogenic layer (stem cells).
Endosteum: Delicate membrane covering internal bone surfaces; contains osteogenic cells.
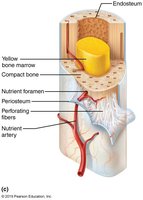
Hematopoietic Tissue in Bones
Red marrow: Found in trabecular cavities of spongy bone and diploë of flat bones; active in hematopoiesis.
Yellow marrow: Can convert to red marrow if needed (e.g., anemia).
Bone Markings
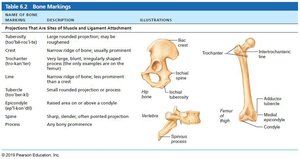
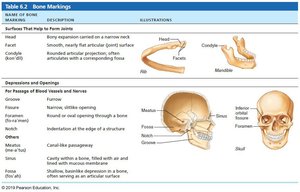
Bone markings are sites for muscle, ligament, and tendon attachment, joint formation, or passageways for blood vessels and nerves. They are classified as projections, depressions, or openings.
Name of Bone Marking | Description | Illustration |
|---|---|---|
Crest | Narrow ridge of bone; usually prominent | Hip bone |
Tubercle | Small rounded projection or process | Femur |
Spine | Sharp, slender, often pointed projection | Vertebra |
Head | Bony expansion carried on a narrow neck | Femur |
Foramen | Round or oval opening through a bone | Skull |
Fossa | Shallow depression | Skull |
Microscopic Anatomy of Bone
Bone Cells
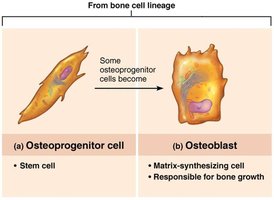
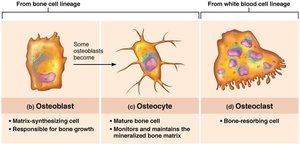
Osteogenic cells: Stem cells in periosteum and endosteum; differentiate into osteoblasts or bone-lining cells.
Osteoblasts: Bone-forming cells; secrete osteoid (collagen and calcium-binding proteins).
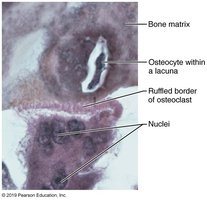
Osteocytes: Mature bone cells in lacunae; maintain matrix and act as stress sensors.
Bone-lining cells: Flat cells on bone surfaces; help maintain matrix.
Osteoclasts: Multinucleate cells; resorb bone matrix.
Compact Bone
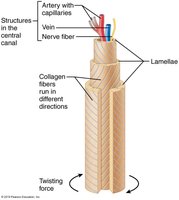
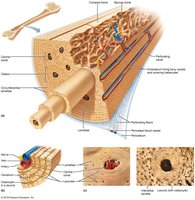
Osteon (Haversian system): Structural unit; elongated cylinder parallel to bone axis; consists of concentric lamellae.
Lamellae: Collagen fibers run in different directions in adjacent rings; withstand stress and resist twisting.
Canals and canaliculi: Central canal contains blood vessels and nerves; canaliculi connect lacunae and allow communication.
Interstitial and circumferential lamellae: Fill gaps between osteons and extend around diaphysis.
Spongy Bone
Trabeculae: Align along lines of stress; confer strength; contain lamellae and osteocytes interconnected by canaliculi.
Capillaries: Supply nutrients via endosteum.
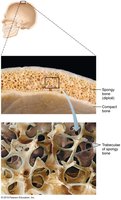
Chemical Composition of Bone
Organic components: Cells and osteoid (ground substance and collagen fibers); provide tensile strength and flexibility.
Inorganic components: Hydroxyapatites (mineral salts); 65% of bone mass; mainly calcium phosphate crystals; responsible for hardness and resistance to compression.
Bone Development (Ossification)
Ossification is the process of bone tissue formation. Formation of the bony skeleton begins in the second month of development. Two methods:
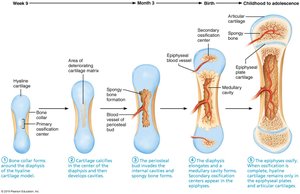
Endochondral ossification: Bone forms by replacing hyaline cartilage; forms most of the skeleton.
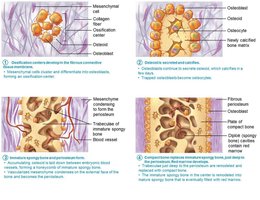
Intramembranous ossification: Bone develops from fibrous membrane; forms cranial bones and clavicles.
Postnatal Bone Growth
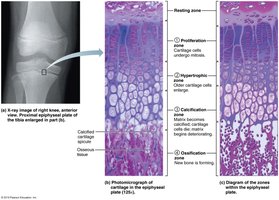
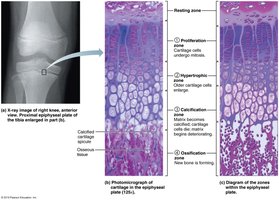
Longitudinal growth: Occurs at epiphyseal plate; five zones: resting, proliferation, hypertrophic, calcification, ossification.
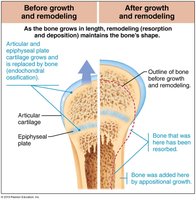
Appositional growth: Bones increase thickness throughout life.
Growth in Width
Bones widen as they lengthen through appositional growth; osteoblasts secrete matrix externally, osteoclasts remove bone internally.
Hormonal Regulation
Growth hormone: Stimulates epiphyseal plate activity.
Thyroid hormone: Modulates growth hormone activity.
Sex hormones: Promote growth spurts and induce epiphyseal plate closure.
Bone Remodeling
Bone mass is recycled weekly; spongy bone replaced every 3-4 years, compact bone every 10 years.
Remodeling consists of bone deposit (by osteoblasts) and bone resorption (by osteoclasts).
Hormonal Controls
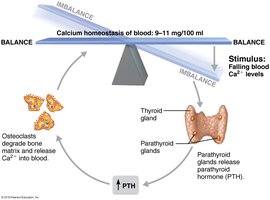
Parathyroid hormone (PTH): Stimulates osteoclasts to resorb bone when blood calcium is low.
Calcitonin: Lowers blood calcium levels temporarily.
Response to Mechanical Stress
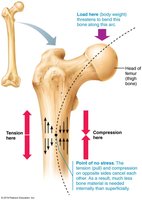
Bones remodel in response to mechanical demands (Wolf’s law).
Bending compresses one side and stretches the other; diaphysis is thickest where stresses are greatest.
Bone Repair
Fractures are classified by position, completeness, and skin penetration.
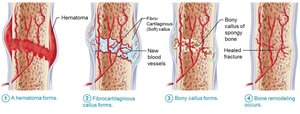
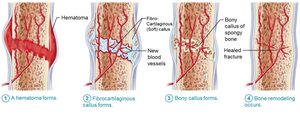
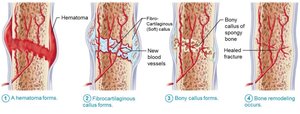
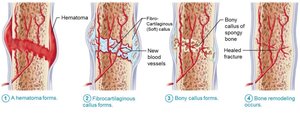
Repair involves four stages: hematoma formation, fibrocartilaginous callus formation, bony callus formation, bone remodeling.
Fracture Type | Description | Comments |
|---|---|---|
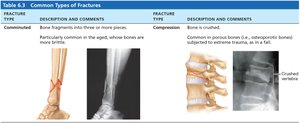
Comminuted | Bone fragments into three or more pieces | Common in aged |
Compression | Bone is crushed | Common in porous bones |
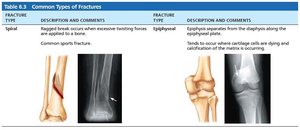
Spiral | Ragged break from twisting forces | Common sports fracture |
Epiphyseal | Epiphysis separates from diaphysis | Occurs where cartilage cells are dying |
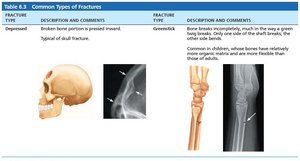
Depressed | Broken bone portion pressed inward | Typical of skull fracture |
Greenstick | Bone breaks incompletely | Common in children |
Bone Disorders
Osteomalacia and Rickets
Osteomalacia: Poorly mineralized bones; soft, weak, painful.
Rickets: Osteomalacia in children; bowed legs, bone deformities; caused by vitamin D deficiency or insufficient calcium.
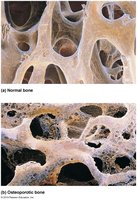
Osteoporosis
Bone resorption exceeds deposit; bone mass declines; vertebral and hip fractures common.
Risk factors: age, postmenopausal women, petite body form, poor diet, smoking, hormone-related conditions.
Treatments: calcium, vitamin D, exercise, hormone therapy, bisphosphonates, selective estrogen receptor modulators, denosumab.
Prevention: adequate calcium, reduced alcohol, weight-bearing exercise.
Paget’s Disease
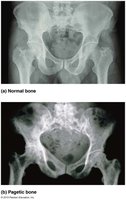
Excessive, haphazard bone deposit and resorption; high ratio of spongy to compact bone; reduced mineralization.
Occurs in spine, pelvis, femur, skull; rare before age 40; cause unknown.
Treatment: calcitonin and bisphosphonates.
Developmental Aspects of Bone
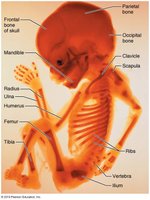
Embryonic skeleton ossifies predictably; fetal age determined by X-rays or sonograms.
Most long bones ossify by 8 weeks; primary ossification centers by week 12.
At birth, most long bones ossified except at epiphyses; epiphyseal plates persist through childhood and adolescence.
At ~25 years, all bones are completely ossified; skeletal growth ceases.
Bone formation exceeds resorption in children/adolescents; balanced in young adults; resorption exceeds formation in adults.
Bone density changes are largely genetic; bone mass, mineralization, and healing decrease with age.