 뒤로
Chapter 7D: The Skeleton – Pelvic Girdle and Lower Limb
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
The Pelvic Girdle
Structure and Function of the Pelvic Girdle
The pelvic girdle, also known as the hip girdle, is a robust structure that connects the lower limbs to the axial skeleton. It is formed by two hip bones (coxal bones or os coxae) and the sacrum. The pelvic girdle transmits the weight of the upper body to the lower limbs and supports pelvic organs. Compared to the shoulder joint, it offers less mobility but greater stability, which is essential for weight-bearing and locomotion.
Attachment: Lower limbs are attached to the axial skeleton via strong ligaments.
Function: Supports pelvic organs and transmits body weight.
Stability: More stable than the shoulder joint due to its function in weight-bearing.
Coxal Bones
Components of the Coxal Bone
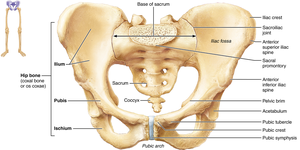
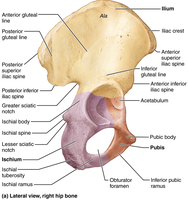
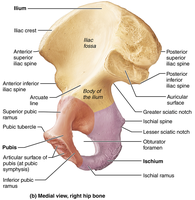
Each coxal bone is formed by the fusion of three bones: the ilium, ischium, and pubis. These bones contribute to the structure and function of the hip.
Ilium: The superior region; articulates with the sacrum at the auricular surface (sacroiliac joint).
Ischium: The posteroinferior part; provides support when sitting.
Pubis: The anterior portion; joins at the pubic symphysis.
Acetabulum: Deep socket formed at the point of fusion; receives the head of the femur.
Pelvis
Structure of the Pelvis
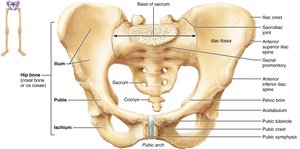
The pelvis is formed by the hip bones, sacrum, and coccyx. It provides a strong, stable base for the vertebral column and supports the weight of the upper body.
Pelvic brim (pelvic inlet): Continuous oval ridge defining the boundary between the false and true pelvis.
False pelvis: Superior to the pelvic brim; supports abdominal organs.
True pelvis: Inferior to the pelvic brim; forms the birth canal.
Pelvic outlet: Inferior margin of the true pelvis.
Pelvic Structure and Childbearing
Differences Between Male and Female Pelves
The structure of the pelvis differs between males and females, reflecting functional adaptations for childbearing. The female pelvis is wider, shallower, lighter, and rounder, which facilitates childbirth.
Female pelvis: Adapted for childbearing; wider and rounder.
Male pelvis: More robust and narrower; adapted for support and locomotion.
Pelvic arch (subpubic angle): Main difference between male and female pelves.
Comparison Table: Male vs. Female Pelvis
The following table summarizes the key differences between male and female pelves:
Feature | Male Pelvis | Female Pelvis |
|---|---|---|
General Structure | Heavier, thicker | Lighter, thinner |
Pelvic Inlet | Narrow, heart-shaped | Wide, oval |
Pelvic Outlet | Narrow | Wide |
Pubic Arch | Acute angle (<90°) | Obtuse angle (>90°) |
Acetabula | Large, close together | Small, farther apart |
Sacrum | Long, narrow | Short, wide |
Coccyx | Less movable, curves forward | More movable, straighter |
The Lower Limb
Overview of Lower Limb Structure
The lower limb consists of three segments: the thigh, leg, and foot. It carries the entire weight of the erect body and is subjected to exceptional forces during activities such as jumping or running.
Thigh: Contains the femur.
Leg: Contains the tibia and fibula.
Foot: Contains tarsal, metatarsal, and phalangeal bones.
Thigh: The Femur
The femur is the largest and strongest bone in the body, making up about one-fourth of a person’s height. It articulates proximally with the acetabulum of the hip and distally with the tibia and patella.
Fovea capitis: Small pit in the head for ligament attachment.
Greater and lesser trochanters: Muscle attachment sites.
Linea aspera: Ridge for muscle attachment.
Medial and lateral condyles: Articulate with tibia.
Patella: Sesamoid bone in quadriceps tendon; protects knee joint.
Leg: Tibia and Fibula
The leg is made up of two parallel bones: the tibia and fibula, connected by an interosseous membrane. The tibia is the medial leg bone and receives the weight of the body from the femur, transmitting it to the foot. The fibula is not weight-bearing and does not articulate with the femur.
Tibia: Medial and lateral condyles, intercondylar eminence, tibial tuberosity, anterior border, medial malleolus, fibular notch.
Fibula: Head, lateral malleolus.
Foot: Tarsus, Metatarsus, and Phalanges
The skeleton of the foot includes the tarsus, metatarsus, and phalanges. The tarsus consists of seven tarsal bones, with the talus and calcaneus bearing most of the body weight. The metatarsals are five bones numbered I–V, and the phalanges are fourteen bones forming the toes.
Tarsus: Talus, calcaneus, cuboid, navicular, and three cuneiform bones.
Metatarsals: Five bones; metatarsal I forms the ball of the foot.
Phalanges: Digit I (hallux) has two bones; digits II–V have three bones each.
Arches of the Foot
The foot has three arches maintained by interlocking bones, ligaments, and tendons. These arches allow the foot to bear weight efficiently.
Lateral longitudinal arch: Low curve elevates lateral part of foot.
Medial longitudinal arch: Curves upward.
Transverse arch: Runs obliquely from one side of the foot to the other.
Developmental Aspects of the Skeleton
Infant Skull and Fontanelles
The infant skull has more bones than the adult skull, with unfused mandible and frontal bones. Skull bones are connected by fontanelles, which are unossified remnants of fibrous membranes that ease birth and allow brain growth.
Fontanelles: Anterior, posterior, mastoid, and sphenoidal.
Growth and Proportions
At birth, the cranium is large relative to the face. By nine months, the cranium is half the adult size. Arms and legs grow faster than the head and trunk, leading to adult proportions.
Spinal Curvatures
Primary curvatures of the thorax and sacrum are convex at birth, resulting in a C-shaped spine. Secondary curvatures of the cervical and lumbar regions develop as the child grows.
Aging and the Skeleton
As humans age, intervertebral discs become thinner, less hydrated, and less elastic, increasing the risk of disc herniation. Height loss, ossification of costal cartilages, and increased fracture risk are common.
Disc herniation: Increased risk with age.
Bone mass: Decreases, increasing fracture risk.
Clinical Aspects
Bimalleolar Fracture
A bimalleolar fracture is a break in the distal ends of both the tibia and fibula, commonly occurring as a sports injury.
Flat Foot (Pes Planus)
Flat foot may be congenital or acquired, caused by age, obesity, or high-impact activities. Proper footwear and orthotic inserts can help manage symptoms.
Cleft Palate
Cleft palate is a congenital abnormality where there is no medial fusion of the right and left halves of the palate, interfering with sucking and potentially leading to aspiration pneumonia.
Developmental Dysplasia of the Hip (DDH)
DDH occurs in up to 2% of newborns and includes partial or complete dislocation of the femoral head and poorly developed acetabulum. High-risk infants include those with breech births. Treatment involves ultrasound, harnesses, casting, or surgery.
Summary Table: Bones of the Pelvic Girdle and Lower Limb
Region | Bones | Key Features |
|---|---|---|
Pelvic Girdle | Ilium, Ischium, Pubis | Acetabulum, pubic symphysis, sacroiliac joint |
Thigh | Femur | Head, neck, trochanters, condyles |
Leg | Tibia, Fibula | Condyles, malleoli, interosseous membrane |
Foot | Tarsals, Metatarsals, Phalanges | Arches, ball of foot, hallux |
