 뒤로
Chapter 9: Muscles and Muscle Tissue – Study Guide
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
Muscle Tissue Types
Overview of Muscle Tissue
Muscle tissue is essential for movement, posture, and various bodily functions. The prefixes myo-, mys-, and sarco- are commonly used in muscle terminology. There are three main types of muscle tissue: skeletal, cardiac, and smooth. Muscle fibers are elongated cells found in skeletal and smooth muscle, but not in cardiac muscle.
Skeletal Muscle: Attached to bones and skin, longest fibers, striated, voluntary, rapid and powerful contractions.
Cardiac Muscle: Found only in the heart, striated, involuntary, contracts at a steady rate due to pacemaker.
Smooth Muscle: Found in walls of hollow organs (e.g., stomach, bladder, airways), non-striated, involuntary.
Key words: Skeletal (skeletal, striated, voluntary), Cardiac (cardiac, striated, involuntary), Smooth (visceral, nonstriated, involuntary).
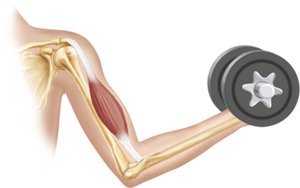
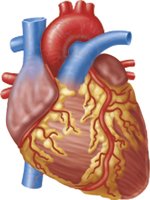
Characteristics and Functions of Muscle Tissue
Characteristics
All muscle tissues share four main characteristics:
Excitability: Ability to receive and respond to stimuli.
Contractility: Ability to shorten forcibly when stimulated.
Extensibility: Ability to be stretched.
Elasticity: Ability to recoil to resting length.
Functions
Produce movement: Responsible for locomotion and manipulation (e.g., walking, digesting, pumping blood).
Maintain posture and body position.
Stabilize joints.
Generate heat: As muscles contract.
Skeletal Muscle Structure
Nerve and Blood Supply
Each skeletal muscle receives a nerve, artery, and veins. Nerves supply every muscle fiber for conscious control. Contracting fibers require large amounts of oxygen and nutrients, and waste removal is essential.
Connective Tissue Sheaths
Muscles and fibers are covered by connective tissue sheaths, which support and reinforce the muscle:
Epimysium: Surrounds entire muscle; dense irregular connective tissue.
Perimysium: Surrounds fascicles (groups of muscle fibers); fibrous connective tissue.
Endomysium: Surrounds each muscle fiber; fine areolar connective tissue.
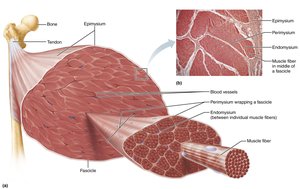
Attachments
Direct (fleshy) attachments: Epimysium fused to periosteum of bone or perichondrium of cartilage.
Indirect attachments: Connective tissue wrappings extend beyond muscle as tendons or aponeuroses.
Skeletal Muscle Fiber Anatomy
Microscopic Anatomy
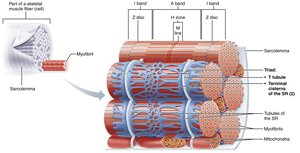
Skeletal muscle fibers are long, cylindrical cells with multiple nuclei. The sarcolemma is the plasma membrane, and the sarcoplasm is the cytoplasm, containing glycosomes (glycogen storage) and myoglobin (oxygen storage).
Myofibrils: Densely packed rodlike elements, responsible for striations and contraction.
Sarcoplasmic reticulum: Smooth endoplasmic reticulum, stores and releases calcium.
T tubules: Extensions of sarcolemma, transmit electrical impulses.
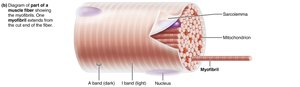
Striations and Sarcomeres
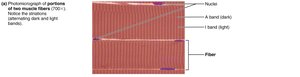
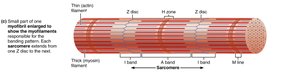
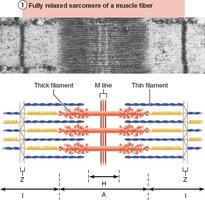
Striations are formed by repeating series of dark (A bands) and light (I bands) regions. The sarcomere is the smallest contractile unit, defined as the area between two Z discs. Sarcomeres align end-to-end along myofibrils.
Myofilaments
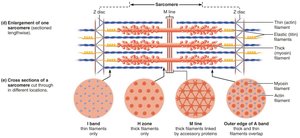
Myofilaments are organized within the sarcomere:
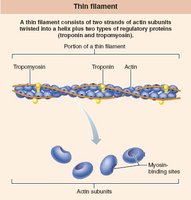
Actin (thin) filaments: Extend across I band and partway into A band, anchored to Z discs.
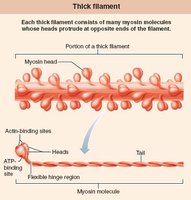
Myosin (thick) filaments: Extend length of A band, connected at M line.
Clinical Focus: Duchenne Muscular Dystrophy
Pathophysiology
Duchenne muscular dystrophy (DMD) is a severe, sex-linked recessive disease affecting mostly males. It is caused by a defective gene for dystrophin, a protein that stabilizes the sarcolemma. The disease leads to muscle degeneration, weakness, and loss of muscle mass.
Symptoms appear between ages 2 and 7.
Progresses from extremities to head, chest, and cardiac muscle.
No cure; supportive care and corticosteroids offer temporary relief.
Gene therapy approved in 2023.
Sarcoplasmic Reticulum and T Tubules
Structure and Function
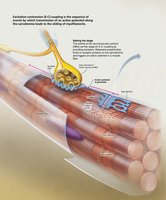
The sarcoplasmic reticulum (SR) surrounds each myofibril and regulates intracellular calcium levels. Terminal cisterns form cross channels at A–I band junctions. T tubules are extensions of the sarcolemma that allow electrical signals to penetrate deep into the muscle fiber.
Triad: Consists of two terminal cisterns and one T tubule.
SR proteins control calcium channel opening; T tubule proteins act as voltage sensors.
Electrical impulses trigger calcium release, initiating contraction.
Sliding Filament Model of Contraction
Mechanism
Contraction occurs when cross bridges form between myosin and actin, generating force. The sliding filament model states that thin filaments slide past thick filaments, increasing overlap without changing filament length.
Myosin heads bind to actin, forming cross bridges.
Cross bridges attach and detach, pulling thin filaments toward the center.
Results in shortening of muscle fiber: I bands shorten, Z discs move closer, H zones disappear, A bands move closer.

Motor Neurons and Muscle Contraction
Neuromuscular Junction
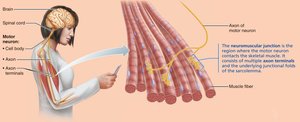
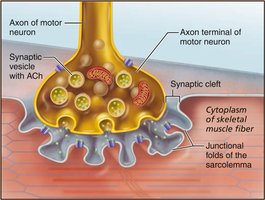
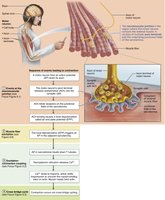
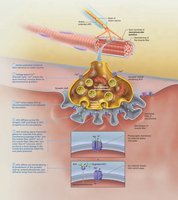
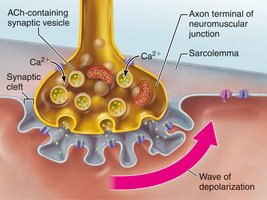
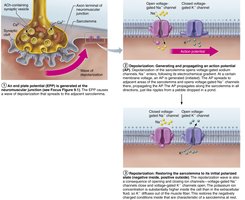
Motor neurons stimulate skeletal muscle fibers to contract. The neuromuscular junction (NMJ) is the site where the motor neuron communicates with the muscle fiber via the neurotransmitter acetylcholine (ACh).
Axon terminals release ACh into the synaptic cleft.
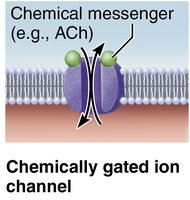
ACh binds to receptors on the sarcolemma, opening chemically gated ion channels.
Infoldings of sarcolemma (junctional folds) increase surface area for ACh receptors.
Generation of Action Potential
Steps
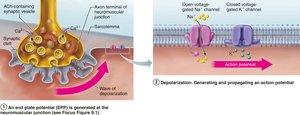
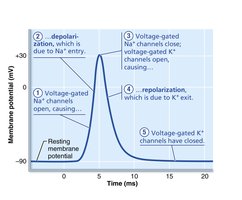
The action potential (AP) is generated and propagated across the sarcolemma, leading to muscle contraction. The process involves:
End plate potential: Local depolarization caused by ACh binding.
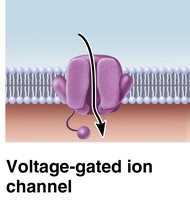
Depolarization: If threshold is reached, voltage-gated channels open, AP is generated.
Repolarization: Restoration of resting membrane potential via ion pumps.
Excitation-Contraction Coupling
Process
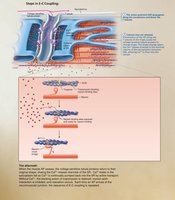
Excitation-contraction (E-C) coupling links the AP to muscle contraction. The AP travels along the sarcolemma and into T tubules, triggering calcium release from the SR. Calcium binds to troponin, moving tropomyosin and allowing myosin to bind to actin.
Cross Bridge Cycling
Steps
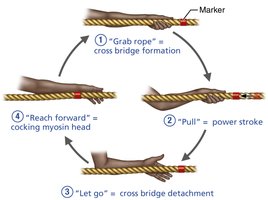
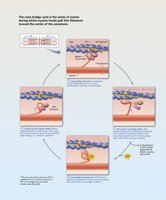
The cross bridge cycle is essential for muscle contraction:
Cross bridge formation: Myosin head attaches to actin.
Power stroke: Myosin head pivots, pulling actin toward M line.
Detachment: ATP binds to myosin, causing detachment.
Cocking: ATP hydrolysis re-cocks myosin head.
Clinical Focus: Rigor Mortis
Mechanism
Rigor mortis occurs 3–4 hours after death due to increased intracellular calcium and lack of ATP, resulting in sustained muscle contraction until proteins break down.
Whole Muscle Contraction
Motor Units
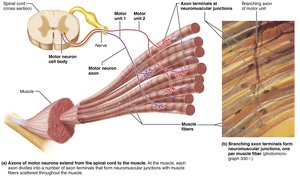
A motor unit consists of a motor neuron and all the muscle fibers it innervates. Smaller motor units allow for fine control, and fibers are distributed throughout the muscle.
Muscle Twitch
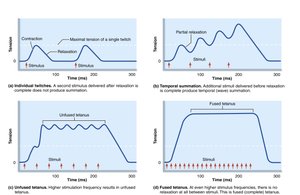
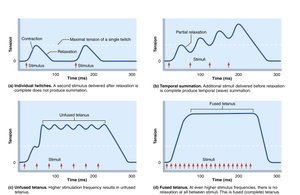
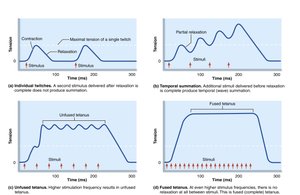
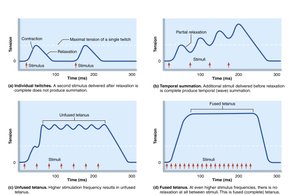
A muscle twitch is the response to a single AP. It has three phases:
Latent period: Excitation-contraction coupling.
Contraction: Cross bridge formation, tension increases.
Relaxation: Calcium reentry into SR, tension declines.


Graded Muscle Contractions
Frequency and Strength
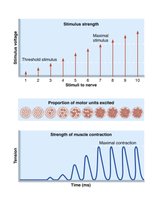
Graded responses allow muscles to vary contraction strength. This is achieved by changing the frequency and strength of stimulation.
Temporal (wave) summation: Rapid stimuli increase force.
Unfused tetanus: Sustained, quivering contraction.
Fused tetanus: Smooth, sustained contraction plateau.
Recruitment: More motor units activated for stronger contraction.
Muscle Tone and Types of Contraction
Muscle Tone
Muscle tone is a constant, slightly contracted state due to spinal reflexes, keeping muscles firm and ready to respond.
Isotonic and Isometric Contractions
Isotonic: Muscle changes length and moves load (concentric: shortens, eccentric: lengthens).
Isometric: Muscle tension increases, but muscle does not shorten.
ATP and Muscle Contraction
Energy Sources
ATP is essential for muscle contraction, cross bridge detachment, calcium pumping, and restoring ionic balance. ATP is regenerated by:
Direct phosphorylation: Creatine phosphate donates phosphate to ADP.
Anaerobic pathway: Glycolysis and lactate formation.
Aerobic pathway: Glycolysis and aerobic respiration in mitochondria.
Muscle Fatigue and Recovery
Fatigue
Muscle fatigue is the inability to contract despite stimulation. Causes include ionic imbalances, increased inorganic phosphate, decreased ATP, increased magnesium, and decreased glycogen.
Excess Postexercise Oxygen Consumption (EPOC)
After exercise, muscles require extra oxygen to replenish reserves, convert lactate, restore glycogen, and resynthesize ATP and creatine phosphate.
Factors Affecting Muscle Contraction
Force
Force depends on:
Frequency of stimulation
Number of fibers stimulated (recruitment)
Size of muscle fibers
Degree of muscle stretch (length-tension relationship)
Velocity and Duration
Influenced by muscle fiber type, load, and recruitment:
Slow oxidative fibers: Endurance, posture.
Fast oxidative fibers: Medium-intensity activities.
Fast glycolytic fibers: Intense, powerful movements.
Muscle Response to Exercise
Aerobic and Resistance Exercise
Aerobic exercise: Increases capillaries, mitochondria, myoglobin; improves endurance and strength.
Resistance exercise: Causes hypertrophy, increases strength and size, increases mitochondria, myofilaments, glycogen, and connective tissue.
Disuse Atrophy
Muscles must be active to remain healthy. Disuse atrophy leads to degeneration and loss of mass, and rehabilitation may become impossible if muscle is replaced by fibrous tissue.
