 뒤로
Epidemiology and Control of Infectious Diseases: Herd Immunity, Transmission, and Nosocomial Infections
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
Epidemiology and Herd Immunity
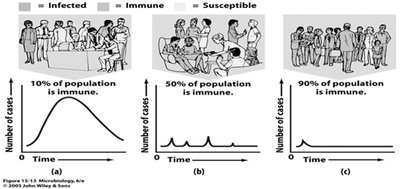
Definition and Importance of Herd Immunity
Herd immunity refers to the proportion of individuals in a population who are immune to a contagious disease, either through vaccination or recovery from illness. This collective immunity helps protect those who are not immune by reducing the spread of the disease.
Key Point 1: Herd immunity is only applicable to contagious diseases (e.g., not tetanus).
Key Point 2: High levels of herd immunity can lead to the elimination of diseases, as seen with smallpox and the ongoing efforts against polio.
Example: When a significant portion of the population is immune, outbreaks are less likely to occur, protecting vulnerable individuals.
Global Progress in Disease Elimination
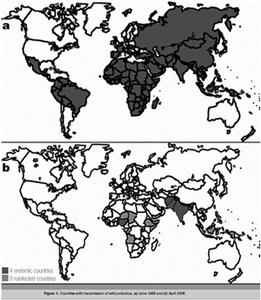
Efforts to eradicate diseases such as polio have significantly reduced the number of endemic countries worldwide. Vaccination campaigns and herd immunity are central to these achievements.
Key Point: In 1988, polio was endemic in 125 countries; by 2014, only three countries remained endemic, though re-introduction remains a risk.
Controlling Transmission of Infectious Diseases
Isolation and Quarantine
Controlling the spread of infectious diseases involves several strategies, including isolation and quarantine. Isolation prevents contact between infected patients and the general population, while quarantine separates healthy but exposed individuals during the incubation period.
Key Point 1: Isolation is critical in both clinical and laboratory settings to prevent transmission.
Key Point 2: Quarantine is less common today but was effective during outbreaks such as SARS in 2003.
Summary of Important Isolation Procedures
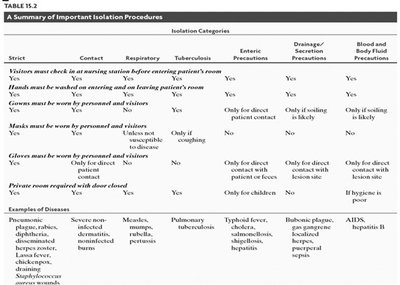
Isolation procedures vary depending on the category of infection and include strict, contact, respiratory, tuberculosis, enteric, drainage/secretion, and blood/body fluid precautions. These procedures are designed to minimize the risk of transmission in healthcare settings.
Isolation Category | Visitor Check-in | Handwashing | Gown | Mask | Gloves | Private Room |
|---|---|---|---|---|---|---|
Strict | Yes | Yes | Yes | Yes | Yes | Yes |
Contact | No | Yes | Yes | No | Only for direct contact | Yes |
Respiratory | No | Yes | No | Yes | No | Yes |
Tuberculosis | No | Yes | No | Only if coughing | No | Yes |
Enteric | No | Yes | No | No | Only for direct patient contact | Only for children |
Drainage/Secretion | No | Yes | No | Only if soiling is likely | Only for direct patient contact | No |
Blood/Body Fluid | No | Yes | No | Only if soiling is likely | Yes | No |
Biosafety Levels in Laboratory Settings
Biosafety levels (BSL) are classifications for laboratory practices and containment based on the risk posed by the microorganisms handled. There are four levels, each with specific requirements:
BSL-1: Nonpathogenic organisms; standard microbiological practices; open bench tops.
BSL-2: Pathogenic to humans; open bench tops; specific training required.
BSL-3: Serious disease by inhalation; biological safety cabinets or personal protective equipment.
BSL-4: Dangerous/exotic agents; life-threatening disease; separate building or controlled area; suits with life support systems.


Nosocomial (Health-Care Associated) Infections
Definition and Impact
Nosocomial infections, also known as health-care associated infections (HAI), are acquired in hospitals or healthcare settings. They affect approximately 10% of patients, resulting in significant morbidity and mortality.
Key Point: Sources can be exogenous (from outside the patient) or endogenous (from the patient's own flora).
Susceptibility: Compromised hosts, breaks in skin or mucous membranes, debilitated or immunosuppressed patients are at higher risk.
Transmission: Varies and can involve direct contact, contaminated equipment, or vectors.
Universal Precautions
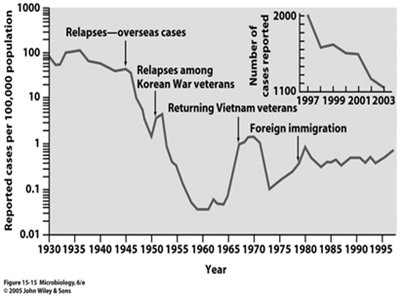
Universal precautions are procedures designed to prevent transmission of infections in healthcare settings, especially when contact with body fluids is possible.
Key Point: Includes handwashing, use of gloves, masks, gowns, and safe handling of sharps.
Precaution | Description |
|---|---|
Gloves and gowns | Wear if soiling of hands, skin, or clothing with blood/body fluids is likely. |
Masks and eyewear | Wear when splashing or splattering of blood/body fluids is likely. |
Handwashing | Before and after patient contact; after glove removal. |
Sharps disposal | Use special containers; do not bend, clip, or recap needles. |
Cleaning spills | Use gloves and barriers; disinfect with bleach solution. |
Common Sites and Microorganisms in Nosocomial Infections
Nosocomial infections commonly affect specific sites and are caused by a range of microorganisms, often normal flora or opportunistic pathogens.
Common Sites: Urinary tract, surgical site, bloodstream, pneumonia, and others.
Common Microorganisms: Escherichia coli, Staphylococcus aureus, Pseudomonas aeruginosa, Streptococcus, Klebsiella, Enterobacter, Staphylococcus epidermidis, Bacteroides, Serratia, Candida.
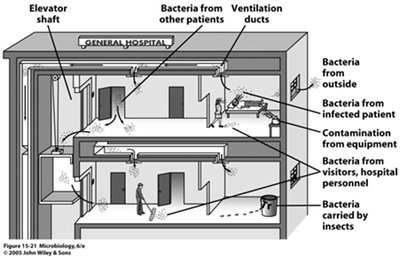

Prevention and Control of Nosocomial Infections
Effective prevention and control measures include infection-control specialists, handwashing, sterile equipment, use of gloves, and insect control.
Key Point: Handwashing is the most important preventive measure.
Case Study: Nosocomial Infection
Clinical Presentation and Diagnosis
A 53-year-old man with Guillain-Barré syndrome, hospitalized for two months, developed a nosocomial infection. He had a bedsore with blue-green pus, was previously treated for bloodstream infections, and presented with shortness of breath, chest pain, shock, and fever.
Key Point: Blood cultures and bedsore cultures confirmed Pseudomonas aeruginosa infection, a gram-negative rod often resistant to antibiotics and producing a blue-green pigment.
Example: Pseudomonas aeruginosa is commonly found in burns, sepsis, and cystic fibrosis cases.
Bioweapons and Bioterrorism
Historical and Modern Context
Bioweapons have been used historically and are now regulated by international conventions. Bioterrorism preparedness involves training healthcare workers and ensuring access to vaccines and medicines.
Geneva Protocol (1925): Prohibited use of asphyxiating gas and biological agents.
Biological and Toxins Weapons Convention (1972): Bans development, production, stockpiling, and use of biological weapons.
Chemical Weapons Convention (1993): Bans chemical weapons; signed by 184 countries.
CDC Categories of Bioterrorism Agents
Category A: High-priority agents (e.g., anthrax, botulism, plague, smallpox, tularemia, viral hemorrhagic fevers) with high mortality and potential for public panic.
Category B: Moderately easy to spread, moderate morbidity, low mortality (e.g., food/water safety threats, zoonoses, rickettsial diseases, toxins).
Category C: Emerging infectious diseases that may be engineered for mass spread (e.g., Nipah virus, hantavirus).
Additional info: Bioterrorism can also target agricultural crops, causing economic and food loss.
