 뒤로
Skeletal Muscle Tissue and the Muscular System: Structure, Function, and Physiology
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
Skeletal Muscle Tissue
Types of Muscle Tissue
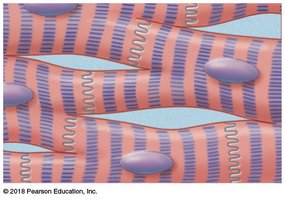
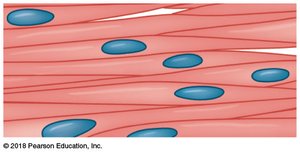
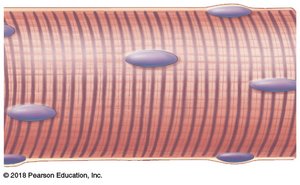
There are three main types of muscle tissue in the human body, each with distinct structural and functional characteristics:
Cardiac Muscle: Involuntary, found only in the heart, characterized by branched, striated fibers and intercalated discs.
Smooth Muscle: Involuntary, located in the walls of hollow organs and blood vessels, composed of spindle-shaped, uninucleate cells.
Skeletal Muscle: Voluntary, attached to bones, composed of cylindrical, multinucleate fibers with striations. Responsible for movement by acting on the skeleton as levers.
Functions of Skeletal Muscle Tissue
Produce movement by pulling on bones
Maintain posture and body position
Support soft tissues
Guard entrances and exits (e.g., sphincters)
Maintain body temperature (thermogenesis)
Store nutrient reserves (glycogen)
Structure of Skeletal Muscle
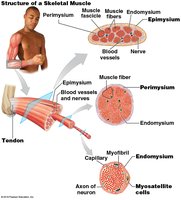
Skeletal muscle is a complex organ composed of muscle tissue, connective tissue, nerves, and blood vessels. The organization of these components is essential for muscle function.
Epimysium: Dense layer of collagen fibers surrounding the entire muscle.
Perimysium: Connective tissue that divides the muscle into fascicles (bundles of muscle fibers).
Endomysium: Areolar connective tissue that wraps each individual muscle fiber (cell).
Each muscle fiber contains myofibrils (bundles of protein filaments).
Development of Skeletal Muscle
Skeletal muscle fibers develop from embryonic cells called myoblasts:
Myoblasts fuse to form large, multinucleate muscle fibers.
Some myoblasts remain as myosatellite cells in the endomysium, which can divide and fuse to repair or replace injured muscle fibers.
Mature muscle fibers can be up to 30 cm (12 inches) long and contain up to 100 nuclei, allowing for rapid protein synthesis required for contraction.
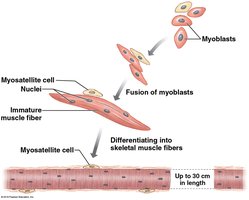
Key Terms in Muscle Cell Structure
Muscle fiber: Another term for a muscle cell.
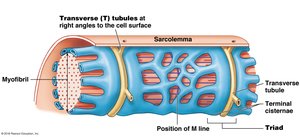
Sarcolemma: The cell membrane of a muscle fiber.
Sarcoplasm: The cytoplasm of a muscle fiber.
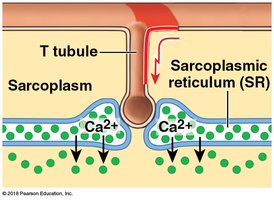
T-tubules (Transverse tubules): Extensions of the sarcolemma that penetrate into the cell, allowing action potentials to reach the interior.
Sarcoplasmic Reticulum (SR): Specialized smooth endoplasmic reticulum that stores calcium ions and forms cisterns adjacent to T-tubules.
Myofibrils: Bundles of myofilaments (thin and thick filaments) responsible for muscle contraction.
Myofilaments: Protein filaments (actin and myosin) that make up myofibrils.
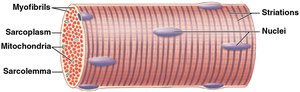
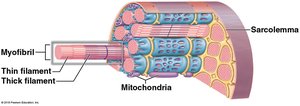
Sarcomere Structure
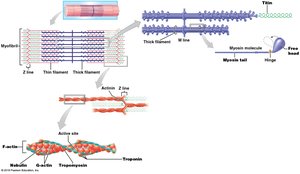
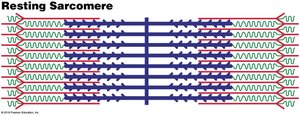
The sarcomere is the basic contractile unit of a myofibril, responsible for the striated appearance of skeletal muscle. Sarcomeres are composed of repeating arrangements of thin (actin) and thick (myosin) filaments.
Actin: Thin filament
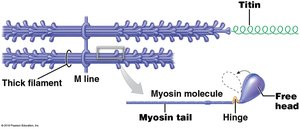
Myosin: Thick filament
Sarcomeres are separated by Z lines.
The arrangement of filaments creates distinct bands (A band, I band, H zone, M line).
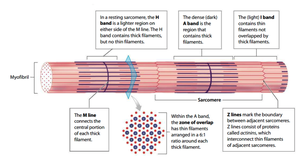
Structure of Thick and Thin Filaments
Thick Filament (Myosin): Composed of ~300 myosin molecules, each with two twisted subunits. The core contains titin, which connects to Z-lines and provides elasticity.
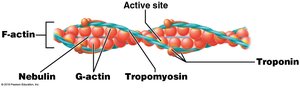
Thin Filament (Actin): Anchored to the Z-line by actinin and composed of four main proteins:
F-actin: Two strands of G-actin subunits.
Nebulin: Holds F-actin strands together.
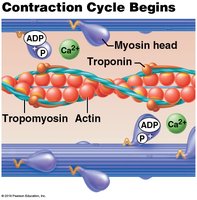
Tropomyosin: Covers myosin binding sites on actin.
Troponin: Binds to tropomyosin and G-actin; has a calcium-binding site.
Arrangement of Filaments in the Sarcomere
The precise arrangement of thick and thin filaments within the sarcomere is essential for muscle contraction. The overlap between these filaments determines the muscle's ability to generate tension.
The Sliding Filament Theory
The sliding filament theory explains how muscles contract:
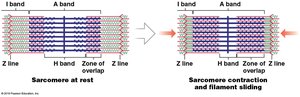
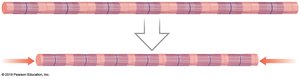
Thin filaments slide past thick filaments, shortening the sarcomere.
H and I bands decrease in size, while the A band remains constant.
Z lines move closer together, resulting in muscle contraction.
All sarcomeres in a myofibril contract simultaneously.
Muscle Cell Excitability and Contraction
Resting Membrane Potential
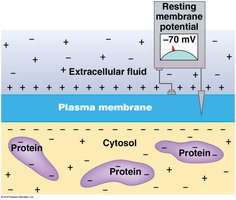
Muscle cells maintain a resting membrane potential due to the action of the Na+/K+ pump, which creates a polarized state (more positive outside, more negative inside). For skeletal muscle, this value is typically around -85 mV.
Na+/K+ pump: Moves 3 Na+ out and 2 K+ in.
Large, negatively charged proteins inside the cell contribute to the negative charge.
Action Potential and Depolarization
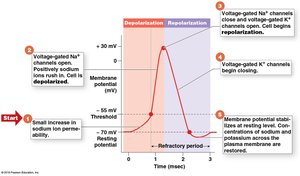
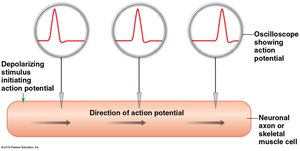
When a muscle cell is stimulated, ligand-gated Na+ channels open in response to acetylcholine (ACh) from a motor neuron, allowing Na+ to enter and depolarize the cell. If threshold is reached, voltage-gated Na+ and K+ channels open, generating an action potential.
The Neuromuscular Junction (NMJ)
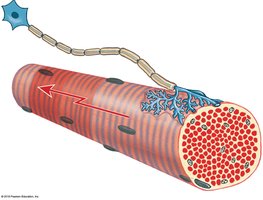
The NMJ is the synapse between a motor neuron and a skeletal muscle fiber. It is essential for translating neural signals into muscle contraction.
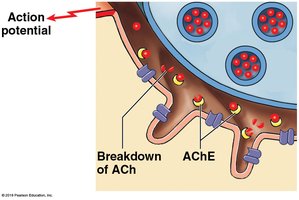
Axon terminal: Releases ACh into the synaptic cleft.
Synaptic cleft: Space between neuron and muscle fiber.
Motor end plate: Region of sarcolemma with ACh receptors and Na+ channels.
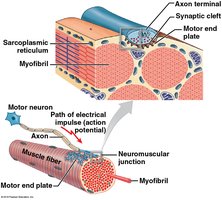
Sequence of Events at the NMJ
ACh is released from the motor neuron into the synaptic cleft.
ACh binds to receptors on the muscle fiber, opening Na+ channels and depolarizing the membrane.
ACh is broken down by acetylcholinesterase, ending the signal.
If threshold is reached, an action potential travels across the sarcolemma and down T-tubules.
The sarcoplasmic reticulum releases Ca2+, initiating contraction (excitation-contraction coupling).
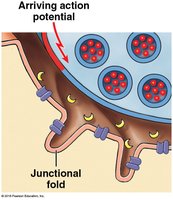
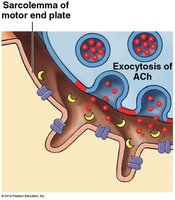
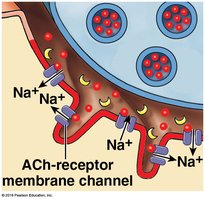
Excitation-Contraction Coupling
This process links the generation of an action potential in the sarcolemma to the contraction of the muscle fiber. The key steps are:
Neural control (motor neuron action potential)
Excitation (ACh release and sarcolemma depolarization)
Calcium ion release from the SR
Contraction cycle begins (cross-bridge formation)
Sarcomeres shorten
Muscle tension is produced
The Contraction Cycle
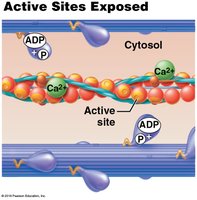
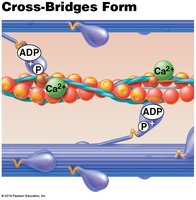
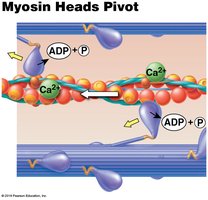
Once Ca2+ binds to troponin, the contraction cycle proceeds as follows:
Active sites on actin are exposed.
Myosin heads form cross-bridges with actin.
Myosin heads pivot, pulling actin filaments toward the M line (power stroke).
ATP binds to myosin, causing cross-bridge detachment.
Myosin hydrolyzes ATP, re-cocking the head for another cycle.
The cycle continues as long as Ca2+ and ATP are available.
Muscle Tension and Contraction Types
Muscle Tension
Muscle tension is the force generated by muscle contraction. The amount of tension depends on:
The length of the sarcomeres (degree of overlap between thick and thin filaments).
The number of muscle fibers stimulated (motor unit recruitment).
Muscle Twitch and Phases
A muscle twitch is a single stimulus-contraction-relaxation sequence in a muscle fiber. It consists of three phases:
Latent Period: Action potential stimulates sarcolemma; Ca2+ released from SR.
Contraction Phase: Ca2+ binds to troponin; cross-bridge cycling and tension development.
Relaxation Phase: Ca2+ returns to SR; cross-bridges detach; tension decreases.
Types of Muscle Contractions
Isotonic Contraction: Muscle changes length (shortens or lengthens) while tension remains constant.
Concentric: Muscle shortens as tension exceeds load.
Eccentric: Muscle lengthens as tension is less than load.
Isometric Contraction: Muscle length does not change; tension never exceeds load (e.g., postural muscles).
Muscle Metabolism and Fiber Types
ATP and Muscle Contraction
Muscle contraction requires ATP, which is generated through:
Aerobic Cellular Respiration: Glycolysis, Citric Acid Cycle, Electron Transport Chain (requires oxygen).
Creatine Phosphate: Stores energy to quickly regenerate ATP from ADP.
Glycogen: Stored glucose for glycolysis and aerobic respiration.
Muscle Fiber Types
Type | Characteristics |
|---|---|
Fast (Type II) | Large, rapid contraction, fatigue quickly, pale color, lots of myofibrils and glycogen |
Slow (Type I) | Smaller, slower contraction, resist fatigue, red color, rich in myoglobin and capillaries |
Intermediate | Intermediate properties, more resistant to fatigue than fast fibers |
Clinical Correlations
Hypertrophy: Increase in muscle size due to repeated stimulation.
Atrophy: Decrease in muscle size due to disuse, aging, or nerve damage.
Muscular Dystrophy: Inherited diseases causing muscle weakness and deterioration (e.g., Duchenne, Becker).
Polio: Viral infection attacking motor neurons, causing paralysis.
Tetanus: Bacterial toxin causing sustained muscle contraction.
Botulism: Bacterial toxin blocking ACh release, causing paralysis.
Myasthenia Gravis: Autoimmune disease reducing ACh receptors, leading to muscle weakness.
Rigor Mortis: Post-mortem muscle contraction due to ATP depletion and sustained Ca2+ presence.
The Muscular System
Organization of Muscles
Axial Muscles: Support and position the axial skeleton (head, neck, trunk).
Appendicular Muscles: Support, move, and brace the limbs.
Fascicle Organization and Leverage
Parallel: Fibers run parallel to the long axis (e.g., biceps brachii).
Convergent: Fibers converge to a single tendon (e.g., pectoralis major).
Pennate: Fibers attach at an angle to a central tendon (e.g., rectus femoris).
Circular: Fibers arranged in a circle (e.g., orbicularis oris).
Muscle Actions and Terminology
Origin: Fixed attachment point of the muscle.
Insertion: Movable attachment point.
Agonist (Prime Mover): Main muscle responsible for movement.
Synergist: Assists the agonist.
Antagonist: Opposes the action of the agonist.
Major Muscle Groups
Axial Muscles: Head & neck, facial expression, extrinsic eye muscles, tongue, pharynx, vertebral column, trunk, pelvic floor.
Appendicular Muscles: Muscles of the pectoral girdle, arm, forearm, thigh, leg, and lower leg.
