 뒤로
Urinary System: Structure, Function, and Pathology
스터디 가이드 - 스마트 노트
 자료에 맞춘 맞춤형 노트, 핵심 정의, 예시, 맥락을 확장해 제공합니다.
Urinary System Overview
Introduction
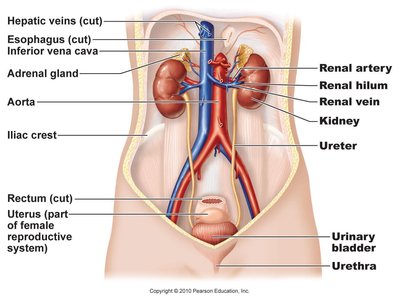
The urinary system is essential for maintaining homeostasis by filtering blood, removing waste, and regulating fluid and electrolyte balance. It consists of the kidneys, ureters, urinary bladder, and urethra.
Key Functions: Filtration of blood, elimination of waste, regulation of blood volume and pressure, acid-base balance, and hormone secretion.
Major Organs: Kidneys, ureters, bladder, urethra.

Anatomy of the Kidneys
Kidney Location and Structure
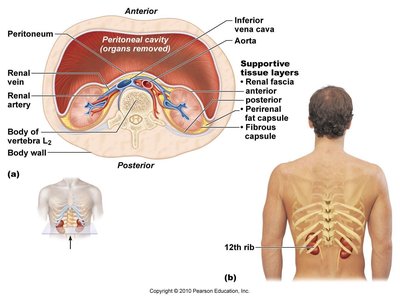
The kidneys are retroperitoneal organs located between T12 and L3 vertebrae, protected by an adipose capsule. Each kidney is about the size of a bar of soap.
Retroperitoneal: Positioned behind the peritoneum.
Adipose Capsule: Provides protection and maintains position.
Internal Anatomy of the Kidney
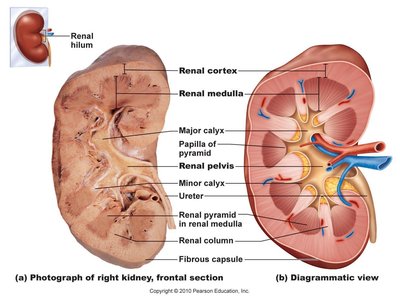
The kidney is divided into the renal cortex and renal medulla. The medulla contains renal pyramids, separated by renal columns. The renal pelvis collects urine from calyces and funnels it to the ureter.
Renal Cortex: Outer region, contains nephrons.
Renal Medulla: Inner region, contains pyramids.
Renal Pelvis: Central cavity for urine collection.
Kidney Lobe and Nephron Distribution
Each kidney lobe consists of a pyramid and overlying cortex. Nephrons, the functional units, are distributed throughout the cortex and medulla.
Nephrons: 1.2 million per kidney; responsible for urine formation.
Renal Artery: Branches into arterioles supplying nephrons.
Nephron Structure and Function
Nephron Anatomy
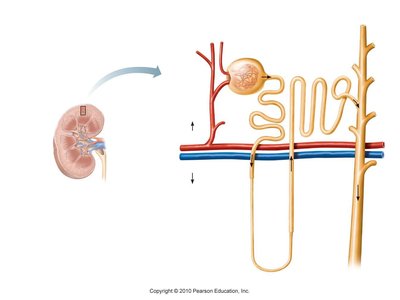
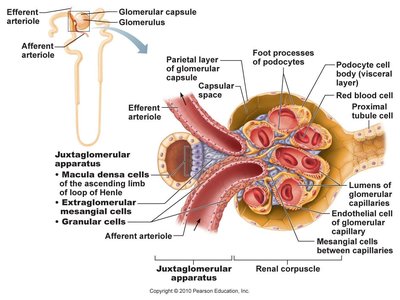
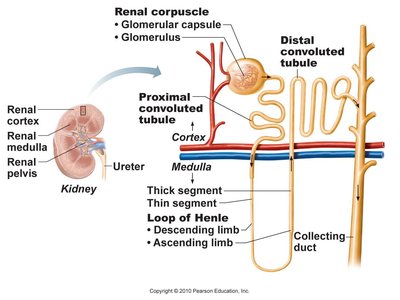
The nephron is composed of the renal corpuscle and renal tubule. The renal corpuscle includes the glomerulus and Bowman's capsule, where filtration occurs.
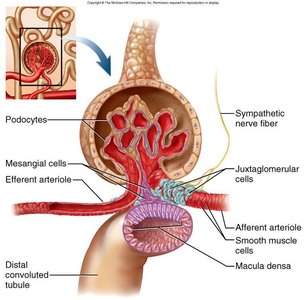
Glomerulus: Capillary bed with high blood pressure for filtration.
Bowman's Capsule: Surrounds glomerulus, collects filtrate.
Renal Tubule: Includes proximal convoluted tubule (PCT), nephron loop (Loop of Henle), distal convoluted tubule (DCT), and collecting duct (CD).
Types of Nephrons
Cortical Nephrons: 85%, short loops, close to kidney surface.
Juxtamedullary Nephrons: 15%, long loops, extend deep into medulla.
Urine Formation
Filtration Membrane
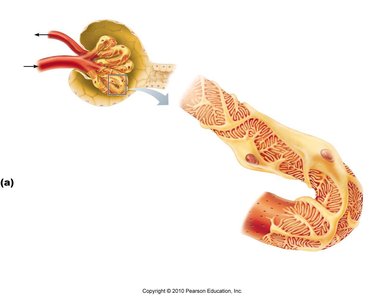
Filtration occurs at the glomerulus, where the filtration membrane consists of fenestrated endothelium, basement membrane, and podocyte filtration slits.
Small Particles: Water, electrolytes, glucose, fatty acids, amino acids, nitrogenous wastes, vitamins.
Large Particles: Albumin, blood cells (excluded).
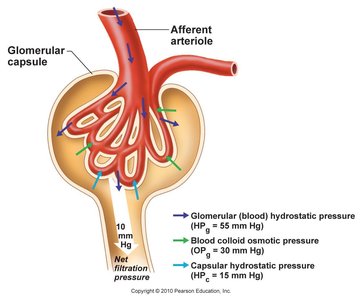
Filtration Pressure: Maintained by wider afferent arteriole compared to efferent.
Glomerular Filtration Rate (GFR)
GFR is the rate at which filtrate is formed by the kidneys.
Normal GFR: 125 ml/min (male), 105 ml/min (female).
99% Reabsorbed: Only 1-2 L urine excreted per day.
High GFR: Dehydration, electrolyte depletion.
Low GFR: Anuria, waste retention.
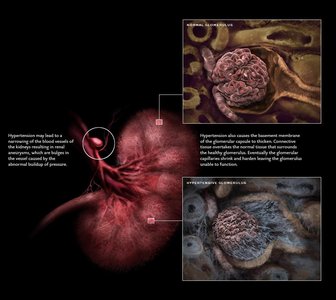
Regulation of Glomerular Filtration
GFR is regulated by autoregulation, sympathetic control, and hormonal mechanisms.
Myogenic Mechanism: Afferent arteriole constricts in response to high BP.
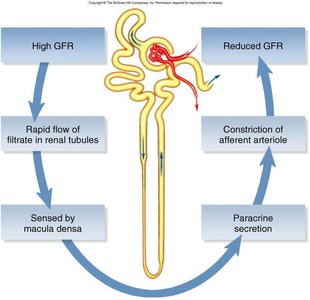
Tubuloglomerular Feedback: Macula densa monitors fluid, signals juxtaglomerular cells to constrict afferent arteriole.
Sympathetic Control: Exercise or shock constricts afferent arterioles, reduces GFR.
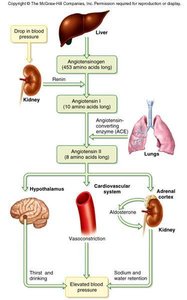
Hormonal Control: Renin-angiotensin-aldosterone system regulates BP and GFR.
Tubular Reabsorption and Secretion
Reabsorption in the Proximal Convoluted Tubule (PCT)
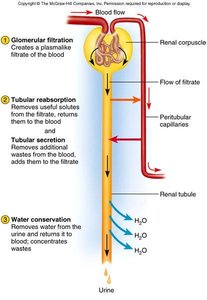
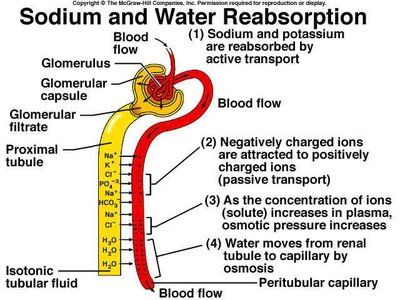
Most reabsorption occurs in the PCT, returning water and solutes to the blood.
Nutrients Reabsorbed: Glucose, amino acids, vitamins.
Peritubular Capillaries: High osmolarity and low BP favor reabsorption.
Solvent Drag: Water absorption carries solutes.
Tubular Secretion
Tubular secretion removes wastes and regulates acid-base balance.
Waste Removal: Urea, uric acid, ammonia, drugs.
Acid-Base Balance: H+ and bicarbonate ions regulate pH.
Nephron Loop (Loop of Henle)
The nephron loop establishes a salinity gradient, allowing urine concentration.
Descending Limb: Water reabsorbed, no electrolytes.
Ascending Limb: Electrolytes reabsorbed (Na+, Cl-, K+), no water.
Thick Segments: Impermeable to water, fluid becomes dilute.
DCT and Collecting Duct
Fluid reabsorption in the DCT and collecting duct is regulated by hormones.
Aldosterone: Promotes Na+ and water reabsorption, decreases urine volume, raises BP.
ADH: Increases water reabsorption, decreases urine volume.
Urine Composition and Properties
Urinalysis
Urinalysis assesses the appearance, odor, specific gravity, osmolarity, pH, and chemical composition of urine.
Normal Appearance: Odorless to deep amber, yellow due to urochrome.
Abnormal Appearance: Pyuria (cloudy), hematuria (blood).
Odor: Bacteria degrade urea to ammonia; asparagus can alter odor.
Specific Gravity: Correlates to osmolarity.
pH: Range 4.5-8.2, usually 6.0.
Chemical Composition: 95% water, 5% solutes (urea, NaCl, KCl, creatinine, uric acid).

Nitrogenous Wastes
Urea: From amino acid metabolism.
Uric Acid: From nucleic acid catabolism.
Creatinine: From creatine phosphate catabolism.
Urine Volume
Normal: 1-2 L/day.
Polyuria: >2 L/day.
Oliguria: <500 mL/day.
Anuria: 0-100 mL/day.
Diabetes and Diuretics
Diabetes Mellitus: Chronic polyuria, hyperglycemia, glycosuria.
Diabetes Insipidus: ADH hyposecretion.
Diuretics: Increase urine output, decrease blood volume; used for hypertension and heart failure.
Ureters, Bladder, and Urethra
Ureters
Ureters are muscular tubes (about 25 cm long) that transport urine from the renal pelvis to the bladder via peristalsis.
Bladder
The bladder is a distensible organ with a capacity of 500-800 mL. The trigone is a triangular area formed by the openings of the ureters and urethra, susceptible to infection.
Urethra
Female: 3-4 cm, more prone to infections.
Male: 18 cm.
Internal Sphincter: Smooth muscle, involuntary.
External Sphincter: Skeletal muscle, voluntary.
Voiding Urine (Micturition)
Stretch receptors in the bladder signal the micturition center when 200 mL urine accumulates.
Results in bladder contraction and relaxation of internal sphincter.
Voluntary control via external sphincter.
Abnormal Constituents and Pathology
Abnormal Urine Constituents
Albuminuria: Albumin in urine.
Glucosuria: Glucose in urine.
Hematuria: Blood in urine.
Pyuria: Pus in urine.
Ketonuria: Ketones in urine.
Bilirubinuria: Bilirubin in urine.
Renal Calculi: Kidney stones.
Microbes: Urinary tract infection (UTI).
Kidney Pathology
Trauma, Infection, Exercise, Hypoxia: Can cause proteinuria or hematuria.
Polycystic Kidney Disease: Genetic, causes cysts, chronic infections, kidney failure.
Kidney Stones: Hard granules of calcium, phosphate, uric acid, protein; cause pain and obstruction.
Renal Insufficiency: Inability to maintain homeostasis due to nephron destruction.
Hemodialysis: Blood filtered through semipermeable tube with dialysis fluid.
Renal Cell Carcinoma: Cancer of kidney tubule lining; symptoms include pain, abnormal urine color, swelling, weight loss.
Summary Table: Urine Constituents
Constituent | Normal | Abnormal |
|---|---|---|
Urea | Yes | No |
Creatinine | Yes | No |
Uric Acid | Yes | No |
Albumin | No | Albuminuria |
Glucose | No | Glucosuria |
Blood | No | Hematuria |
Pus | No | Pyuria |
Ketones | No | Ketonuria |
Bilirubin | No | Bilirubinuria |
Microbes | No | UTI |
Key Equations
Glomerular Filtration Rate (GFR)
GFR is determined by net filtration pressure:
Net Filtration Pressure:
Example values:
Additional info:
Urinary system is critical for excretion, osmoregulation, and acid-base balance.
Hormonal regulation (aldosterone, ADH) is essential for maintaining blood pressure and volume.
Pathologies such as diabetes, kidney stones, and renal insufficiency can severely impact homeostasis.
