 Back
Chapter 19: Management of Patients with Acute Disorders of the Chest and Lower Respiratory Tract
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Chapter 19: Management of Patients with Acute Disorders of the Chest and Lower Respiratory Tract
Definition and Overview
Atelectasis is the closure or collapse of alveoli, which impairs gas exchange and can lead to hypoxemia. It is commonly detected via chest x-ray and can be acute or chronic, with acute atelectasis most often seen postoperatively.
Key Point 1: Causes include excess secretions, mucus plugs, and shallow breathing patterns.
Key Point 2: Types: Nonobstructive (reduced ventilation) and Obstructive (blockage impeding air passage, most common type).
Example: Postoperative patients are at high risk due to pain and shallow breathing.
Clinical Manifestations
Symptoms include increasing dyspnea, cough, and sputum production. Acute cases may present with marked respiratory distress, tachycardia, tachypnea, pleural pain, and central cyanosis. Chronic cases predispose to infections.
Key Point: Physical findings: decreased breath sounds, crackles, hypoxemia.
Assessment and Diagnostic Findings
Diagnosis is based on increased work of breathing, hypoxemia, chest x-ray (patchy infiltrates), and pulse oximetry (<90% hemoglobin saturation).
Key Point: Chest x-ray is essential for detection.
Prevention and Management
Prevention focuses on frequent turning, early mobilization, deep breathing maneuvers, and incentive spirometry. Management aims to improve ventilation and remove secretions, using techniques such as positive expiratory pressure (PEP), bronchoscopy, and mechanical ventilation in severe cases.
Key Point: Incentive spirometry provides visual feedback and encourages lung expansion.
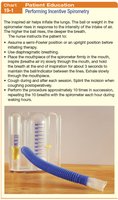
Secretion Management Techniques
Directed cough, suctioning, aerosol nebulizer treatments, chest physiotherapy (CPT), and bronchoscopy are used to clear secretions and maintain airway patency.
Key Point: Effective secretion management is crucial for recovery.
Acute Tracheobronchitis
Definition and Pathophysiology
Acute tracheobronchitis is inflammation of the trachea and bronchial tree, often following a viral upper respiratory infection. Decreased resistance can lead to secondary bacterial infection.
Key Point: Common causative organisms: Streptococcus pneumoniae, Haemophilus influenzae, Mycoplasma pneumoniae.
Example: Fungal infections (e.g., Aspergillus) may also cause tracheobronchitis.
Clinical Manifestations
Initial symptoms include dry, irritating cough, sternal soreness, fever, chills, night sweats, headache, and malaise. Progressive symptoms: shortness of breath, stridor, wheeze, purulent sputum.
Key Point: Sputum may be blood-streaked in severe cases.
Medical and Nursing Management
Treatment includes antibiotics (if bacterial), increased fluid intake, suctioning, bronchoscopy, and symptomatic measures (cool vapor therapy, moist heat, analgesics). Nursing care emphasizes bronchial hygiene, rest, and completion of antibiotics.
Key Point: Avoid overexertion to prevent relapse.
Pneumonia
Definition and Classification
Pneumonia is inflammation of the lung parenchyma caused by bacteria, mycobacteria, fungi, or viruses. It is a leading cause of death from infectious diseases.
Key Point: Four types: Community-acquired (CAP), Health care–associated (HCAP), Hospital-acquired (HAP), Ventilator-associated (VAP).

Risk Factors
Risk factors vary by pathogen type and include age, alcohol use, immunosuppression, comorbidities, and recent antibiotic therapy.
Key Point: Residence in long-term care facilities and exposure to certain environments increase risk.

Clinical Manifestations
Symptoms depend on type and organism: chills, fever, pleuritic chest pain, tachypnea, respiratory distress, purulent or rusty sputum, central cyanosis, orthopnea, fatigue.
Key Point: Streptococcal pneumonia presents with sudden onset and high fever.
Assessment and Diagnostic Findings
Diagnosis is based on history, physical exam, chest x-ray, blood culture, and sputum examination. Invasive procedures may be needed for specimen collection in severe cases.
Key Point: Bronchoscopy is used for severe, chronic, or refractory infections.
Prevention
Vaccination (COVID-19, RSV, pneumococcal) is recommended for adults, especially those 65+ or immunocompromised. Preventive measures include following CDC guidelines and maintaining up-to-date vaccination status.
Key Point: Two types of pneumococcal vaccines: PCV15/PCV20 and PPSV23.
Medical Management
Treatment includes antibiotics for bacterial pneumonia, supportive care for viral pneumonia, hydration, oxygenation, and complication management.
Key Point: Antibiotic choice is based on culture, resistance patterns, and patient risk factors.
Other Therapeutic Regimens
Supportive care for viral pneumonia includes hydration, antipyretics, antitussives, warm moist inhalations, antihistamines, and nasal decongestants. Oxygen therapy is administered if hypoxemia develops.
Key Point: Hospitalized patients are observed until clinical improvement.
Gerontologic Considerations
Older adults may have atypical symptoms and higher mortality. Supportive treatment includes hydration, oxygen, deep breathing, coughing, position changes, and early ambulation.
Key Point: Vaccination reduces complications in older adults.
Complications
Severe complications include hypotension, septic shock, respiratory failure, atelectasis, pleural effusion, and delirium.
Key Point: Management of septic shock and respiratory failure is critical.
Pleural Effusion
Pleural effusion is the accumulation of fluid in the pleural space, often associated with pneumonia. Thoracentesis is performed for fluid removal and analysis.
Key Point: Empyema requires chest tube drainage and prolonged antibiotics.
Nursing Assessment and Diagnoses
Nursing assessment is critical for detecting pneumonia and complications. Major diagnoses include impaired airway clearance, fatigue, risk for hypovolemia, impaired nutrition, and lack of knowledge.
Key Point: Monitor for unusual behavior and altered mental status in older adults.
Collaborative Problems and Planning
Goals include improved airway patency, increased activity, proper fluid volume, adequate nutrition, understanding of treatment, and absence of complications.
Key Point: Education and adherence to treatment are essential.
Improving Airway Clearance
Hydration, humidification, effective coughing, chest physiotherapy, and oxygen therapy are used to remove secretions and improve gas exchange.
Key Point: CPT is indicated for sputum retention and abnormal breath sounds.
Promoting Rest, Fluid Intake, and Nutrition
Rest, increased fluid intake (2–3 L/day), and nutritional support are important for recovery. Small, frequent meals and oral supplements may be needed.
Key Point: Hydration must be monitored in patients with heart failure.
Promoting Knowledge and Self-Care
Patient education covers pneumonia cause, symptom management, signs to report, and follow-up. Encourage gradual activity increase, breathing exercises, smoking cessation, and vaccination.
Key Point: Written instructions and repetition improve understanding.
Continuing and Transitional Care
Severely debilitated patients may require home or community-based care. Home visits assess status, complications, and adherence.
Key Point: Influenza vaccination reduces susceptibility to secondary bacterial pneumonia.
Aspiration
Definition and Pathophysiology
Aspiration is the inhalation of foreign material into the lungs, leading to pneumonia. Key factors include the volume and character of aspirated contents.
Key Point: Common causative organisms: S. aureus, S. pneumoniae, H. influenzae, Enterobacter species.
Prevention and Clinical Practices
Prevention strategies include proper positioning, swallowing assessments, and monitoring. Clinical practices to prevent aspiration are summarized in Chart 19-6.
Key Point: Maintain head-of-bed elevation, confirm feeding tube placement, and monitor for delayed stomach emptying.

Acute Respiratory Failure
Definition and Pathophysiology
Acute respiratory failure is a sudden, life-threatening deterioration of gas exchange, defined by hypoxemia (PaO2 < 60 mm Hg) and hypercapnia (PaCO2 > 50 mm Hg with acidosis). Causes include CNS impairment, neuromuscular dysfunction, musculoskeletal dysfunction, and pulmonary diseases.
Key Point: V/Q mismatch is a common mechanism.
Clinical Manifestations
Early signs: restlessness, fatigue, headache, dyspnea, tachycardia, increased blood pressure. Progressive hypoxemia: confusion, lethargy, tachypnea, central cyanosis, respiratory arrest.
Key Point: Use of accessory muscles and decreased breath sounds are common findings.
Medical and Nursing Management
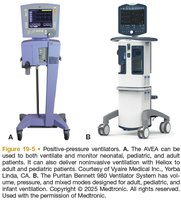
Management includes correcting the underlying cause, ET intubation, mechanical ventilation, and ICU care. Nursing care involves monitoring responsiveness, ABGs, pulse oximetry, vital signs, and preventing complications.
Key Point: Communication methods are important for intubated patients.
Endotracheal Intubation and Tracheostomy
Procedure and Indications
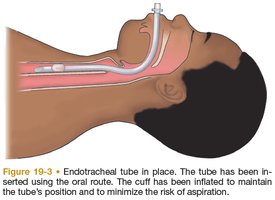
Endotracheal intubation involves passing a tube through the nose or mouth into the trachea to maintain airway and allow for mechanical ventilation. Tracheostomy is a surgical opening into the trachea for long-term airway management.
Key Point: Indications include respiratory distress, inability to maintain airway, and need for mechanical ventilation.
Complications and Care
Complications include cuff pressure issues, aspiration, infection, tracheal injury, and communication difficulties. Care involves continuous monitoring, suctioning, positioning, and education.
Key Point: Maintain cuff pressure between 20 and 25 mm Hg to prevent complications.
Acute Respiratory Distress Syndrome (ARDS)
Definition and Pathophysiology
ARDS is a severe inflammatory process causing diffuse alveolar damage, pulmonary edema, and hypoxemia unresponsive to oxygen. It is classified by severity based on PaO2/FiO2 ratio.
Key Point: Bilateral infiltrates on chest x-ray are characteristic.
Medical Management and Supportive Care
Management focuses on treating the underlying condition, aggressive supportive care (ET intubation, mechanical ventilation, PEEP), circulatory and nutritional support, and monitoring.
Key Point: Prone positioning may improve oxygenation in severe cases.
Chest Trauma
Blunt and Penetrating Trauma
Chest trauma can be blunt (compression or positive pressure) or penetrating (foreign object). Complications include pneumonia, DVT/PE, unplanned extubation, and ARDS.
Key Point: Blunt trauma is common in motor vehicle crashes and falls.
Pathophysiology and Assessment
Life-threatening injuries result in hypoxemia, hypovolemia, and cardiac failure. Assessment includes airway, breathing, chest movement, and diagnostic workup (x-ray, CT, CBC, ABG, ECG).
Key Point: Immediate assessment is critical for survival.
Sternal and Rib Fractures
Sternal fractures are common in motor vehicle crashes; rib fractures are the most frequent chest trauma. Pain, tenderness, and splinting lead to diminished ventilation and complications.
Key Point: Incentive spirometry prevents atelectasis.
Flail Chest and Pulmonary Contusion
Flail chest results from multiple rib fractures, causing paradoxical movement and respiratory impairment. Pulmonary contusion involves hemorrhage and edema, leading to gas exchange interference and hypoxemia.
Key Point: Severe cases require mechanical ventilation and aggressive management.
Pneumothorax
Definition and Types
Pneumothorax occurs when pleura is breached, exposing pleural space to positive pressure. Types: simple, traumatic, tension pneumothorax.
Key Point: Tension pneumothorax is a medical emergency.
Clinical Manifestations and Management
Symptoms: sudden pain, tachypnea, respiratory distress, tracheal shift. Management: chest tube insertion, suction, reestablish negative pressure, antibiotics.
Key Point: Chest tube placement is essential for lung reexpansion.

Collaborative Practice and Bundles
Ventilator-Associated Pneumonia Prevention
Evidence-based bundles include elevation of head of bed, daily sedation interruption, assessment of readiness to extubate, oral care, DVT prophylaxis, and daily review of antibiotic therapy.
Key Point: Bundles improve patient outcomes and reduce VAP incidence.

ABCDEF Bundle
The ABCDEF bundle addresses pain assessment, awakening and breathing coordination, delirium monitoring, early mobility, and family engagement.
Key Point: Early mobility and family engagement are crucial for recovery.
Summary Tables
Summary Table: Classifications of Pneumonia
Type | Definition |
|---|---|
CAP | Community-acquired, outside hospital or within 48 hours of admission |
HCAP | Health care–associated, recent health care contact |
HAP | Hospital-acquired, >48 hours after admission |
VAP | Ventilator-associated, >48 hours after intubation |
Summary Table: Risk Factors for Pneumonia Pathogens
Pathogen | Risk Factors |
|---|---|
Penicillin-resistant pneumococci | Age >65, alcohol use, immunosuppression, recent antibiotics |
Enteric Gram-negative bacteria | Long-term care, comorbidities, recent antibiotics |
Pseudomonas aeruginosa | Structural lung disease, malnutrition, recent antibiotics |
Summary Table: Clinical Practices to Prevent Aspiration
Practice | Description |
|---|---|
Head-of-bed elevation | 30–45 degrees unless contraindicated |
Sedatives | Use sparingly |
Tube feeding | Confirm placement, assess residuals |
Swallowing evaluation | For at-risk patients |
ET cuff pressure | Maintain >20 cm H2O |
Summary Table: Indications for Mechanical Ventilation
Laboratory Value | Clinical Manifestation |
|---|---|
PaO2 <55 mm Hg | Apnea or bradypnea |
PaCO2 >50 mm Hg and pH <7.32 | Respiratory distress with confusion |
Vital capacity <10 mL/kg | Increased work of breathing |
Negative inspiratory force <25 cm H2O | Confusion with need for airway protection |
FEV1 <10 mL/kg | Circulatory shock |
Key Equations
Arterial Blood Gas Criteria for Acute Respiratory Failure
Hypoxemia:
Hypercapnia:
Acidosis:
ARDS Severity Classification
Mild ARDS:
Moderate ARDS:
Severe ARDS:
Conclusion
This guide summarizes acute disorders of the chest and lower respiratory tract, including atelectasis, tracheobronchitis, pneumonia, aspiration, respiratory failure, ARDS, chest trauma, and pneumothorax. Prevention, assessment, management, and collaborative practices are emphasized for optimal patient outcomes.
References
CDC Vaccination Guidelines
American Association of Critical-Care Nurses
Ramirez, 2023
Kompas et al., 2022
Amital, 2020
