 Back
Bones and Skeletal Tissues: Structure, Function, and Development
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Chapter 6: Bones and Skeletal Tissues
6.1 Skeletal Cartilages
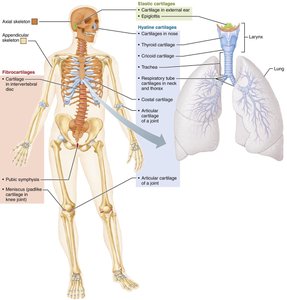
The human skeleton initially consists of cartilage, which is gradually replaced by bone except in areas requiring flexibility. Skeletal cartilage is a resilient tissue composed mainly of water, providing flexibility and cushioning. It is avascular and lacks nerves, with chondrocytes (cartilage cells) residing in lacunae within a jelly-like matrix.
Hyaline cartilage: Provides support, flexibility, and resilience; most abundant; found in articular surfaces, costal cartilage, respiratory structures, and nasal cartilage.
Elastic cartilage: Contains elastic fibers; found in the external ear and epiglottis.
Fibrocartilage: Contains thick collagen fibers; provides tensile strength; found in menisci of the knee and intervertebral discs.
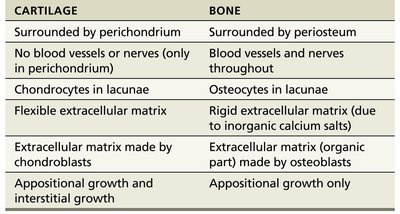
Comparison of Cartilage and Bone
CARTILAGE | BONE |
|---|---|
Surrounded by perichondrium | Surrounded by periosteum |
No blood vessels or nerves (only in perichondrium) | Blood vessels and nerves throughout |
Chondrocytes in lacunae | Osteocytes in lacunae |
Flexible extracellular matrix | Rigid extracellular matrix (due to inorganic calcium salts) |
Extracellular matrix made by chondroblasts | Extracellular matrix (organic part) made by osteoblasts |
Appositional growth and interstitial growth | Appositional growth only |
Growth of Cartilage
Appositional growth: New matrix is secreted on the surface by cells in the perichondrium, increasing width.
Interstitial growth: Chondrocytes divide and secrete new matrix from within, increasing length.
Cartilage growth is essential for normal bone development and continues until early adulthood.
6.2 Functions of Bones
Bones perform several critical functions in the body:
Support: Framework for the body and soft organs.
Protection: Shields the brain, spinal cord, and vital organs.
Movement: Acts as levers for muscle action.
Mineral and growth factor storage: Reservoir for calcium, phosphorus, and growth factors.
Blood cell formation: Hematopoiesis occurs in red marrow cavities.
Triglyceride (fat) storage: Stored in yellow marrow for energy.
Hormone production: Osteocalcin regulates insulin secretion, glucose levels, and metabolism.
Anchorage: Provides attachment points for muscles, enabling movement.
6.3 Classification of Bones
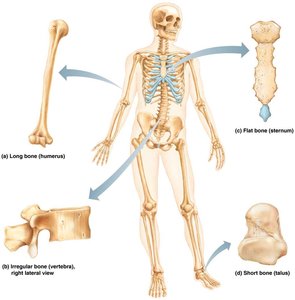
Bones are classified by shape into four main categories:
Long bones: Longer than wide (e.g., humerus, femur).
Short bones: Cube-shaped (e.g., carpals, tarsals); includes sesamoid bones like the patella.
Flat bones: Thin, flat, and slightly curved (e.g., sternum, ribs, skull bones).
Irregular bones: Complicated shapes (e.g., vertebrae, hip bones).
6.4 Bone Structure
Bones are organs composed of several tissue types. They have three levels of structure: gross, microscopic, and chemical.
Gross Anatomy
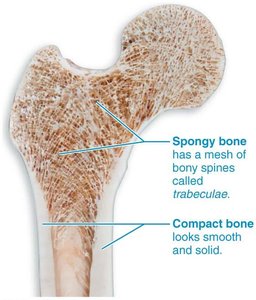
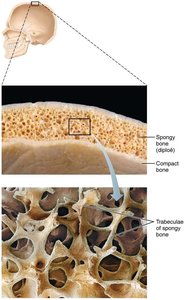
Compact bone: Dense outer layer that appears smooth and solid.
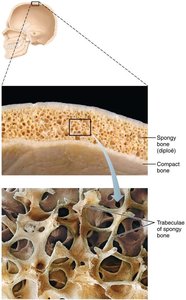
Spongy bone: Internal honeycomb of trabeculae filled with marrow.
Structure of Short, Irregular, and Flat Bones
Thin plates of spongy bone (diploë) covered by compact bone.
Periosteum covers the outside; endosteum covers the inside.
No defined marrow cavity; marrow is scattered throughout spongy bone.
Hyaline cartilage covers joint surfaces.
Structure of a Typical Long Bone
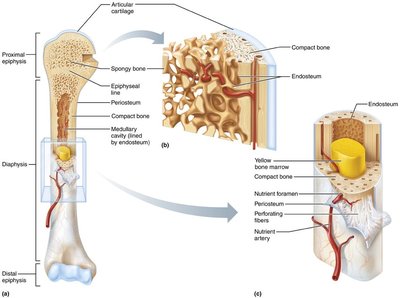
Diaphysis: Shaft; compact bone surrounding the medullary cavity (yellow marrow in adults).
Epiphyses: Bone ends; compact bone externally, spongy bone internally; articular cartilage covers joint surfaces.
Epiphyseal line: Remnant of the growth plate in adults.
Membranes: Periosteum (outer) and endosteum (inner) cover bone surfaces.
Bone Markings
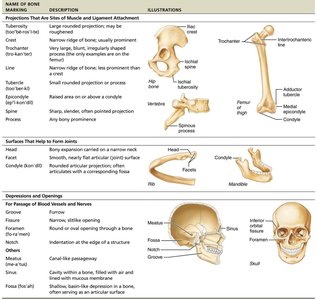
Bone markings are features on bones that serve as sites for muscle, ligament, and tendon attachment, or as passages for nerves and blood vessels. They are classified as projections, depressions, or openings.
Microscopic Anatomy of Bone
Bone Cells
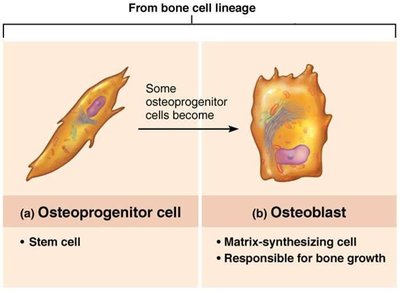
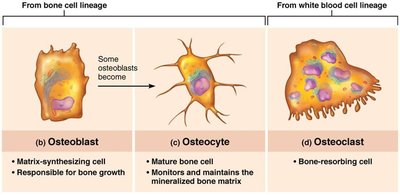
Osteogenic cells: Stem cells in periosteum and endosteum; differentiate into osteoblasts or bone-lining cells.
Osteoblasts: Bone-forming cells; secrete osteoid (collagen and calcium-binding proteins).
Osteocytes: Mature bone cells in lacunae; maintain bone matrix and act as stress sensors.
Osteoclasts: Bone-resorbing cells derived from hematopoietic stem cells; break down bone matrix.
Compact Bone (Lamellar Bone)
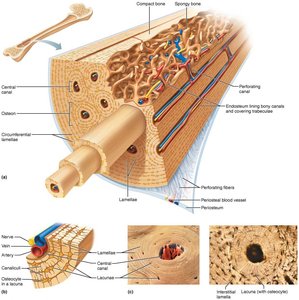
Osteon (Haversian system): Structural unit; elongated cylinders with concentric lamellae.
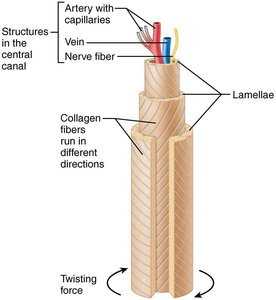
Lamellae: Collagen fibers run in alternating directions to resist twisting.
Central (Haversian) canal: Contains blood vessels and nerves.
Perforating (Volkmann's) canals: Connect blood supply of periosteum to central canal.
Lacunae: Small cavities with osteocytes.
Canaliculi: Tiny canals connecting lacunae for nutrient and waste exchange.
Spongy Bone
Composed of trabeculae aligned along lines of stress.
No osteons; contains irregularly arranged lamellae and osteocytes connected by canaliculi.
Capillaries in endosteum supply nutrients.
Chemical Composition of Bone
Organic components: Cells (osteogenic, osteoblasts, osteocytes, osteoclasts) and osteoid (collagen, ground substance).
Inorganic components: Hydroxyapatites (mineral salts, mainly calcium phosphate) provide hardness and resistance to compression.
6.5 Bone Development (Ossification)
Ossification (osteogenesis) is the process of bone tissue formation. It occurs in two main forms:
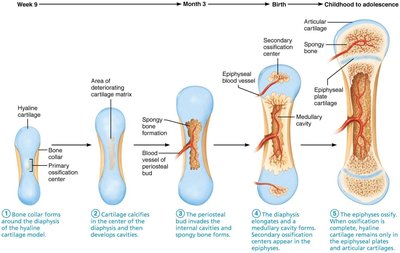
Endochondral ossification: Bone forms by replacing hyaline cartilage; forms most of the skeleton below the skull (except clavicles).
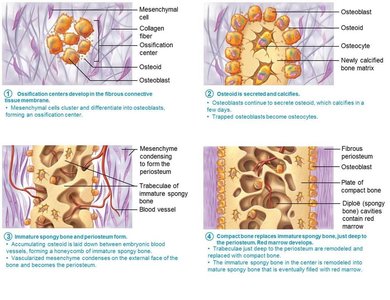
Intramembranous ossification: Bone develops from fibrous membranes; forms flat bones (e.g., skull, clavicles).
Postnatal Bone Growth
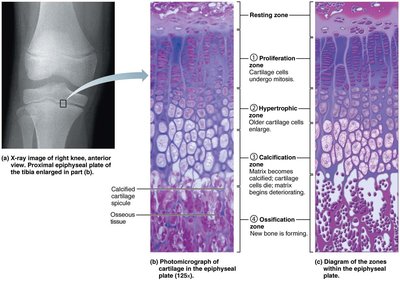
Interstitial growth: Lengthening of long bones at the epiphyseal plate.
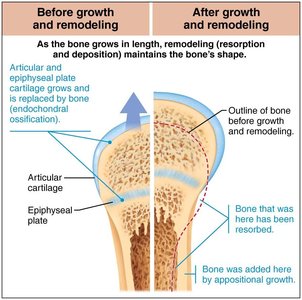
Appositional growth: Increase in bone thickness throughout life.
Epiphyseal plate closure marks the end of longitudinal growth (around age 18 in females, 21 in males).
Hormonal Regulation of Bone Growth
Growth hormone: Stimulates epiphyseal plate activity.
Thyroid hormone: Modulates growth hormone effects.
Sex hormones: Promote growth spurts and induce epiphyseal plate closure.
6.6 Bone Remodeling
Bone remodeling is a continuous process involving bone deposit (by osteoblasts) and bone resorption (by osteoclasts). About 5–7% of bone mass is recycled weekly.
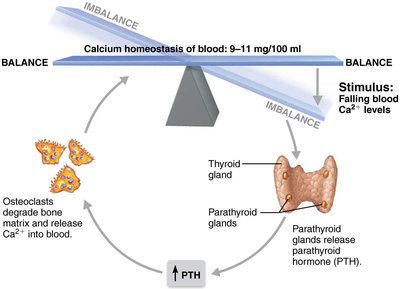
Hormonal controls: Parathyroid hormone (PTH) stimulates osteoclasts to release calcium into the blood when levels are low; calcitonin (from the thyroid) can lower blood calcium at high doses.
Mechanical stress: Bones adapt to the loads placed on them, becoming thicker and stronger with use.
6.7 Bone Repair
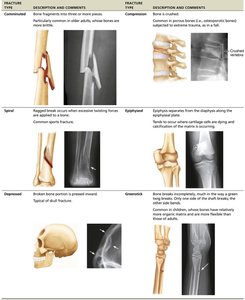
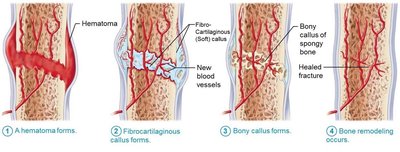
Bone fractures are classified by position, completeness, and whether the skin is penetrated. Healing involves several stages:
Hematoma formation: Blood clot forms at the fracture site.
Fibrocartilaginous callus formation: Collagen fibers and cartilage bridge the break.
Bony callus formation: Spongy bone replaces the callus.
Bone remodeling: Compact bone restores the shaft's original shape.
Bone Disorders
Osteomalacia and Rickets
Osteomalacia: Poorly mineralized bones in adults; bones are soft and weak due to inadequate calcium deposition.
Rickets: Osteomalacia in children; causes bone deformities, usually due to vitamin D deficiency or insufficient calcium.
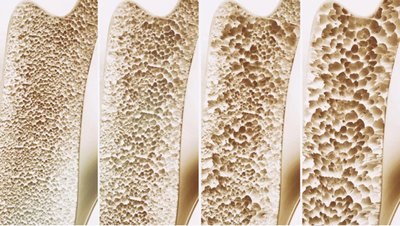
Osteoporosis
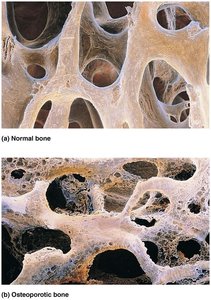
Bone resorption exceeds deposit; bone mass declines but matrix remains normal.
Common in postmenopausal women; risk factors include age, low calcium/protein intake, inactivity, and genetics.
Treatment includes calcium, vitamin D, exercise, and hormone therapy.
Paget's Disease
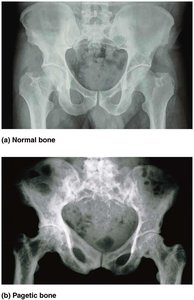
Excessive and disorganized bone remodeling; high ratio of spongy to compact bone.
Commonly affects the spine, pelvis, femur, and skull; cause is unclear.
Treatment includes calcitonin and bisphosphonates.
Developmental Aspects of Bone
Embryonic skeleton ossifies predictably; fetal age can be determined by ossification centers.
Most long bones begin ossifying by 8 weeks; primary ossification centers by week 12.
At birth, most long bones are ossified except at epiphyses; epiphyseal plates persist through adolescence.
Bone mass peaks in young adulthood and declines with age, especially in females and those with genetic risk factors.
