 Back
Chapter 17: Blood – Anatomy & Physiology Study Guide
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Blood: Structure, Function, and Clinical Significance
Functions of Blood
Blood is a vital connective tissue that serves as the internal transport system of the body. Its functions are categorized into transport, regulation, and protection.
Transport: Delivers oxygen and nutrients to cells, removes metabolic wastes, and transports hormones.
Regulation: Maintains body temperature, pH balance (using buffers and bicarbonate ions), and fluid volume.
Protection: Prevents blood loss (via clotting) and infection (via immune agents such as antibodies, complement proteins, and white blood cells).
Components of Blood
Blood consists of plasma (the liquid matrix) and formed elements (cells and cell fragments). The formed elements include erythrocytes (red blood cells), leukocytes (white blood cells), and platelets.
Plasma: Straw-colored fluid containing water, proteins (albumin, globulins, fibrinogen), nutrients, gases, hormones, and wastes.
Formed Elements: Erythrocytes (RBCs), leukocytes (WBCs), and platelets.

Physical Characteristics and Volume
Blood is a viscous, opaque fluid with a metallic taste. Its color varies with oxygen content: bright red when oxygen-rich, dark red when oxygen-poor. Blood pH is tightly regulated between 7.35–7.45. Average volume is 5–6 L in males and 4–5 L in females.
Blood Plasma
Plasma is the fluid portion of blood, making up about 55% of total blood volume. It contains over 100 dissolved solutes, including nutrients, gases, hormones, wastes, proteins, and inorganic ions. Plasma proteins, mainly produced by the liver, are the most abundant solutes.
Albumin: Most abundant plasma protein; functions as a blood buffer, carrier, and contributor to osmotic pressure.
Formed Elements
The formed elements have unique features: erythrocytes and platelets are not true cells (RBCs lack nuclei and most organelles; platelets are cell fragments). Most formed elements survive only a few days and are replaced by stem cells in red bone marrow.
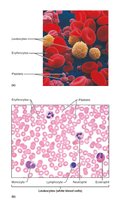
Erythrocytes (Red Blood Cells)
Structural Characteristics
Erythrocytes are small, biconcave, anucleate cells specialized for gas transport. Their shape provides a large surface area to volume ratio, facilitating efficient gas exchange. They are filled with hemoglobin and lack mitochondria, so they do not consume the oxygen they transport.
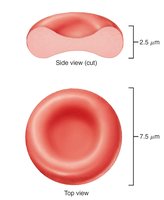
Functions of Erythrocytes
RBCs are dedicated to respiratory gas transport. Hemoglobin binds reversibly with oxygen and carbon dioxide. Each hemoglobin molecule consists of four globin chains and four heme groups, each with a central iron ion that binds one oxygen molecule.
Oxyhemoglobin: Hemoglobin bound to oxygen (bright red).
Deoxyhemoglobin: Hemoglobin after oxygen is released (dark red).
Carbaminohemoglobin: Hemoglobin bound to carbon dioxide.
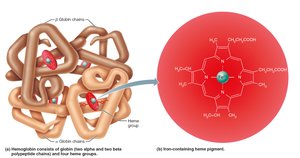
Production of Erythrocytes (Erythropoiesis)
Erythropoiesis occurs in red bone marrow and involves several stages, from hematopoietic stem cells to mature erythrocytes. Reticulocyte counts estimate the rate of RBC formation.
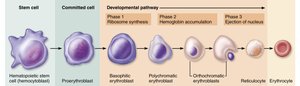
Regulation of Erythropoiesis
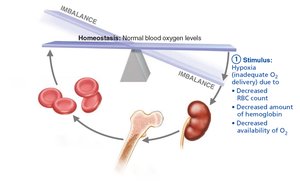
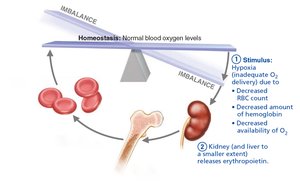
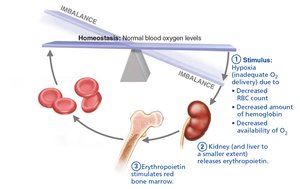
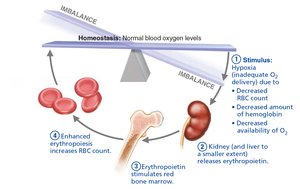
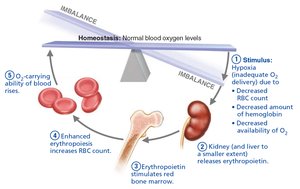
Erythropoiesis is regulated by erythropoietin (EPO), a hormone released by the kidneys in response to hypoxia. Dietary requirements include amino acids, lipids, carbohydrates, vitamin B12, folic acid, and iron.
Iron: Essential for hemoglobin synthesis; stored as ferritin and hemosiderin, transported by transferrin.
Fate and Destruction of Erythrocytes
RBCs have a lifespan of 100–120 days. Old RBCs are destroyed by macrophages in the spleen. Hemoglobin is broken down: iron is stored for reuse, heme is converted to bilirubin (excreted in bile), and globin is metabolized to amino acids.




Erythrocyte Disorders
Disorders include anemia (low oxygen-carrying capacity) and polycythemia (excess RBCs).
Anemia: Caused by blood loss, insufficient RBC production, or excessive RBC destruction. Types include iron-deficiency, pernicious, renal, aplastic, hemolytic, thalassemia, and sickle-cell anemia.
Sickle-cell anemia: Genetic disorder causing abnormal hemoglobin and sickled RBCs, leading to blockages and pain.
Polycythemia: Abnormal excess of RBCs, increasing blood viscosity.

Leukocytes (White Blood Cells)
General Structure and Function
Leukocytes are complete cells with nuclei and organelles. They defend the body against infection and disease, moving through tissues by diapedesis and chemotaxis.
Leukocytosis: Elevated WBC count, normal response to infection.
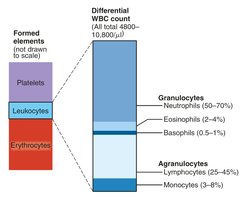
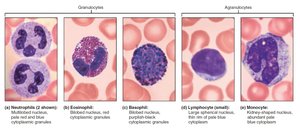
Classification: Granulocytes (neutrophils, eosinophils, basophils) and agranulocytes (lymphocytes, monocytes).
Granulocytes
Granulocytes have visible cytoplasmic granules and lobed nuclei.
Neutrophils: Most numerous, phagocytic, kill bacteria.
Eosinophils: Destroy parasitic worms, modulate immune response.
Basophils: Release histamine, involved in inflammation.
Agranulocytes
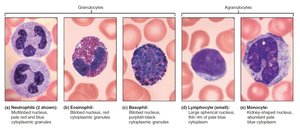
Agranulocytes lack visible granules and have spherical or kidney-shaped nuclei.
Lymphocytes: Second most numerous, crucial for immunity (T cells and B cells).
Monocytes: Largest WBCs, become macrophages, active in phagocytosis.
Leukocyte Formation
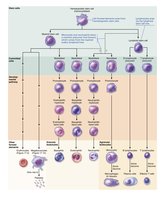
Leukopoiesis is stimulated by interleukins and colony-stimulating factors. Hematopoietic stem cells differentiate into myeloid or lymphoid lines, producing various WBCs.
Leukocyte Disorders
Disorders include leukemias (cancerous overproduction of abnormal WBCs), leukopenia (low WBC count), and infectious mononucleosis (viral disease causing excess atypical lymphocytes).
Platelets
Structure and Function
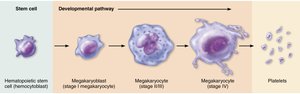
Platelets are cell fragments from megakaryocytes, essential for blood clotting. They form temporary plugs to seal vessel breaks and contain chemicals for clotting.
Hemostasis
Overview
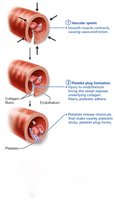
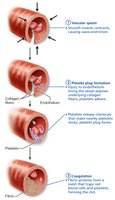
Hemostasis is the process that stops bleeding, involving three steps: vascular spasm, platelet plug formation, and coagulation.
Vascular spasm: Vasoconstriction reduces blood loss.
Platelet plug formation: Platelets adhere to exposed collagen, become activated, and aggregate.
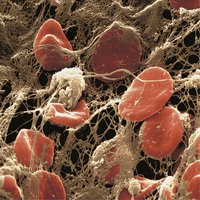
Coagulation: Reinforces plug with fibrin mesh.

Coagulation Pathways
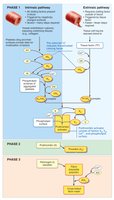
Coagulation involves intrinsic and extrinsic pathways leading to the formation of prothrombin activator, which converts prothrombin to thrombin. Thrombin then converts fibrinogen to fibrin, forming the clot.
Intrinsic pathway: Triggered by factors within blood.
Extrinsic pathway: Triggered by tissue factor outside blood.
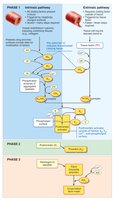
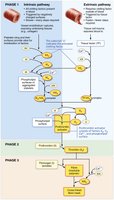
Clot Retraction and Fibrinolysis
Clot retraction stabilizes the clot, and fibrinolysis removes the clot after repair. Plasminogen is converted to plasmin, which digests fibrin.
Disorders of Hemostasis
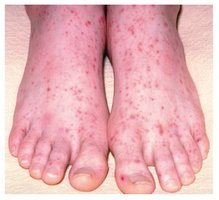
Thromboembolic disorders (undesirable clot formation) and bleeding disorders (impaired clotting) are major types. Examples include thrombocytopenia, hemophilia, and disseminated intravascular coagulation (DIC).
Blood Transfusion and Blood Typing
Blood Groups
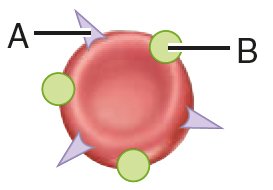
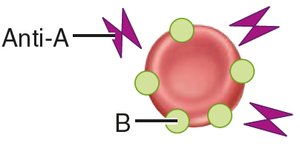
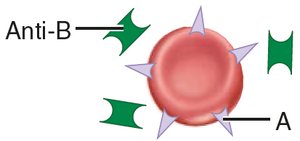
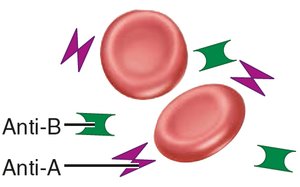
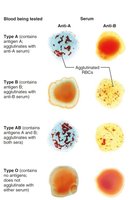
Blood groups are determined by antigens on RBC membranes. The ABO and Rh groups are most clinically significant.
ABO: Type A (A antigen), Type B (B antigen), Type AB (both), Type O (neither).
Rh: Presence or absence of D antigen.
Transfusion Reactions
Transfusion reactions occur if mismatched blood is infused, leading to agglutination and hemolysis of donor RBCs. Group O is considered the universal donor, and group AB the universal recipient, but other antigens can cause reactions.
Blood Tests and Clinical Insights
Blood tests provide information about health, including hematocrit, blood glucose, differential WBC count, prothrombin time, and complete blood count (CBC).
Developmental Aspects of Blood
Fetal blood cells form in the yolk sac, liver, and spleen. Red bone marrow becomes the primary hematopoietic area by the seventh month. Hemoglobin F in the fetus has a higher affinity for oxygen than adult hemoglobin.
