 Indietro
Bones and Skeletal Tissues: Structure, Function, and Development
Guida di studio - Note intelligenti
 Appunti personalizzati basati sui tuoi materiali, ampliati con definizioni chiave, esempi e contesto.
Chapter 7: Bones and Skeletal Tissues
Skeletal Cartilage
Skeletal cartilage is a resilient tissue that forms much of the embryonic skeleton and persists in adult joints. It is avascular and lacks nerves, relying on diffusion for nutrient supply.
Composition: Primarily water, surrounded by the perichondrium (dense connective tissue containing blood vessels).
Types of Cartilage:
Hyaline cartilage: Most abundant; provides support, flexibility, and resilience. Found in articular, costal, respiratory, and nasal cartilages.
Elastic cartilage: Similar to hyaline but with more elastic fibers; found in external ear and epiglottis.
Fibrocartilage: Highly compressible, contains collagen fibers; found in menisci, pubic symphysis, and intervertebral discs.
Classification of Bones
The human skeleton consists of 206 named bones, divided into axial and appendicular skeletons. Bones are classified by shape and function.
Axial skeleton: Skull, vertebral column, rib cage.
Appendicular skeleton: Limbs, shoulder, hip.
Bone shapes:
Long bones: Longer than wide (e.g., humerus).
Short bones: Cube-shaped (e.g., wrist, ankle).
Flat bones: Thin, flattened, curved (e.g., sternum, skull).
Irregular bones: Complex shapes (e.g., vertebrae, pelvis).
Sesamoid bones: Small, round, in tendons (e.g., patella).
Functions of Bones
Bones serve multiple essential functions in the body.
Support: Framework for the body and soft organs.
Protection: Shields brain, spinal cord, and vital organs.
Movement: Acts as levers for muscle action.
Storage: Stores minerals (calcium, phosphate), growth factors, and fat (triglycerides).
Blood cell formation: Hematopoiesis occurs in red bone marrow.
Bone Markings
Bone markings are structural features that serve as sites for muscle, ligament, and tendon attachment, joint surfaces, and conduits for blood vessels and nerves.
Bulges, depressions, holes: Facilitate attachment and passage.
Foramen: Openings for vessels and nerves.
Bone Textures
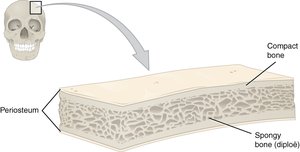
Bones have two main textures: compact and spongy.
Compact bone: Dense outer layer providing strength.
Spongy bone: Honeycomb structure of trabeculae, filled with marrow.
Gross Anatomy of Bone
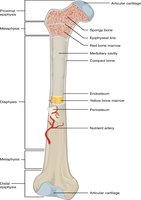
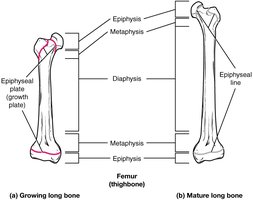
Long bones have a distinct anatomy, including diaphysis, epiphysis, and specialized membranes.
Diaphysis: Shaft, contains medullary cavity (yellow marrow in adults, red in infants).
Epiphysis: Ends of bone, filled with spongy bone and red marrow.
Epiphyseal plate: Growth plate of hyaline cartilage; becomes epiphyseal line after growth.
Endosteum: Membrane lining internal surfaces, contains osteoblasts and osteoclasts.
Periosteum: Covers outer surface, contains vessels, nerves, and Sharpey’s fibers.
Articular cartilage: Hyaline cartilage at epiphyses, reduces friction.
Microscopic Structure of Bone: Compact Bone
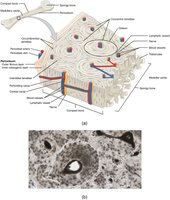
Compact bone is organized into osteons (Haversian systems), which are the functional units.
Osteon: Cylindrical structure with concentric lamellae.
Lamella: Collagen matrix tubes for weight-bearing.
Haversian canal: Central channel for vessels and nerves.
Volkmann’s canals: Perforating canals connecting periosteum and Haversian canal.
Osteocytes: Mature bone cells in lacunae.
Canaliculi: Tiny canals connecting lacunae and central canal.
Microscopic Anatomy of Bone: Spongy Bone
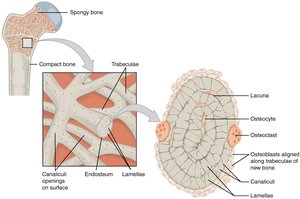
Spongy bone consists of trabeculae aligned along lines of stress, containing lamellae, osteocytes, and canaliculi.
Trabeculae: Irregular latticework, no osteons.
Marrow: Red or yellow, fills spaces between trabeculae.
Capillaries: Supply nutrients via endosteum.
Location of Hematopoietic Tissue (Red Marrow)
Red marrow is the site of blood cell formation and its location changes with age.
Infants: Medullary cavity and all spongy bone.
Adults: Spongy bone of flat bones, heads of femur and humerus.
Yellow marrow: Can revert to red marrow in anemia.
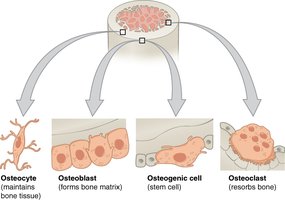
Types of Bone Cells
Bone tissue contains four main cell types, each with distinct functions.
Osteocytes: Mature bone cells, maintain bone tissue.
Osteoblasts: Bone-forming cells, synthesize matrix.
Osteoclasts: Large, multinucleated cells that resorb bone.
Osteogenic cells: Stem cells in periosteum and endosteum, differentiate into osteoblasts.
Chemical Composition of Bone
Bones are composed of organic and inorganic components.
Organic: Collagen fibers, cells (osteocytes, osteoblasts, osteoclasts).
Inorganic: Hydroxyapatites (calcium phosphates), magnesium; responsible for hardness and resistance to compression.
Bone Development (Osteogenesis/Ossification)
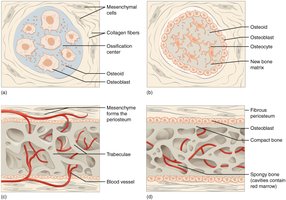
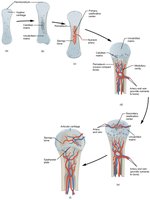
Bone formation occurs in three stages: initial formation, postnatal growth, and lifelong remodeling.
Intramembranous ossification: Bone develops from fibrous membranes; forms cranial bones and clavicles.
Endochondral ossification: Bone forms by replacing hyaline cartilage; forms most of the skeleton.
Long Bone Growth and Remodeling
Long bones grow in length and thickness through interstitial and appositional growth.
Interstitial growth: Cartilage grows and is replaced by bone, increasing length.
Appositional growth: Osteoblasts and osteoclasts remodel bone surfaces, increasing thickness.
Hormonal Regulation of Bone Growth
Bone growth is regulated by hormones, especially during childhood and adolescence.
Growth hormone: Stimulates epiphyseal plate activity.
Thyroid hormone: Modulates growth hormone activity. Sex hormones: Promote growth spurts and induce epiphyseal plate closure.
Bone Deposition and Resorption
Bone is continuously deposited and resorbed to maintain strength and mineral homeostasis.
Deposition: Osteoblasts build bone; requires protein, vitamins, and minerals.
Resorption: Osteoclasts break down bone matrix using lysosomal enzymes.
Control of Bone Remodeling
Bone remodeling is controlled by hormonal and mechanical factors.
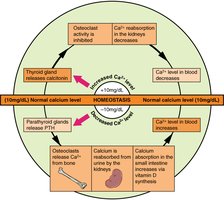
Hormonal mechanism: Maintains blood calcium homeostasis.
Mechanical forces: Wolff’s law states bone adapts to stress.
Hormonal Control of Blood Calcium (Ca2+)
Blood calcium levels are tightly regulated by hormones.
Low Ca2+: Parathyroid hormone (PTH) stimulates osteoclasts to release calcium from bone.
High Ca2+: Calcitonin from thyroid stimulates osteoblasts to deposit calcium in bone.
Response to Mechanical Stress
Bone adapts to mechanical stress according to Wolff’s law.
Handedness: Dominant limb bones are thicker.
Curved bones: Thickest where most likely to buckle.
Trabeculae: Align along lines of stress.
Projections: Occur where muscles attach.
Bone Fractures
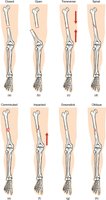
Fractures are classified by position, completeness, orientation, and skin penetration.
Nondisplaced: Ends retain normal position.
Displaced: Ends out of alignment.
Complete: Broken all the way through.
Incomplete: Not broken all the way through.
Linear: Parallel to long axis.
Common Types of Fractures
Several fracture types are commonly observed in clinical practice.
Transverse: Perpendicular to long axis.
Compound (open): Bone penetrates skin.
Simple (closed): Bone does not penetrate skin.
Comminuted: Bone fragments into pieces.
Spiral: Ragged break from twisting.
Depressed: Bone pressed inward (skull).
Compression: Bone crushed (spine).
Greenstick: Incomplete break (children).
Bone Fracture Healing Stages
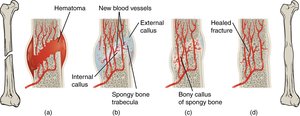
Bone healing occurs in four stages:
Hematoma formation: Blood clot forms at fracture site.
Fibrocartilaginous callus formation: New blood vessels and soft callus form.
Bony callus formation: Spongy bone replaces callus.
Bone remodeling: Compact bone replaces spongy bone, restoring shape.
Homeostatic Imbalances
Several disorders affect bone health and homeostasis.
Osteomalacia (Rickets): Inadequate mineralization, soft bones, pain, deformities; caused by calcium or vitamin D deficiency.
Osteoporosis: Loss of bone mass, increased fracture risk; risk factors include age, hormone deficiency, immobility, diabetes.
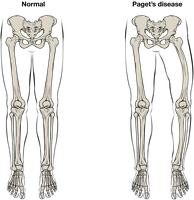
Paget’s Disease: Excessive bone formation and breakdown, high ratio of spongy to compact bone, spotty weakening; cause unknown.
Developmental Aspects of Bones
Bone development begins in the embryo and continues through early adulthood.
Mesoderm: Gives rise to mesenchymal cells, forming embryonic skeleton.
Ossification: Predictable timetable allows fetal age estimation.
At birth: Most long bones ossified except epiphyses.
By age 25: Nearly all bones completely ossified.
Bone mass: Decreases with age, resorption predominates in old age.
Bone Cell Type | Function |
|---|---|
Osteocyte | Maintains bone tissue |
Osteoblast | Forms bone matrix |
Osteogenic cell | Stem cell for bone |
Osteoclast | Resorbs bone |
Type of Fracture | Description |
|---|---|
Transverse | Perpendicular to long axis |
Compound (open) | Bone penetrates skin |
Simple (closed) | Bone does not penetrate skin |
Comminuted | Bone fragments into pieces |
Spiral | Ragged break from twisting |
Depressed | Bone pressed inward |
Compression | Bone crushed |
Greenstick | Incomplete break |
Example: Osteoporosis is common in elderly individuals, especially postmenopausal women, due to decreased estrogen levels, leading to increased fracture risk in the spine and femur.
Additional info: Bone remodeling is a dynamic process influenced by both systemic hormones and local mechanical forces, ensuring bones adapt to changing demands and maintain mineral homeostasis.
