 Back
Bones and Skeletal Tissues: Medical Terminology Study Guide
Study Guide - Smart Notes
 Tailored notes based on your materials, expanded with key definitions, examples, and context.
Bones and Skeletal Tissues
Introduction
The skeletal system is fundamental to human anatomy and physiology, providing structure, protection, and facilitating movement. Understanding bone anatomy, development, and disorders is essential for medical terminology students.
Skeletal Cartilages
Basic Structure and Types
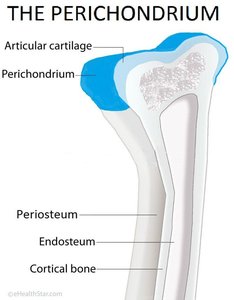
Skeletal cartilage is a resilient, molded tissue primarily composed of water. It contains no blood vessels or nerves and is surrounded by the perichondrium, a dense connective tissue layer that supplies nutrients and resists expansion.
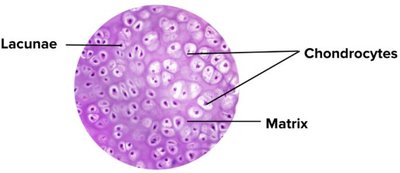
Chondrocytes: Cells encased in lacunae within the extracellular matrix.
Perichondrium: Surrounds cartilage, contains blood vessels for nutrient delivery.
Types of Cartilage
Hyaline cartilage: Provides support, flexibility, and resilience; most abundant; found in joints, ribs, respiratory structures, and nose.
Elastic cartilage: Similar to hyaline but contains elastic fibers; found in external ear and epiglottis.
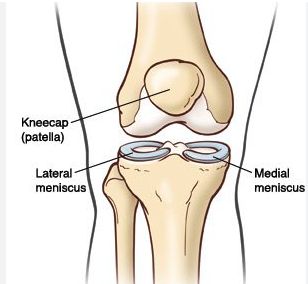
Fibrocartilage: Thick collagen fibers, great tensile strength; found in menisci of knee, vertebral discs, and pubic symphysis.


Growth of Cartilage
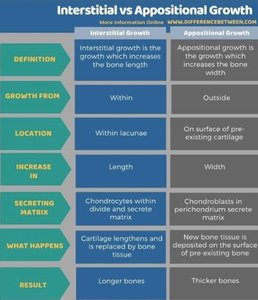
Appositional growth: Chondroblasts in perichondrium secrete matrix on surface, increasing width.
Interstitial growth: Chondrocytes divide within lacunae, expanding cartilage from within, increasing length.

Calcification of cartilage occurs during normal bone growth in youth and can occur in old age, but hardened cartilage is not bone.
Functions of Bones
Seven Key Functions
Support: Provides framework for the body and soft organs.
Protection: Shields brain, spinal cord, and vital organs.
Movement: Acts as levers for muscle action.
Mineral and growth factor storage: Reservoir for calcium, phosphorus, and growth factors.
Blood cell formation: Hematopoiesis in red marrow cavities.
Triglyceride storage: Fat stored in bone cavities (yellow marrow).
Hormone production: Osteocalcin regulates insulin, glucose, and metabolism.
Classification of Bones
Axial vs. Appendicular Skeleton
The human skeleton has 206 named bones, divided into:
Axial skeleton: Skull, vertebral column, rib cage (long axis of body).
Appendicular skeleton: Bones of limbs and girdles attaching limbs to axial skeleton.

Bone Shapes
Long bones: Longer than wide; limb bones, fingers.
Short bones: Cube-shaped; wrist, ankle, sesamoid bones (patella).
Flat bones: Thin, flat, slightly curved; sternum, scapulae, ribs, skull.
Irregular bones: Complicated shapes; vertebrae, hip bones.


Bone Structure
Gross Anatomy
Compact bone: Dense outer layer, smooth and solid.
Spongy bone: Honeycomb of trabeculae, filled with red or yellow marrow.

Structure of Long Bones
Diaphysis: Shaft, compact bone surrounding medullary cavity (yellow marrow).
Epiphyses: Ends, compact bone externally, spongy bone internally; articular cartilage covers joint surfaces.
Epiphyseal line: Remnant of epiphyseal plate (site of bone growth).

Membranes
Periosteum: Double-layered membrane covering external surfaces except joints; contains nerve fibers, blood vessels, and osteogenic cells.
Endosteum: Delicate membrane covering internal bone surfaces, trabeculae, and canals; contains osteogenic cells.
Hematopoietic Tissue
Red marrow: Found in trabecular cavities of spongy bone and diploë of flat bones; site of blood cell formation.
Yellow marrow: Can convert to red marrow if needed.
Bone Markings
Bone markings are sites for muscle, ligament, and tendon attachment, joint formation, and passageways for blood vessels and nerves.
Type | Description |
|---|---|
Projection | Outward bulge, often for muscle attachment or joint formation (e.g., tuberosity, crest, trochanter, condyle, spine, process, facet, head). |
Depression | Bowl- or groove-like cut-out, passageways for vessels/nerves or joint role (e.g., groove, fossa, notch). |
Opening | Hole or canal for passageways (e.g., foramen, meatus, sinus). |
Microscopic Anatomy of Bone
Bone Cells
Osteogenic cells: Stem cells in periosteum and endosteum; differentiate into osteoblasts.
Osteoblasts: Bone-forming cells; secrete osteoid (collagen and calcium-binding proteins).
Osteocytes: Mature bone cells in lacunae; maintain matrix and act as stress sensors.
Bone-lining cells: Maintain matrix; periosteal (external) and endosteal (internal).
Osteoclasts: Multinucleate cells for bone resorption; derived from hematopoietic stem cells.
Compact Bone Structure
Osteon (Haversian system): Structural unit; elongated cylinder with concentric lamellae.
Lamellae: Collagen fibers in different directions; resist stress and twisting.
Canals: Central (Haversian) canal (blood vessels, nerves); Perforating (Volkmann's) canals (connect periosteum, medullary cavity, central canal).
Lacunae: Small cavities with osteocytes.
Canaliculi: Hairlike canals connecting lacunae and central canal; allow communication and nutrient/waste relay.
Interstitial lamellae: Fill gaps between osteons.
Circumferential lamellae: Extend around diaphysis; resist twisting.
Spongy Bone Structure
Trabeculae aligned along lines of stress; confer strength.
No osteons; irregular lamellae and osteocytes interconnected by canaliculi.
Capillaries in endosteum supply nutrients.
Chemical Composition of Bone
Organic Components
Cells: Osteogenic, osteoblasts, osteocytes, bone-lining, osteoclasts.
Osteoid: Ground substance and collagen fibers; tensile strength and flexibility.
Sacrificial bonds in collagen molecules dissipate energy and prevent fractures.
Inorganic Components
Hydroxyapatites (mineral salts): 65% of bone mass; calcium phosphate crystals.
Responsible for hardness and resistance to compression.
Bone Development (Ossification)
Ossification Processes
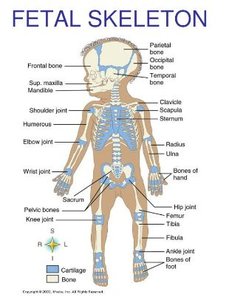
Endochondral ossification: Bone forms by replacing hyaline cartilage; most bones below skull.
Intramembranous ossification: Bone develops from fibrous membrane; forms flat and irregular bones (e.g., skull, clavicle).
Steps in Endochondral Ossification
Bone collar forms around diaphysis of cartilage model.
Central cartilage in diaphysis calcifies, develops cavities.
Periosteal bud invades cavities, forms spongy bone.
Diaphysis elongates, medullary cavity forms; secondary ossification centers appear in epiphyses.
Epiphyses ossify; hyaline cartilage remains in epiphyseal plates and articular cartilage.
Steps in Intramembranous Ossification
Ossification centers form as mesenchymal cells become osteoblasts.
Osteoid is secreted and calcified.
Woven bone and periosteum form.
Lamellar bone replaces woven bone; red marrow appears.
Postnatal Bone Growth
Growth in Length
Occurs at epiphyseal plate via interstitial growth.
Epiphyseal plate consists of five zones: resting, proliferation, hypertrophic, calcification, ossification.
Bone lengthening ceases when epiphysis and diaphysis fuse (epiphyseal plate closure).
Growth in Width (Appositional Growth)
Osteoblasts beneath periosteum secrete bone matrix externally.
Osteoclasts remove bone on endosteal surface.
Leads to thicker, stronger bone.
Hormonal Regulation
Growth hormone stimulates epiphyseal plate activity.
Thyroid hormone modulates growth hormone activity.
Testosterone and estrogens promote growth spurts and induce epiphyseal plate closure.
Bone Remodeling
Bone Deposit and Resorption
Bone remodeling occurs at periosteum and endosteum surfaces.
Osteoclasts resorb bone; osteoblasts deposit new matrix.
Hormonal controls: Parathyroid hormone (PTH) increases resorption; calcitonin lowers blood calcium.
Mechanical stress (Wolff's law): Bones remodel in response to stress; thicker where stresses are greatest.
Bone Repair
Fracture Classification
Position: Nondisplaced vs. displaced.
Completeness: Complete vs. incomplete.
Skin penetration: Open (compound) vs. closed (simple).
Common Types of Fractures
Type | Description |
|---|---|
Comminuted | Bone fragments in 3 or more pieces; common in old age. |
Compression | Bone is crushed; common in osteoporotic bones. |
Spiral | Ragged break from excessive twisting; common in sports. |
Epiphyseal | Epiphysis separates from diaphysis along epiphyseal plate. |
Depressed | Broken bone pressed inward; common in skull. |
Greenstick | Incomplete break; common in children. |
Fracture Treatment and Repair
Hematoma formation: Clotted blood at fracture site.
Fibrocartilaginous callus formation: Repair tissue forms.
Bony callus formation: Spongy bone replaces callus.
Bone remodeling: Restores original structure.
Bone Disorders
Osteomalacia and Rickets
Osteomalacia: Poor mineralization, soft bones, pain.
Rickets: Osteomalacia in children; bowed legs, bone deformities; caused by vitamin D deficiency or insufficient calcium.
Osteoporosis
Bone resorption exceeds deposit; bone mass declines.
Risk factors: Age, postmenopausal women, insufficient exercise, poor diet, smoking, genetics, hormone-related conditions.
Treatments: Calcium, vitamin D, exercise, hormone therapy, bisphosphonates, denosumab.
Prevention: Adequate calcium, reduced alcohol, weight-bearing exercise.
Paget's Disease
Excessive, haphazard bone deposit and resorption; poor bone structure.
Occurs in spine, pelvis, femur, skull; treated with calcitonin and bisphosphonates.
Developmental Aspects and Age-Related Changes
Embryonic skeleton ossifies predictably; fetal age determined by X-rays/sonograms.
Bone formation exceeds resorption in children/adolescents; balanced in young adults; resorption exceeds formation in adults.
Bone mass, mineralization, and healing decrease with age, especially in females and whites.
Additional info: Tables and figures referenced are recreated in text for clarity. Images included are directly relevant to anatomical structures, cartilage types, bone shapes, and ossification processes.
